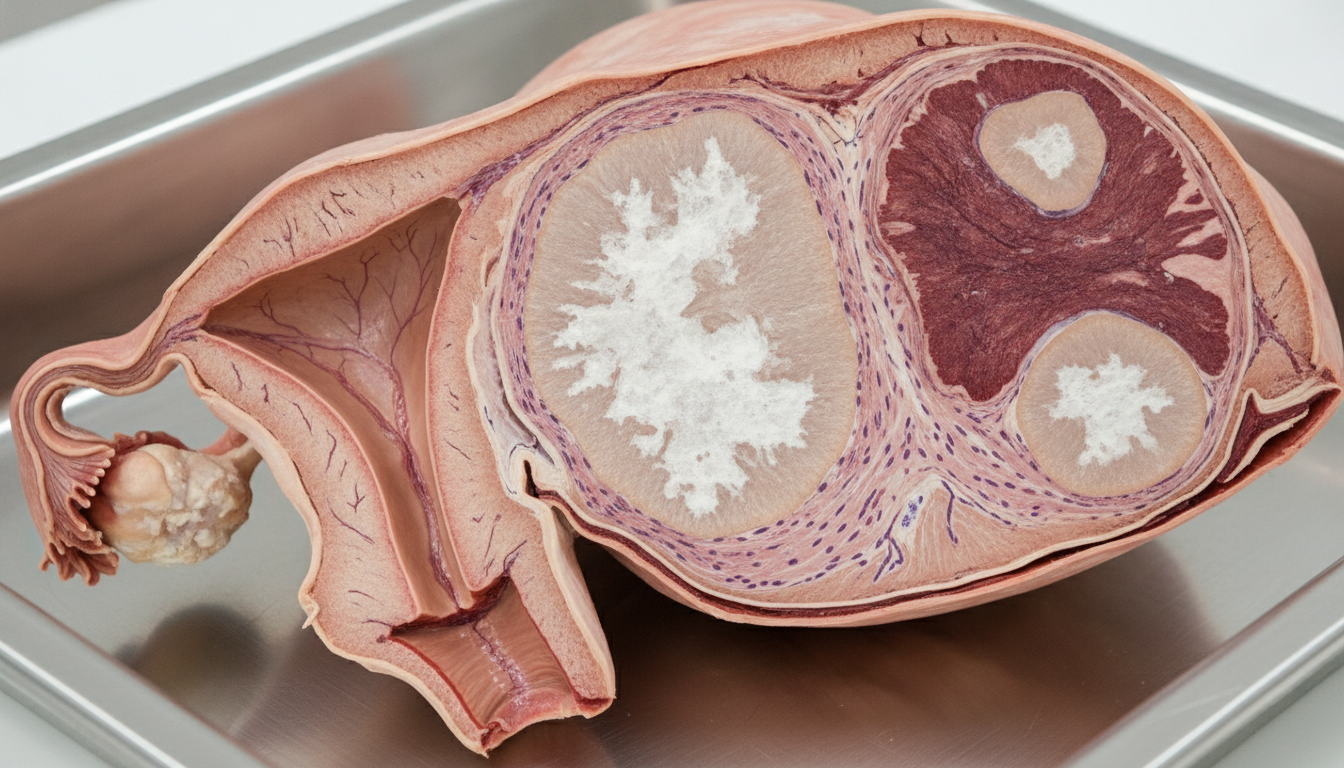
Detailed examination of Uterine fibroids on ultrasound symptoms pictures is crucial for accurate diagnosis and effective management. Understanding how these common benign growths appear on ultrasound and correlate with patient-reported symptoms provides invaluable insights for healthcare providers. This article delves into the visual manifestations and symptomatic presentations of uterine fibroids as captured through diagnostic imaging, offering a comprehensive resource.
Uterine fibroids on ultrasound Symptoms Pictures
While uterine fibroids themselves are internal growths, their presence and characteristics on ultrasound are intrinsically linked to the diverse range of symptoms experienced by individuals. The visual evidence from an ultrasound scan helps explain the severity and type of discomfort, allowing for a more targeted approach to care. The correlation between what is seen in uterine fibroids on ultrasound pictures and the patient’s symptoms is a cornerstone of clinical practice.
Common symptoms associated with uterine fibroids, often visible or inferable from fibroid ultrasound images, include:
- Heavy Menstrual Bleeding (Menorrhagia): This is one of the most prevalent symptoms. On ultrasound, this often correlates with the presence of submucosal fibroids, which protrude into the uterine cavity, or large intramural fibroids that distort the endometrial lining.
- Characteristics on ultrasound: Submucosal fibroids appear as hypoechoic masses within the endometrial cavity or pushing into it, often with clear delineation from the surrounding myometrium. Intramural fibroids causing heavy bleeding might be large, centrally located, and distort the endometrial stripe.
- Symptomatic presentation: Soaking through pads or tampons every hour, bleeding for more than seven days, passing large blood clots, and experiencing symptoms of anemia such like fatigue and shortness of breath. The degree of endometrial distortion by the fibroid directly impacts bleeding severity.
- Impact on daily life: Significant disruption of social activities, work productivity, and overall quality of life due to constant worry about bleeding.
- Prolonged Menstrual Periods: Similar to heavy bleeding, longer periods are frequently observed. Ultrasound imaging can reveal the size, number, and location of fibroids contributing to this symptom.
- Characteristics on ultrasound: Multiple fibroids, especially those near the endometrial lining or large fibroids that increase the surface area of the uterine lining, can lead to prolonged shedding. Vascularity within the fibroids, visible on Doppler ultrasound, can also contribute.
- Symptomatic presentation: Menstrual bleeding extending beyond the typical 5-7 days, sometimes lasting for two weeks or more. This is often coupled with heavy flow.
- Patient impact: Chronic discomfort, increased risk of iron-deficiency anemia, and ongoing management of menstrual hygiene.
- Pelvic Pressure and Pain: As fibroids grow, they can exert pressure on surrounding organs, leading to a sensation of heaviness or dull ache in the pelvis. Fibroid symptoms pictures often show large or multiple fibroids as the cause.
- Characteristics on ultrasound: Large intramural or subserosal fibroids, particularly those exceeding 5 cm in diameter, are frequently associated with pressure symptoms. The specific location, such as pressing on the bladder or rectum, is clearly visible.
- Symptomatic presentation: A feeling of fullness, bloating, or a constant heavy sensation in the lower abdomen. Pain can range from a dull ache to sharp, acute pain if degeneration occurs.
- Specific pain types: Dysmenorrhea (painful periods), dyspareunia (pain during intercourse if fibroids are near the cervix or vaginal vault), and chronic pelvic pain unrelated to menstruation.
- Frequent Urination or Difficulty Emptying Bladder: Fibroids, especially those located anteriorly (towards the front) or very large ones, can press on the bladder.
- Characteristics on ultrasound: Anterior subserosal or large intramural fibroids can be seen impinging upon the bladder wall, sometimes distorting its contour.
- Symptomatic presentation: Increased frequency of urination, urgency, or a sensation of incomplete bladder emptying. In rare cases, hydronephrosis (swelling of kidneys due to urine backup) can occur if fibroids compress the ureters, which would be visible on a comprehensive ultrasound.
- Differential diagnosis: Important to distinguish from urinary tract infections or overactive bladder, which can be ruled out with further tests.
- Constipation or Difficulty with Bowel Movements: Posterior (towards the back) fibroids or very large fibroids can press on the rectum.
- Characteristics on ultrasound: Posterior subserosal or large intramural fibroids are visualized in close proximity to the rectum, potentially causing its compression or displacement.
- Symptomatic presentation: Chronic constipation, straining during bowel movements, or a feeling of incomplete evacuation.
- Gastrointestinal impact: Can lead to discomfort, hemorrhoids, and a decreased quality of life.
- Backache or Leg Pain: Large fibroids can compress nerves or blood vessels in the pelvis or lower back.
- Characteristics on ultrasound: Large fibroids, particularly those in the posterior uterus or lower uterine segment, may be seen impinging on pelvic nerves or vessels.
- Symptomatic presentation: Persistent lower back pain, often dull and aching, or pain radiating down the legs (sciatica-like symptoms).
- Nerve compression: While less common, significant nerve compression can lead to paresthesia or weakness in the legs.
- Abdominal Swelling or Enlargement: Especially with multiple or very large fibroids, the uterus can grow to a size comparable to pregnancy.
- Characteristics on ultrasound: The uterus will appear significantly enlarged with multiple large hypoechoic masses. The overall uterine size can be measured and compared to a non-gravid uterus.
- Symptomatic presentation: Visible abdominal distension, feeling of fullness, and clothes fitting tighter around the waist.
- Patient perception: Often mistaken for weight gain or pregnancy, leading to distress and delayed diagnosis.
- Infertility or Pregnancy Complications: While many women with fibroids conceive without issues, certain fibroid types can impair fertility or cause adverse pregnancy outcomes.
- Characteristics on ultrasound: Submucosal fibroids distorting the endometrial cavity, intramural fibroids significantly enlarging the uterus or compromising blood flow to the endometrium, or fibroids blocking fallopian tube openings.
- Symptomatic presentation: Difficulty conceiving, recurrent miscarriages, preterm labor, placental abruption, or malpresentation of the fetus.
- Reproductive impact: Careful assessment via ultrasound images of fibroids is critical for women planning pregnancy or experiencing reproductive challenges.
Signs of Uterine fibroids on ultrasound Pictures
The ultrasound is the primary imaging modality for diagnosing uterine fibroids, providing characteristic signs of uterine fibroids on ultrasound pictures that are critical for identification and classification. These images allow clinicians to assess the number, size, location, and specific echogenicity of the fibroids, guiding treatment decisions. Understanding these visual signs is fundamental for accurate diagnosis.
Key ultrasound findings and characteristics of uterine fibroids include:
- Hypoechoic or Heterogeneous Masses: Fibroids typically appear as solid masses that are usually hypoechoic (darker) compared to the surrounding myometrium due to their dense, fibrous tissue content.
- Echogenicity: Most commonly hypoechoic. However, they can be isoechoic (similar echogenicity) or hyperechoic (brighter) if they contain calcifications or have undergone degeneration.
- Texture: Often appear as heterogeneous masses, meaning they have a mixed texture with areas of different echogenicity due to varying amounts of fibrous tissue, smooth muscle, and possibly areas of degeneration or necrosis.
- Clarity: Well-defined margins are common, distinguishing them from the surrounding normal uterine muscle.
- Well-Defined Margins: Fibroids usually have clear, distinct borders, separating them from the normal myometrium. This characteristic is a crucial diagnostic feature in uterine fibroids images.
- Capsule: A thin, pseudo-capsule, which is compressed myometrial tissue, can sometimes be observed surrounding the fibroid, further enhancing its distinct appearance.
- Shape: Typically round or ovoid in shape, though they can be irregular, especially when multiple fibroids coalesce.
- Posterior Shadowing: Dense fibrous tissue and, especially, calcifications within fibroids can cause acoustic shadowing, where the ultrasound waves are blocked, creating a darker area behind the fibroid.
- Calcifications: Degenerating fibroids or older fibroids often develop calcifications, appearing as bright echogenic foci with prominent posterior shadowing. These are unmistakable ultrasound signs of fibroids.
- Clinical significance: Calcified fibroids are typically benign and often indicate a long-standing lesion.
- Doppler Flow (Vascularity): Color or power Doppler ultrasound can demonstrate vascularity within or around the fibroid.
- Peripheral vascularity: Often, a rim of blood flow is seen around the fibroid, indicating its blood supply.
- Internal vascularity: While less common in benign fibroids, some can have internal vascularity, which may require differentiation from other masses, though fibroids typically have lower velocity flows than malignant tumors.
- Assessment: Doppler can help differentiate fibroids from other uterine masses, such as adenomyosis, which typically shows diffuse vascularity within the myometrial wall rather than focal flow.
- Mass Effect and Uterine Enlargement: Large fibroids or multiple fibroids can cause significant enlargement and distortion of the uterine contour.
- Uterine size: Measurement of the overall uterine dimensions, often reported in terms of gestational weeks (e.g., “16-week size uterus”) to convey the extent of enlargement.
- Contour distortion: Irregularity or lobulation of the outer uterine wall (serosal surface) due to subserosal or large intramural fibroids.
- Impact on other organs: Displacement or compression of the bladder, rectum, or ureters, visible on detailed imaging.
- Specific Locations of Fibroids on Ultrasound: The location is crucial for understanding symptoms and guiding management.
- Intramural fibroids: The most common type, located within the muscular wall of the uterus (myometrium). They appear as well-defined masses within the uterine wall. These are frequently depicted in uterine fibroids on ultrasound pictures.
- Subserosal fibroids: Located on the outer surface of the uterus, often bulging outwards. They can be sessile (broad-based) or pedunculated (attached by a stalk). Pedunculated subserosal fibroids can sometimes be mistaken for ovarian masses.
- Submucosal fibroids: Located just beneath the endometrial lining, protruding into the uterine cavity. These are often associated with heavy bleeding and infertility. They are typically seen distorting the endometrial stripe on ultrasound.
- Pedunculated fibroids: Can be subserosal or submucosal, attached by a stalk. Torsion of a pedunculated fibroid can cause acute, severe pain.
- Cervical fibroids: Located in the cervix, less common but can cause unique symptoms related to bladder/bowel obstruction or pain.
- Intraligamentary fibroids: Located within the broad ligament, potentially dissecting between its layers, requiring careful differentiation from adnexal masses.
- Degenerative Changes: Fibroids can undergo various forms of degeneration, which alter their ultrasound appearance.
- Hyaline degeneration: The most common type, often showing amorphous, anechoic areas within the fibroid.
- Cystic degeneration: Appears as well-defined anechoic (fluid-filled) areas within the fibroid.
- Red degeneration: Hemorrhagic infarction, often seen during pregnancy, presenting as an acute painful event. On ultrasound, it may show increased echogenicity (brighter) with areas of hemorrhage, sometimes with a peripheral hypoechoic rim.
- Myxoid degeneration: Rare, presenting as anechoic or hypoechoic areas with internal echoes.
- Fatty degeneration: Very rare, can show hyperechoic (brighter) areas within the fibroid.
Early Uterine fibroids on ultrasound Photos
Detecting uterine fibroids in their early stages or when they are still small can be challenging but is important for understanding their natural history and potential future impact. Early uterine fibroids on ultrasound photos typically show subtle characteristics that require careful attention from the sonographer. These nascent fibroids might not yet cause significant symptoms, making their ultrasound detection often incidental or prompted by non-specific complaints.
Characteristics of early or small uterine fibroids on ultrasound:
- Small, Well-Defined Hypoechoic Nodules: Early fibroids often appear as discrete, small (e.g., a few millimeters to 2-3 cm) hypoechoic nodules within the myometrium.
- Size range: Can be as small as 0.5 cm, sometimes only visible with high-frequency transvaginal probes.
- Differentiation: At this stage, it’s crucial to differentiate them from normal myometrial vessels or focal adenomyosis, which typically lacks the well-defined capsule of a fibroid.
- Echogenicity: Usually consistently hypoechoic, without significant heterogeneity unless early degenerative changes are already present.
- Subtle Myometrial Distortion: Unlike large fibroids that visibly distort the uterine contour, early intramural fibroids might only cause very subtle localized bulging or alteration of the myometrial architecture.
- Contour: The uterine serosal contour usually remains smooth, but a slight localized bulge may be present with subserosal fibroids.
- Endometrial line: Small submucosal fibroids may cause only minor indentation of the endometrial stripe, which can be challenging to discern without careful evaluation.
- Lack of Significant Shadowing or Calcification: Early fibroids are typically soft and do not yet contain dense calcifications. Therefore, prominent posterior shadowing is usually absent.
- Echogenic foci: Any echogenic foci in early fibroids usually represent small areas of increased fibrous tissue rather than macroscopic calcification.
- Homogeneity: Tend to be more homogeneous in echotexture compared to larger, older fibroids that have undergone degeneration.
- Minimal Vascularity on Doppler: Small fibroids may show very little or no discernible blood flow on color Doppler ultrasound, or only minimal peripheral vascularity.
- Perfusion: Blood supply is present but may not be robust enough to be easily detected by standard Doppler settings, especially for very small lesions.
- Diagnostic utility: Doppler is still useful to confirm the presence of a solid mass and rule out cystic structures.
- Incidental Findings: Many early uterine fibroids on ultrasound photos are discovered incidentally during pelvic ultrasound performed for other reasons, such as routine gynecological check-ups, evaluation of ovarian cysts, or fertility assessments.
- Asymptomatic: Patients typically do not experience symptoms directly attributable to these small fibroids.
- Monitoring: Once detected, these early fibroids can be monitored over time for growth and development of symptoms.
- Challenges in Detection:
- Operator dependence: Identification of very small fibroids relies heavily on the skill and experience of the sonographer.
- Image quality: Factors like patient body habitus, bowel gas, and probe frequency can affect the visibility of subtle lesions.
- Differentiation from normal variants: Distinguishing small fibroids from normal myometrial fascicles or localized uterine contractions can be difficult.
- Multiple small fibroids: The presence of numerous small fibroids can make the myometrium appear generally heterogeneous, potentially obscuring individual lesions.
- Symptoms Prompting Early Ultrasound: Even small fibroids can cause symptoms if located strategically.
- Submucosal location: A small submucosal fibroid (even 1-2 cm) can cause significant heavy bleeding and prolonged periods due to its proximity to the endometrial lining. These are often the earliest fibroids to cause noticeable symptoms.
- Pelvic discomfort: While rare for very small fibroids, a pedunculated fibroid, even if small, could potentially twist, causing acute pain that prompts an early ultrasound.
- Fertility concerns: An early ultrasound in women struggling with conception may reveal small fibroids that, despite their size, are impacting implantation or tubal patency.
Skin rash Uterine fibroids on ultrasound Images
It is crucial to clarify that Uterine fibroids on ultrasound Images and Skin rash Uterine fibroids on ultrasound Images are not directly related. Uterine fibroids are benign tumors of the uterus and do not directly cause skin rashes. Therefore, there are no specific ultrasound images or visual representations that would link a skin rash directly to the presence of uterine fibroids. The phrase “Skin rash Uterine fibroids on ultrasound Images” is based on a misunderstanding of how fibroids manifest.
However, it is important to address why such a question might arise and to discuss potential indirect connections or important differential considerations:
- Uterine Fibroids Do Not Directly Cause Skin Rashes:
- Internal pathology: Fibroids are internal growths composed of smooth muscle and fibrous connective tissue within the uterine wall. Their symptoms are typically related to their size, number, and location within the pelvis (e.g., heavy bleeding, pelvic pressure, pain, urinary/bowel issues).
- No dermal manifestation: There is no known physiological mechanism by which uterine fibroids directly trigger a dermatological (skin) response such as a rash.
- Potential Indirect Associations (Not Causal): While not directly causing rashes, fibroids can be associated with broader physiological changes or co-existing conditions that *might* indirectly involve the skin. These are not specific skin rash uterine fibroids images but rather secondary considerations:
- Hormonal Imbalance: Fibroids are estrogen-dependent tumors. While severe hormonal imbalances *can* sometimes influence skin health (e.g., acne, melasma), there is no direct link to a “fibroid rash.” Any skin changes would be general, not fibroid-specific.
- Estrogen dominance: High estrogen levels, sometimes associated with fibroids, can theoretically influence skin conditions in some individuals, but this is not a direct rash.
- Anemia: Chronic heavy menstrual bleeding caused by fibroids often leads to iron-deficiency anemia. While anemia primarily causes fatigue and pallor, severe cases can sometimes be associated with generalized dryness or brittle nails, but not typically a rash.
- Stress and Systemic Inflammation: Living with chronic pain, heavy bleeding, and the anxiety associated with fibroid symptoms can be stressful. Stress can exacerbate or trigger various skin conditions (e.g., eczema, psoriasis, hives) in predisposed individuals, but this is a secondary effect of stress, not a direct fibroid manifestation.
- Medication Side Effects: If a patient is undergoing medical treatment for fibroids (e.g., GnRH agonists, tranexamic acid), some medications might have skin-related side effects, including rashes. This would be a drug reaction, not a fibroid symptom.
- Co-existing Conditions: A person with uterine fibroids may coincidentally develop an unrelated skin rash. This rash would be due to other causes (e.g., allergies, infections, other dermatological conditions) and not the fibroids themselves.
- Importance of differential diagnosis: It is crucial for clinicians to investigate any skin rash separately, considering common dermatological causes.
- Hormonal Imbalance: Fibroids are estrogen-dependent tumors. While severe hormonal imbalances *can* sometimes influence skin health (e.g., acne, melasma), there is no direct link to a “fibroid rash.” Any skin changes would be general, not fibroid-specific.
- What to Do if a Rash Develops with Fibroids:
- Consult a Dermatologist: Any new or unexplained skin rash should be evaluated by a dermatologist or a general practitioner to determine its cause and appropriate treatment.
- Do not attribute directly to fibroids: Patients should be advised against assuming a direct causal link between their fibroids and a skin rash.
- Holistic assessment: A thorough medical history should include all current symptoms, medications, and other health conditions.
- Clarification on Ultrasound and Skin:
- Ultrasound imaging, especially transabdominal and transvaginal ultrasound, is used to visualize internal pelvic structures, primarily the uterus and ovaries. It cannot visualize or diagnose skin rashes, which are superficial dermatological conditions.
- There are no ultrasound criteria or imaging characteristics that would ever depict or diagnose a skin rash in conjunction with uterine fibroids. The focus of uterine fibroids on ultrasound pictures remains exclusively on the internal uterine pathology.
In summary, while the question of “Skin rash Uterine fibroids on ultrasound Images” highlights a potential area of confusion, it is important to reiterate that uterine fibroids do not cause skin rashes. Any co-occurrence would be coincidental or related to indirect systemic factors, requiring separate dermatological evaluation. Ultrasound is a tool for imaging the uterus, not the skin.
Uterine fibroids on ultrasound Treatment
The diagnosis of uterine fibroids, primarily confirmed through uterine fibroids on ultrasound pictures, paves the way for a discussion of various treatment options. Treatment for uterine fibroids is highly individualized, depending on the patient’s symptoms, fibroid size and location (as seen on ultrasound), desire for future fertility, age, and overall health. The goal of treatment is typically to manage symptoms, reduce fibroid size, or remove the fibroids.
Treatment approaches, guided by fibroid ultrasound images and clinical assessment, include:
- Watchful Waiting (Expectant Management):
- Indication: For asymptomatic or mildly symptomatic fibroids, especially small ones visualized on early uterine fibroids ultrasound photos, or when nearing menopause.
- Management: Regular follow-up appointments, including periodic ultrasound scans to monitor fibroid growth and symptom development.
- Rationale: Many fibroids do not cause significant problems, and some may shrink after menopause.
- Medical Management (Non-Surgical): These treatments aim to manage symptoms like heavy bleeding and pain, and sometimes to reduce fibroid size, without removing the fibroids themselves.
- Nonsteroidal Anti-inflammatory Drugs (NSAIDs):
- Mechanism: Reduce prostaglandin production, which helps decrease menstrual flow and alleviate pain (dysmenorrhea).
- Indication: Mild-to-moderate pain and heavy bleeding.
- Effectiveness: Primarily symptomatic relief, does not affect fibroid size.
- Tranexamic Acid:
- Mechanism: An antifibrinolytic that reduces menstrual blood loss by inhibiting the breakdown of blood clots.
- Indication: Heavy menstrual bleeding associated with fibroids.
- Effectiveness: Significantly reduces blood loss; taken only during heavy bleeding days. Does not affect fibroid size or volume.
- Hormonal Contraceptives (Birth Control Pills, Patches, Rings):
- Mechanism: Help regulate the menstrual cycle, reduce menstrual flow, and alleviate pain.
- Indication: Heavy and painful periods.
- Effectiveness: Primarily symptomatic relief; do not shrink fibroids but can help control bleeding.
- Progestin-Releasing Intrauterine Device (IUD) (Mirena):
- Mechanism: Releases levonorgestrel directly into the uterus, thinning the endometrial lining and reducing menstrual bleeding.
- Indication: Heavy menstrual bleeding.
- Effectiveness: Highly effective for reducing bleeding and pain; does not typically shrink fibroids but manages symptoms well, especially for intramural or subserosal fibroids not distorting the cavity significantly. Submucosal fibroids distorting the cavity may preclude IUD placement.
- Gonadotropin-Releasing Hormone (GnRH) Agonists (e.g., Lupron):
- Mechanism: Induce a temporary, reversible menopause-like state by suppressing estrogen production, leading to fibroid shrinkage.
- Indication: Used to shrink fibroids pre-surgically to make surgery easier, or to manage severe symptoms.
- Effectiveness: Can shrink fibroids by 30-50% within a few months. Effect is temporary, fibroids regrow after stopping treatment. Side effects include menopausal symptoms.
- Selective Progesterone Receptor Modulators (SPRMs) (e.g., Ulipristal Acetate):
- Mechanism: Act on progesterone receptors to reduce fibroid size and control bleeding.
- Indication: Pre-operative treatment or long-term management of symptoms.
- Availability: Availability varies by country due to regulatory concerns regarding liver safety.
- Nonsteroidal Anti-inflammatory Drugs (NSAIDs):
- Minimally Invasive Procedures: These procedures treat fibroids without major abdominal surgery, often guided by imaging.
- Uterine Artery Embolization (UAE) / Uterine Fibroid Embolization (UFE):
- Mechanism: A radiologist inserts a catheter into the femoral artery, guides it to the uterine arteries, and injects small particles to block blood flow to the fibroids, causing them to shrink and die.
- Indication: Most symptomatic fibroids, especially multiple or large ones, suitable for women who do not desire future pregnancy or want to avoid hysterectomy. Effectiveness is highly influenced by fibroid location and vascularity as shown in ultrasound images of fibroids.
- Effectiveness: Highly effective in reducing symptoms and fibroid volume.
- Magnetic Resonance-Guided Focused Ultrasound Surgery (MRgFUS / ExAblate):
- Mechanism: Uses high-intensity focused ultrasound waves, guided by MRI, to heat and ablate (destroy) fibroid tissue.
- Indication: Select symptomatic fibroids, typically for women who desire a non-invasive option and are not planning future pregnancies. Fibroids need to be visible and accessible on MRI/ultrasound.
- Effectiveness: Can effectively reduce fibroid volume and symptoms.
- Endometrial Ablation:
- Mechanism: Destroys the lining of the uterus to reduce heavy bleeding.
- Indication: Heavy bleeding, typically for women who have completed childbearing and have small or no submucosal fibroids that significantly distort the cavity.
- Effectiveness: Highly effective for heavy bleeding; does not treat the fibroids themselves.
- Radiofrequency Ablation (RFA) / Acessa Procedure:
- Mechanism: Uses heat from radiofrequency energy delivered via a laparoscopic probe to destroy fibroid tissue.
- Indication: Symptomatic intramural fibroids, especially for women seeking a minimally invasive option to preserve the uterus.
- Effectiveness: Shrinks fibroids and reduces symptoms.
- Uterine Artery Embolization (UAE) / Uterine Fibroid Embolization (UFE):
- Surgical Management: These options involve removing the fibroids or the entire uterus.
- Myomectomy:
- Mechanism: Surgical removal of only the fibroids, preserving the uterus.
- Indication: Symptomatic fibroids, especially for women who wish to preserve fertility or the uterus. Location, size, and number of fibroids (as shown in ultrasound photos of fibroids) determine the surgical approach.
- Approaches:
- Hysteroscopic Myomectomy: For submucosal fibroids protruding into the uterine cavity. A hysteroscope is inserted through the vagina and cervix.
- Laparoscopic Myomectomy: For subserosal or intramural fibroids, performed through small incisions in the abdomen.
- Open Abdominal Myomectomy (Laparotomy): For large, numerous, or deeply embedded fibroids, requiring a larger abdominal incision.
- Effectiveness: Highly effective in relieving symptoms and improving fertility outcomes. Risk of fibroid recurrence.
- Hysterectomy:
- Mechanism: Surgical removal of the entire uterus.
- Indication: Severe, persistent symptoms not managed by other treatments, large or numerous fibroids, or when fertility preservation is not desired. Often considered a definitive cure.
- Approaches: Can be performed abdominally (open), vaginally, or laparoscopically (minimally invasive).
- Effectiveness: Completely eliminates fibroids and their symptoms. Leads to permanent infertility and menopause if ovaries are also removed.
- Myomectomy:
- Considerations for Treatment Decisions Based on Ultrasound Findings:
- Fibroid Size and Number: Larger and more numerous fibroids (evident in uterine fibroids on ultrasound pictures) may necessitate more aggressive treatments like UAE, myomectomy, or hysterectomy, especially if symptoms are severe. Small, asymptomatic fibroids may only require observation.
- Fibroid Location:
- Submucosal fibroids: Often best treated with hysteroscopic myomectomy for bleeding and fertility issues.
- Intramural fibroids: Can be treated with medical therapy, UAE, laparoscopic or open myomectomy, or hysterectomy, depending on size and symptoms.
- Subserosal fibroids: Less likely to cause bleeding but can cause pressure. Often suitable for laparoscopic myomectomy or observation. Pedunculated subserosal fibroids may undergo torsion, requiring emergency surgery.
- Vascularity: Doppler ultrasound can assess fibroid vascularity, which can influence the success of UAE.
- Degenerative Changes: Fibroids undergoing degeneration (visible on ultrasound) can cause acute pain; treatment may focus on pain management in the acute phase.
- Associated Uterine Pathology: Ultrasound may reveal co-existing conditions like adenomyosis or endometrial hyperplasia, which can influence the choice of treatment.