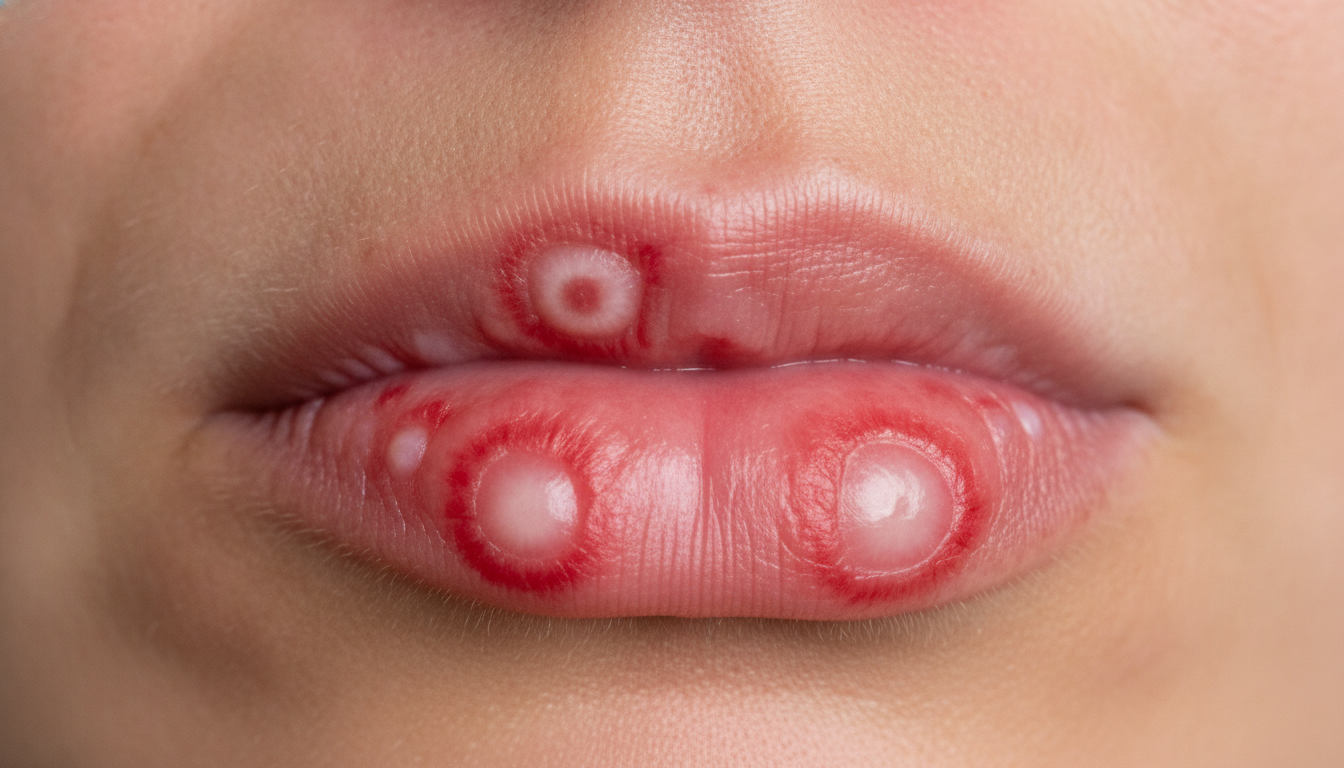
Understanding the visual presentation of skin conditions is crucial for identification and management. This article delves into “Urticaria on the face symptoms pictures”, providing a detailed look at how this common skin reaction manifests on facial skin, aiding in its recognition.
Urticaria on the face Symptoms Pictures
Urticaria on the face presents with distinct
The appearance of
Color : Hives typically appear erythematous (red) in individuals with lighter skin tones, often with a paler, edematous center. In individuals with darker skin tones, the lesions may be skin-colored, hyperpigmented, or subtly violaceous, making the raised texture and surrounding erythema more indicative.Shape and Size : Lesions can be round, oval, annular (ring-shaped), serpiginous (snake-like), or polycyclic (multiple rings). Their size is highly variable, from a few millimeters to several centimeters across. They can also coalesce to form larger patches.Elevation : Wheals are characteristically elevated from the surrounding skin due to dermal edema. This elevation is clearly discernible, giving them a puffy or swollen appearance.Blanching : When pressed, urticarial lesions typically blanch (turn white) due to the temporary displacement of blood in the superficial capillaries. This is an important diagnostic sign visible inurticaria photos .Associated Swelling (Angioedema) : Particularly on the face,urticaria can be accompanied byangioedema , which is deeper swelling affecting the dermis and subcutaneous tissues. This manifests as significant swelling of the lips, eyelids, cheeks, or tongue. Unlike hives, angioedema is often painful or tight rather than intensely itchy and can persist longer, sometimes for up to 72 hours. This distinction is crucial forfacial urticaria diagnosis .
Common areas for
Periorbital region : Swelling around the eyes, particularly the eyelids, making them appear puffy or closed.Lips : Significant swelling of one or both lips, often causing disfigurement and difficulty with speech or eating.Cheeks : Diffuse or localized swelling and redness on the cheeks.Forehead : Raised lesions and diffuse swelling.Ears : Swelling and redness of the earlobes or entire ear.
Understanding these
Signs of Urticaria on the face Pictures
The
Detailed
Transient Wheals : The rapid onset and resolution of individual wheals within 24 hours (usually much quicker, often in a few hours) is a definitive sign. This impermanence distinguishesurticarial lesions from other persistentskin rashes .Angioedema : When present,angioedema is a critical sign, especially on the face. It manifests as a localized, non-pitting edema that involves the deeper layers of the skin and subcutaneous tissue. Common sites forfacial angioedema pictures include:Lips : Sudden and pronounced swelling, often causing them to protrude significantly.Eyelids : Marked puffiness, sometimes severe enough to obstruct vision.Tongue and Pharynx : Potentially life-threatening swelling that can lead to airway obstruction. This demands immediate medical attention.Cheeks and Jawline : A swollen, tight sensation across the lower face.
Unlike hives,
angioedema is typically more painful or associated with a sensation of tightness/pressure rather than intense itching, and it resolves more slowly, often over 1-3 days.Dermatographism : While not exclusive to the face, in some individuals, stroking or scratching the skin (including on the face) can induce linear wheals. This sign, visible inskin testing photos , indicates a heightened skin reactivity.Blanching with Pressure : As mentioned, applying pressure to a hive causes it to temporarily turn white due to the vascular nature of the lesion. This is a simple yet effective diagnostic test that can be observed inclinical images of urticaria .Erythema and Edema : The twin signs of redness (erythema) and swelling (edema) are always present. The degree of redness can vary, but the raised, swollen nature of thehives is constant.Absence of Secondary Lesions (initially) : In the early stages,facial urticaria typically presents without excoriations (scratch marks), crusts, or scales, which might be seen in other chronicfacial dermatoses . However, prolonged scratching can lead to secondary changes.Associated Systemic Symptoms : While primarily a skin condition, severeurticaria with angioedema can sometimes be accompanied by systemic signs such as difficulty breathing (due to laryngeal angioedema), abdominal pain, nausea, vomiting, dizziness, or even syncope, especially in cases of anaphylaxis. These are crucial to recognize when assessing the severity offacial swelling .
These
Early Urticaria on the face Photos
Recognizing
The
Pinpoint Erythema : The very first sign might be small, transient red spots or patches on the skin, resembling mosquito bites. These tiny areas of redness are where the mast cells have begun to degranulate, releasing histamine and other mediators.Slightly Raised Papules : These small red spots quickly evolve into slightly raised, firm papules. These initial elevations are often accompanied by a distinctitching sensation , which can be the first subjective symptom reported by the individual.Localized Warming Sensation : Before visible swelling, some individuals report a localized feeling of warmth or a tingling sensation on the affected areas of the face. This often precedes the full development of a wheal.Rapid Expansion : Within minutes to an hour, these small papules expand centrifugally to form larger, more recognizable wheals. The borders may still be somewhat irregular or ill-defined in theseearly stages of facial urticaria .Evolving Edema : The central pallor of the wheal, indicative of significant dermal edema, may not be immediately apparent but develops as the lesion matures. The overallfacial skin swelling becomes more prominent.Periorbital or Perioral Itch : Due to the delicate nature of the skin around the eyes and mouth, an early, intense itch in these areas can be a precursor toangioedema of the eyelids orswollen lips , which are often the first visible signs of deeper swelling on the face.
Factors influencing
Trigger Exposure : If related to a specific trigger (e.g., food allergen, insect sting, medication), theearly facial reaction might appear very quickly, sometimes within minutes.Contact urticaria on the face will typically show initial redness and itching precisely where the skin touched the irritant.Physical Urticaria : For conditions likecold urticaria , initial blanching followed by erythema and wheal formation may be observed upon rewarming of facial skin after cold exposure.Solar urticaria will show initial redness and hives specifically on sun-exposed facial areas.Stress or Heat : Cholinergic urticaria, often triggered by heat or emotional stress, may initially present as very small, itchy papules on the face, sometimes accompanied by flushing, before coalescing.
Catching these
Skin rash Urticaria on the face Images
When observing
Key characteristics of the
Distribution Patterns :Localized Eruption : Hives may be concentrated in specific areas, such as around the eyes, lips, or cheeks, often indicating a localized trigger or an initial site of reaction.Diffuse Involvement : In more severe cases, the entire face can be covered with wheals, appearing as a generalizedred, swollen rash .Asymmetrical vs. Symmetrical : The rash can appear on one side of the face (asymmetrical) or on both sides (symmetrical), depending on the trigger and individual response.Coalescing Lesions : Individual wheals often merge to form large, irregularly shaped patches or plaques, especially in areas with looser skin like the eyelids or lips.
Color and Texture Variability :Bright Red to Pale Pink : The color can vary significantly, from a vivid red, especially at the borders, to a paler pink or even skin-colored hue, particularly in the center of older lesions or on darker skin.Smooth and Shiny : The surface of the wheals is typically smooth and shiny due, to underlying edema, with no scaling or blistering (unless secondary to severe scratching).Induration : The rash feels firm to the touch due to the swelling, especially where angioedema is present.
Migratory Nature : A defining feature is the fleeting and shifting nature of the rash. A patch ofhives on the forehead in onephoto might have completely resolved in a subsequent image taken hours later, with new lesions appearing on the chin or nose. Thistransient skin rash pattern is diagnostic.Associated Angioedema : Frequently, thefacial urticarial rash is accompanied by deeper, non-pitting swelling (angioedema), which is particularly noticeable around the eyes and lips. This swelling can significantly alter facial features and adds a critical dimension to thevisual assessment of the rash . Infacial angioedema photos , the swelling appears taut and firm, unlike the more superficial wheals.Secondary Changes : Prolonged or intense itching can lead to secondary skin changes, such as excoriations (scratch marks), lichenification (skin thickening from chronic rubbing), or post-inflammatory hyperpigmentation (darkening of the skin after the rash resolves), especially in chronic cases. These are less typical inacute facial urticaria but can be seen inchronic hives on the face .
Specific types of
Acute Spontaneous Urticaria : Most commonly seen, appearing suddenly and lasting less than 6 weeks. Often triggered by infections, medications, or food.Chronic Spontaneous Urticaria (CSU) : Hives occurring almost daily for more than 6 weeks without an identifiable external trigger. Thefacial rash is persistent and recurrent.Physical Urticaria : Rashes triggered by physical stimuli:Cold Urticaria : Hives appear on facial skin exposed to cold temperatures upon rewarming.Solar Urticaria : Rash develops rapidly on sun-exposed facial areas.Dermatographism : Linear wheals following pressure or stroking on the face.Cholinergic Urticaria : Tiny, very itchy papules often seen on the face and upper torso, triggered by heat, exercise, or stress.
Contact Urticaria : Arash developing on facial areas directly contacting an allergen or irritant (e.g., cosmetics, topical medications, certain foods).
Interpreting
Urticaria on the face Treatment
Comprehensive
1. Antihistamines (First-Line Therapy)
Non-sedating H1-antihistamines are the cornerstone of
Second-Generation H1-Antihistamines :Examples : Fexofenadine, Loratadine, Cetirizine, Desloratadine, Levocetirizine.Dosage : Often started at standard doses (e.g., once daily), but forchronic spontaneous urticaria (CSU) or persistentfacial hives , guidelines recommend increasing the dose up to four times the standard dose, under medical supervision, before considering other therapies.Benefits : Less sedating than older antihistamines, making them suitable for daily use.
First-Generation H1-Antihistamines :Examples : Diphenhydramine, Hydroxyzine.Usage : Can be used for breakthroughitching , especially at night due to their sedative effects, which can help with sleep disturbances caused by severefacial itching . Not recommended for long-term daily use due to sedation and anticholinergic side effects.
2. Corticosteroids
Used for acute, severe flares of
Oral Corticosteroids :Usage : Short courses (e.g., 3-7 days) of oral prednisone or prednisolone can rapidly suppress severehives andangioedema on the face.Caution : Not for long-term use due to significant side effects (e.g., weight gain, bone density loss, hypertension), especially in the management ofchronic urticaria . A careful tapering schedule is often employed.
Topical Corticosteroids :Usage : Generally not very effective for deep-seatedurticarial lesions orangioedema as they don’t penetrate deeply enough. They might offer some superficialitch relief for very mild, localized hives but should be used with extreme caution on the face due to risks of skin thinning, telangiectasias, and acneiform eruptions, especially with potent preparations.
3. Leukotriene Receptor Antagonists
Example : Montelukast.Usage : Sometimes used as an add-on therapy, especially forurticaria unresponsive to antihistamines, or in cases where aspirin or NSAIDs exacerbatehives . Its effectiveness forfacial urticaria specifically can vary.
4. Immunosuppressants
For severe
Cyclosporine :Usage : An effective option for difficult-to-treatCSU , includingfacial involvement . It works by suppressing the immune system.Monitoring : Requires careful monitoring for side effects such as kidney toxicity and hypertension.
5. Biologics
Omalizumab (Xolair) :Mechanism : A monoclonal antibody that targets IgE, reducing IgE levels and stabilizing mast cells.Usage : Approved forchronic spontaneous urticaria in adults and adolescents (12 years and older) who remain symptomatic despite H1-antihistamine treatment. It has shown significant efficacy in reducinghives andangioedema , includingfacial swelling , and improving quality of life. Administered via subcutaneous injection, typically every 2 or 4 weeks.Benefits : Provides sustained control for many patients where other treatments have failed, leading to a significant reduction infacial rash anditching .
6. Emergency Treatment for Severe Angioedema on the Face
If
Epinephrine : Administered via auto-injector (e.g., EpiPen) or by medical professionals.Intravenous Antihistamines and Corticosteroids : To rapidly reduce swelling and prevent progression.Airway Management : In severe cases, intubation may be necessary.
7. Trigger Avoidance and Supportive Care
Identify and Avoid Triggers : Keeping a symptom diary can help identify specificfacial urticaria triggers such as foods, medications (e.g., NSAIDs, ACE inhibitors), infections, stress, or physical stimuli (cold, heat, pressure, sunlight). Eliminating these can significantly reducefacial hives .Cool Compresses : Applying cool, damp cloths to theitchy facial areas can provide symptomatic relief and reduce swelling.Moisturizers : Keeping the skin well-hydrated with gentle, fragrance-free moisturizers can help maintain skin barrier function and reduce general irritation, although they do not directly treat hives.Avoid Scratching : While difficult due to intenseitching , scratching can exacerbate the rash and lead to secondary skin infections or scarring. Keeping nails short can help.Stress Management : Stress is a known trigger forurticaria flares , includingfacial involvement . Techniques like meditation, yoga, or counseling can be beneficial.
The