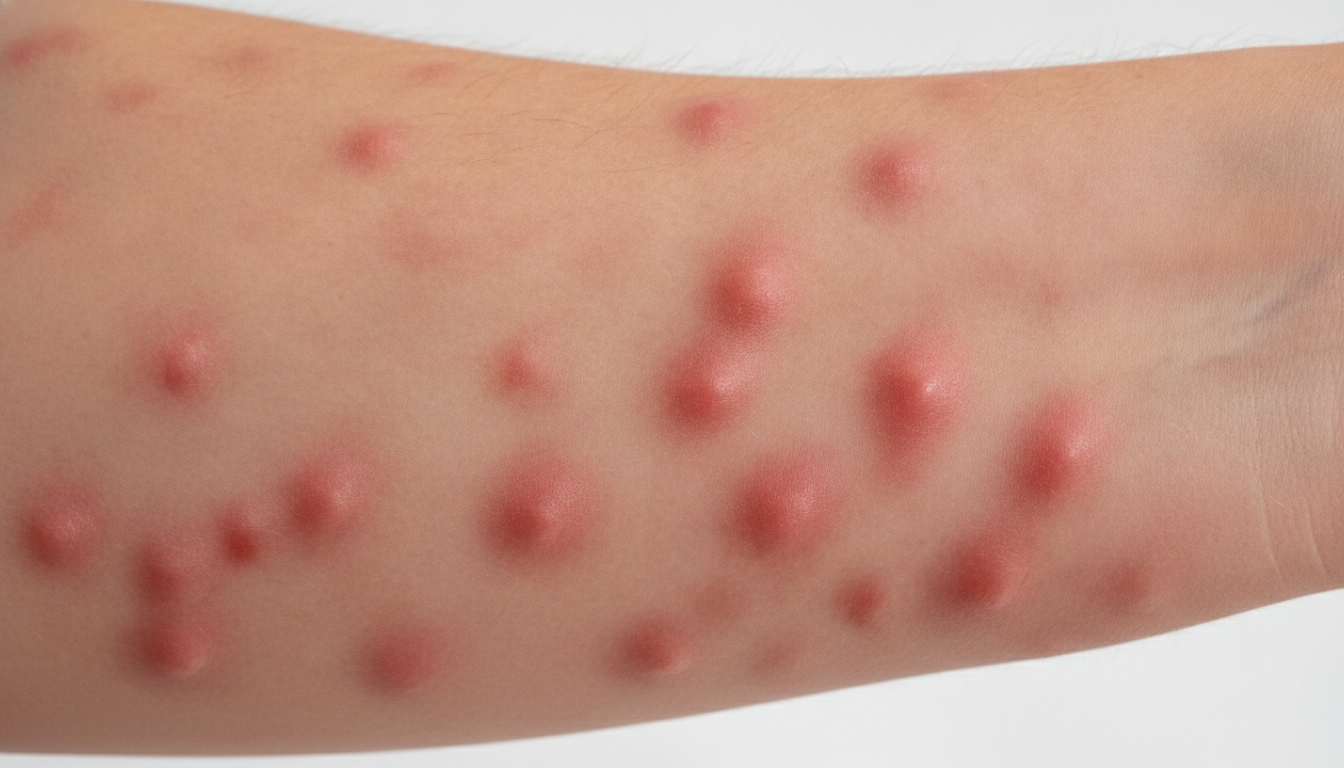
Urticaria allergy symptoms pictures often display a distinctive pattern of skin reactions. These visual manifestations are key to identifying this common condition, presenting as raised, itchy welts that can appear suddenly and disappear just as quickly, making the characteristic appearance of urticaria allergy symptoms pictures crucial for recognition.
Urticaria allergy Symptoms Pictures
Urticaria, commonly known as hives, presents a highly characteristic set of visual symptoms that are vital for diagnosis. The hallmark of urticaria allergy symptoms pictures is the presence of wheals, also referred to as weals or hives. These are raised, erythematous (red) or sometimes skin-colored lesions that typically blanch (turn white) when pressure is applied. They can vary dramatically in size, from a few millimeters to several centimeters in diameter, and their shapes are equally diverse, ranging from round or oval to highly irregular, often with ragged borders. A key feature captured in urticaria allergy symptoms pictures is their transient nature; individual lesions typically appear, change size and shape, and then fade within 24 hours without leaving any residual marks, though new lesions may continually emerge in different areas, giving the impression of a migrating rash. The primary sensation associated with these visible signs is intense pruritus, or itching, which can be severe and debilitating, significantly impacting quality of life. Some individuals may also report a burning, stinging, or tingling sensation accompanying the itching, particularly as the wheals develop or when they are exposed to specific triggers. The distribution of these wheals is highly variable, potentially affecting any part of the body, including the trunk, limbs, face, scalp, palms, and soles. In some instances, wheals may coalesce to form larger, more extensive areas of raised skin, creating large patches of inflamed and intensely itchy skin, which is a common presentation in severe urticaria allergy pictures. The color of the wheals can also offer clues, with some appearing bright red, especially on lighter skin tones, while on darker skin, they might appear more purple or darker than the surrounding skin, or simply as elevated areas of skin. Furthermore, accompanying the wheals in a significant number of cases is angioedema. Angioedema is a deeper swelling that affects the subcutaneous or submucosal tissues, contrasting with the superficial nature of wheals. This manifests as significant swelling of the lips, eyelids, tongue, genitals, hands, or feet. While not typically itchy, angioedema can cause a sensation of tightness, burning, or discomfort. In severe cases, swelling of the tongue or throat can lead to difficulty breathing or swallowing, representing a medical emergency that might also be present in critical urticaria allergy symptoms pictures. Recognizing the distinctive appearance and transient nature of these skin lesions, alongside any associated angioedema, is paramount for accurate identification of urticaria allergy symptoms and subsequent management.
- Wheals (Hives) Appearance:
- Size Variation: From small, pinpoint papules (1-2mm) to large, confluent plaques (several centimeters).
- Shape Diversity: Round, oval, annular (ring-shaped), serpiginous (snake-like), or highly irregular with ill-defined borders.
- Coloration: Erythematous (red) on lighter skin tones, often paler in the center, or skin-colored. On darker skin tones, they may appear darker than surrounding skin, purplish, or simply as areas of raised skin.
- Blanching: A defining characteristic where the wheals turn white when pressure is applied, indicating vascular dilation rather than hemorrhage.
- Elevation: Distinctly raised above the surrounding skin, giving them a palpable quality.
- Distribution: Can appear anywhere on the body, including the face, trunk, extremities, palms, soles, and scalp.
- Transient Nature: Individual lesions typically resolve within 24 hours without scarring or post-inflammatory changes, though new lesions may continuously form elsewhere.
- Associated Sensations:
- Intense Pruritus: Severe itching is the most common and often distressing symptom, which can range from mild to incapacitating.
- Burning Sensation: Some individuals report a burning or stinging sensation accompanying the itching.
- Tingling: A less common but reported sensation, particularly during the onset of a wheal.
- Angioedema Presentation:
- Deeper Swelling: Affects deeper layers of the skin (dermis and subcutaneous tissue) or submucosal tissues.
- Common Sites: Lips, eyelids, tongue, hands, feet, and genitalia are frequently affected.
- Appearance: Presents as large, often asymmetric, well-demarcated swelling, which may appear red or skin-colored.
- Symptoms: Typically causes a feeling of tightness, discomfort, or pain rather than itching.
- Duration: Usually resolves more slowly than wheals, often lasting 24-72 hours.
- Severe Manifestations: Swelling of the larynx or pharynx can obstruct the airway, leading to respiratory distress, a life-threatening emergency.
- Variations in Symptom Presentation:
- Acute Urticaria: Symptoms typically last less than six weeks, often associated with a clear trigger.
- Chronic Urticaria: Symptoms persist for more than six weeks, often without an identifiable cause (chronic spontaneous urticaria) or due to physical stimuli (chronic inducible urticaria).
- Confluent Urticaria: Multiple wheals merging to form large, erythematous, raised plaques.
- Annular Urticaria: Wheals forming distinct rings with central clearing.
- Figurate Urticaria: Complex patterns formed by coalescing and spreading wheals.
Signs of Urticaria allergy Pictures
The visual signs of urticaria allergy are highly dynamic and often diagnostic, providing crucial insights into the condition. When viewing signs of urticaria allergy pictures, one immediately notices the characteristic pattern of individual lesions known as wheals, but also the broader distribution and migratory nature of the rash across the body. The fundamental sign is the presence of elevated areas of skin, which are typically surrounded by a halo of erythema, particularly visible on lighter skin. These individual wheals are distinct and can appear singly or in clusters, sometimes forming intricate patterns. A key diagnostic sign observable in urticaria allergy pictures is dermatographism, a form of physical urticaria where stroking or scratching the skin results in a raised, red line or welt corresponding to the area of stimulation. This reaction typically occurs within minutes and resolves within 30-60 minutes. The migratory characteristic is another significant sign: while individual wheals resolve quickly, new ones continuously emerge in different locations, making the rash appear to “move” across the body. This phenomenon is critical for differentiating urticaria from other fixed skin eruptions. Common areas where these signs are evident include the trunk, extremities, face, and neck, though no body part is truly spared. On the face, particular attention is drawn to the periorbital area and lips, which are frequent sites for both wheals and angioedema. The overall skin surface might show varying degrees of redness or pallor depending on the underlying inflammation and individual skin tone. In chronic cases, the skin might show signs of excoriation from persistent scratching, although the individual wheals themselves do not leave marks. When observing signs of urticaria allergy pictures, one might also discern subtle textural changes, where the affected skin feels slightly firmer or edematous. In instances of chronic inducible urticaria, specific triggers like cold, heat, pressure, or water can elicit the appearance of wheals, providing direct visual evidence of the stimulus-response relationship. For example, in cold urticaria, exposure to cold temperatures will visibly induce wheals in the exposed area, a striking sign captured in related urticaria allergy images. Similarly, pressure urticaria will show deep, often painful, swellings in areas subjected to sustained pressure, like under tight clothing or straps. Recognizing the transient, migratory, and often intensely pruritic nature of these lesions, along with potential deep tissue swelling (angioedema), forms the cornerstone of identifying urticaria allergy symptoms based on visual signs.
- Primary Lesions (Wheals):
- Discrete or Confluent: Can appear as isolated bumps or merge into larger plaques.
- Erythematous Halo: Often surrounded by a wider area of redness, especially during acute flares.
- Palpable Elevation: Clearly felt as raised areas on the skin surface.
- Blanching: Essential sign, indicating dilation of superficial blood vessels that are still functional.
- Distribution Patterns:
- Generalized: Wheals can appear on any part of the body.
- Localized: In inducible urticaria, wheals may be localized to specific areas exposed to a trigger (e.g., pressure points, cold exposure).
- Symmetry: Often asymmetric, reflecting the migratory nature, but can be symmetric in widespread acute flares.
- Migratory Nature:
- Rapid Onset and Resolution: Individual lesions resolve quickly (within hours), but new ones appear constantly.
- Changing Landscape: The appearance of the rash shifts across the body, leading to a dynamic visual presentation.
- Dermatographism:
- Physical Sign: Visible red lines or wheals appearing along scratched or stroked areas of the skin.
- Mechanism: Localized mast cell degranulation triggered by mechanical friction.
- Associated Angioedema Signs:
- Deep Swelling: Noticeable swelling, especially around the eyes (periorbital), lips, and extremities.
- Asymmetry: Often affects one side of the face or one limb more than the other.
- Skin Color Changes: May be red, pale, or normal skin color over the swollen area.
- Lack of Pruritus: Typically lacks the intense itching of wheals, replaced by discomfort or pain.
- Signs of Specific Inducible Urticaria:
- Cold Urticaria: Wheals appearing minutes after rewarming skin exposed to cold temperatures.
- Heat Urticaria: Localized wheals upon exposure to localized heat.
- Pressure Urticaria: Deep, often painful, swellings appearing 4-12 hours after sustained pressure.
- Cholinergic Urticaria: Small, itchy wheals (1-3mm) surrounded by a red flare, typically on the trunk and upper extremities, triggered by exercise, heat, or emotional stress.
- Solar Urticaria: Wheals appearing minutes after exposure to UV or visible light, limited to exposed areas.
- Aquagenic Urticaria: Small, intensely itchy wheals upon contact with water, regardless of temperature.
- Secondary Signs:
- Excoriations: Scratch marks resulting from intense pruritus, particularly in chronic cases.
- Lichenification: Skin thickening in severe, chronic cases due to repeated scratching, though less common than in other chronic pruritic conditions.
Early Urticaria allergy Photos
Examining early urticaria allergy photos reveals the nascent stages of an allergic skin reaction, providing valuable insights into the rapid onset and evolution of hives. In the earliest moments, before full-blown wheals develop, the skin may present with subtle changes. Initially, you might observe localized erythema—small, reddish patches that signify an increase in blood flow to the area. These areas may feel slightly warmer to the touch. This initial redness is often accompanied by the very first sensation of itching, a tell-tale sign that a reaction is commencing. As the process unfolds, small, often indistinct, slightly raised bumps or papules begin to emerge within these erythematous zones. These early formations are usually few in number and scattered, lacking the confluent or extensive appearance seen in more advanced stages. What differentiates these from other insect bites or early rashes is their swift progression. Within minutes to an hour, these small papules visibly expand and elevate, transforming into the characteristic wheals. The central part of these early wheals may become edematous and slightly paler due to fluid accumulation, while the surrounding skin maintains a reddish hue. This rapid evolution from a simple red spot to a defined, raised, and intensely itchy wheal is a signature feature captured in early urticaria allergy photos. On various skin tones, these initial reactions can look slightly different; on lighter skin, the redness is usually more pronounced, while on darker skin, the early elevations might be more apparent, with subtle color changes that are darker than the surrounding skin or appear purplish. The speed at which these lesions develop and mature is a crucial diagnostic indicator. Unlike many other skin conditions that progress slowly over hours or days, early urticaria manifests with remarkable alacrity. The appearance of new lesions in previously unaffected areas, sometimes even before older ones have fully resolved, demonstrates the dynamic nature of urticaria allergy symptoms from their very beginning. Observing these initial stages in early urticaria allergy photos underscores the acute inflammatory response occurring in the skin’s superficial layers, driven by mast cell degranulation and histamine release, which leads to localized vasodilation and increased vascular permeability. This early visual evidence helps confirm the diagnosis and distinguishes it from other dermatological conditions that might present with early redness or bumps but lack the rapid evolution and transient nature characteristic of urticaria.
- Initial Erythema:
- Localized Redness: Small, distinct red patches appearing on the skin surface.
- Warmth: Affected areas may feel slightly warmer to the touch due to increased blood flow.
- First Pruritus:
- Onset of Itching: Often precedes visible skin changes, serving as an early warning sign.
- Intensity: Can range from mild to moderate initially, quickly escalating as wheals form.
- Emergence of Papules:
- Small Bumps: Development of tiny, slightly raised bumps or papules within the erythematous zones.
- Scattered Appearance: Initially few in number and often sparsely distributed.
- Color: May be pink, red, or match the surrounding skin tone on darker complexions.
- Rapid Evolution to Wheals:
- Quick Expansion: Within minutes, these papules enlarge and elevate.
- Central Edema: The center of the developing wheal often becomes swollen and may appear paler.
- Surrounding Flare: A reactive red flare often encircles the expanding wheal.
- Characteristic Features in Early Stages:
- Speed of Development: The most distinctive feature, with lesions appearing and maturing within 15-60 minutes.
- Lack of Uniformity: Early lesions may not all be the same size or shape, reflecting ongoing dynamic processes.
- Transient Nature (Early Indication): While not fully resolved, the initial subtle changes hint at the impermanence of the eruption.
- Appearance on Different Skin Tones:
- Lighter Skin: Early redness and pinkish-red bumps are more prominent.
- Darker Skin: Early elevations might be more discernible, with color variations appearing darker or purplish relative to the surrounding skin.
- Early Angioedema:
- Subtle Swelling: In cases where angioedema develops, early signs might be a mild puffiness or fullness in typical areas like lips or eyelids, accompanied by a tingling or tight sensation rather than itching.
- Rapid Increase: This swelling can quickly progress from subtle to noticeable within a short timeframe.
- Microscopic Changes (Underlying):
- Mast Cell Activation: The fundamental event, leading to the release of histamine and other mediators.
- Vascular Permeability: Increased leakage of fluid from blood vessels into the superficial dermis, causing edema.
- Vasodilation: Widening of blood vessels, contributing to the redness and warmth.
Skin rash Urticaria allergy Images
The skin rash in urticaria allergy images exhibits a remarkable diversity, reflecting the varied underlying mechanisms and individual responses to triggers. Fundamentally, the rash consists of wheals, but their configuration, distribution, and associated features can differ significantly. Acute urticaria typically presents as widespread, intensely itchy wheals that can appear suddenly and last for a few hours before fading, only to be replaced by new ones. These urticaria allergy rash images often show lesions that are erythematous, edematous, and sharply demarcated, with some exhibiting central pallor. The rash can be generalized, covering large areas of the trunk, limbs, and even the face. In contrast, chronic urticaria, lasting more than six weeks, might present with more persistent or recurring episodes of wheals, though individual lesions still resolve within 24 hours. The patterns seen in skin rash urticaria allergy images can be particularly telling for inducible forms of urticaria. For instance:
- Dermatographism: The most common inducible urticaria, visually manifested as linear wheals appearing precisely where the skin has been scratched or rubbed. These specific urticaria allergy rash images highlight the responsiveness of the skin to mechanical stimuli.
- Cold Urticaria: Wheals that develop specifically on areas of the skin exposed to cold temperatures, or during rewarming after cold exposure. These photos might show lesions on hands after holding a cold drink, or on the face after being outdoors in cold weather.
- Heat Urticaria: Less common, but presents as localized wheals on skin exposed to heat.
- Delayed Pressure Urticaria: This form shows deep, tender, and often painful swellings that appear 4-12 hours after sustained pressure on the skin. Urticaria allergy rash images of this type might show deep welts under bra straps, waistbands, or where one has leaned.
- Solar Urticaria: A striking presentation where wheals appear rapidly on sun-exposed skin, typically within minutes of light exposure, and resolve upon removal from sunlight. These pictures emphasize the photosensitive nature of the rash.
- Cholinergic Urticaria: Characterized by very small (1-3mm) wheals surrounded by a prominent red flare, appearing in response to increased body temperature from exercise, hot baths, or stress. These lesions are typically widespread on the trunk and upper extremities.
- Aquagenic Urticaria: A rare form where very small, intensely itchy wheals develop within minutes of contact with water, regardless of its temperature.
Beyond these inducible forms, the general appearance of the skin rash in urticaria allergy images can also show variations in color. While often red, on darker skin tones, the wheals might appear more purplish, darker brown, or simply as elevated areas contrasting with the surrounding skin. The texture can appear smooth and taut due to underlying edema. In severe cases, particularly with angioedema, the rash can encompass significant facial swelling, including eyelids and lips, which might distort facial features, a serious manifestation captured in severe urticaria allergy images. Repeated scratching in chronic conditions can lead to secondary changes like excoriations (scratch marks), but individual urticarial lesions themselves do not scar. The fleeting nature of individual lesions, even in a widespread outbreak, is a constant across all types of urticaria allergy rash images, reiterating the dynamic and non-destructive nature of the lesions themselves. Understanding these diverse presentations is crucial for accurate identification and management of urticaria allergy symptoms, guiding appropriate treatment strategies and patient education on triggers.
- Acute Urticaria Rash Characteristics:
- Widespread Distribution: Often affects large areas of the body, including trunk, limbs, and face.
- Vibrant Erythema: Typically bright red, especially on lighter skin, with possible central pallor.
- Ephemeral Lesions: Individual wheals resolve within 24 hours, but new ones continuously appear.
- Intense Itching: The most prominent accompanying symptom.
- Chronic Urticaria Rash Characteristics:
- Recurrent Episodes: Similar appearance to acute urticaria but occurring persistently for more than six weeks.
- Variable Intensity: Flares can range from mild to severe over time.
- Impact of Scratching: May show signs of excoriation, especially in chronic spontaneous urticaria due to prolonged pruritus.
- Physical Urticaria Rash Manifestations (Inducible Forms):
- Dermatographism: Linear wheals on areas of mechanical friction or scratching.
- Cold Urticaria: Wheals and/or angioedema on cold-exposed or rewarmed skin (e.g., swimming, cold air, holding ice).
- Heat Urticaria: Localized wheals on skin exposed to external heat sources.
- Delayed Pressure Urticaria: Deep, often painful, swellings developing hours after sustained pressure (e.g., from tight clothing, sitting).
- Solar Urticaria: Wheals and erythema confined to sun-exposed skin, appearing rapidly after UV/visible light exposure.
- Cholinergic Urticaria: Characterized by small (1-3mm), itchy wheals surrounded by a large red flare (erythematous halo), triggered by sweating (exercise, hot showers, emotional stress).
- Aquagenic Urticaria: Minute, intensely pruritic wheals upon contact with water, regardless of temperature.
- Vibratory Urticaria/Angioedema: Deep, painful swellings or wheals induced by vibratory stimuli (e.g., jackhammer use, vibrating massagers).
- Angioedema in Urticaria Rash Images:
- Deep Swelling: Often appears as asymmetric swelling of lips, eyelids, tongue, hands, or feet.
- Associated Symptoms: May cause discomfort, tightness, or pain rather than itching.
- Life-threatening Potential: Swelling of the larynx or pharynx can be visible as severe swelling of the neck/throat area in extreme cases.
- Color and Texture Variations:
- Erythematous to Purplish: Depending on skin tone, wheals can range from bright red to darker purplish or brown hues.
- Smooth and Taut: The surface of the wheals typically appears smooth due to the underlying edema.
- Configurations of the Rash:
- Annular: Ring-shaped lesions with central clearing.
- Serpiginous: Snake-like or wavy patterns formed by coalescing wheals.
- Targetoid: Rarely, wheals can have a target-like appearance, though this is more characteristic of erythema multiforme.
- Confluent: Multiple wheals merging to form large, irregular plaques.
- Differential Features (Distinguishing from other rashes):
- Lack of Vesicles/Bullae: Urticarial rashes typically do not blister or form fluid-filled sacs.
- Absence of Scales/Crusts: Not typically present on primary urticarial lesions, distinguishing them from conditions like eczema or fungal infections.
- No Residual Pigmentation: Unlike some inflammatory rashes, urticaria usually resolves without leaving permanent color changes or scars. (Exception: Urticarial vasculitis might leave purpuric changes and hemosiderin deposition).
Urticaria allergy Treatment
Effective urticaria allergy treatment focuses on alleviating symptoms, preventing new wheals and angioedema, and improving the patient’s quality of life. The approach to urticaria allergy treatment is typically multi-faceted, starting with identifying and avoiding known triggers where possible, though this is often difficult, especially in chronic spontaneous urticaria.
The cornerstone of symptomatic relief for urticaria allergy symptoms pictures is the use of antihistamines.
First-Line Pharmacological Treatments:
- Second-Generation H1-Antihistamines: These are the preferred initial treatment for both acute and chronic urticaria due to their efficacy and reduced sedative effects compared to older antihistamines. They work by blocking the action of histamine, a key mediator in the development of wheals and itching.
- Examples: Loratadine, desloratadine, cetirizine, levocetirizine, fexofenadine, rupatadine, bilastine.
- Dosage: Often prescribed at standard doses initially, but in chronic or persistent cases, dosages can be increased up to four times the standard dose under medical supervision to achieve better symptom control, based on guidelines for urticaria allergy treatment.
- Mechanism: Competitively inhibit histamine at H1 receptors, reducing vascular permeability, vasodilation, and pruritus, thereby diminishing the appearance and severity of the skin rash urticaria allergy images.
Second-Line and Adjunctive Pharmacological Treatments:
- First-Generation H1-Antihistamines: While largely supplanted by newer agents, these can be used for their sedative properties, especially at night to help with sleep disruption caused by severe itching. However, their use is limited by side effects such as drowsiness, dry mouth, and cognitive impairment.
- Examples: Diphenhydramine, hydroxyzine, chlorpheniramine.
- Caution: Not recommended for long-term daily use due to side effect profile, especially in the elderly.
- H2-Antihistamines (H2-Blockers): While primarily used for gastric acid reduction, they can be added to H1-antihistamines for additive effect in some patients, though their independent efficacy in urticaria is limited.
- Examples: Ranitidine (withdrawn in some markets), famotidine, cimetidine.
- Mechanism: Block histamine at H2 receptors, potentially affecting some aspects of the vascular response in the skin.
- Leukotriene Receptor Antagonists (LTRAs): These medications, such as montelukast or zafirlukast, can be used as an add-on therapy, particularly when antihistamines alone are insufficient, offering an alternative pathway in urticaria allergy treatment strategies. They target leukotrienes, which also contribute to inflammation and swelling.
- Oral Corticosteroids: For severe, acute flares of urticaria or angioedema that are unresponsive to high-dose antihistamines, a short course of oral corticosteroids (e.g., prednisone) may be prescribed. These are potent anti-inflammatory agents that can quickly suppress the immune response.
- Usage: Typically used for short durations (3-7 days) to avoid long-term side effects. Not recommended for chronic urticaria due to significant adverse effects with prolonged use.
- Effectiveness: Can rapidly reduce the redness, swelling, and itching seen in severe urticaria allergy symptoms pictures.
- Omalizumab (Xolair): For chronic spontaneous urticaria (CSU) that remains unresponsive to high-dose H1-antihistamines, omalizumab is a highly effective biologic therapy. It is a monoclonal antibody that targets IgE, reducing free IgE levels and subsequently decreasing mast cell activation.
- Administration: Administered via subcutaneous injections, typically every 4 weeks.
- Efficacy: Can lead to complete or significant symptom control in a large percentage of refractory CSU patients, demonstrating a clear improvement in the appearance of urticaria allergy photos.
- Cyclosporine: An immunosuppressant agent that may be considered for severe, refractory chronic urticaria when other treatments, including omalizumab, have failed. Its use is limited by potential serious side effects, including nephrotoxicity and hypertension.
- Other Immunosuppressants: In very rare and extremely severe cases, other immunosuppressive drugs such as methotrexate or tacrolimus may be considered, always under strict specialist supervision due to their side effect profiles.
Non-Pharmacological and Lifestyle Interventions:
- Trigger Avoidance: If specific triggers (e.g., certain foods, medications, physical stimuli like cold or pressure) are identified through careful patient history or testing, avoiding them is a primary preventive measure against the onset of urticaria allergy symptoms.
- Cool Compresses/Baths: Applying cool compresses or taking cool (not cold) baths can help soothe itchy skin and reduce inflammation.
- Loose Clothing: Wearing loose-fitting, cotton clothing can minimize irritation and prevent the aggravation of symptoms, especially in forms like pressure urticaria.
- Topical Agents: While less effective for generalized urticaria, topical menthol creams, calamine lotion, or low-potency topical corticosteroids can offer temporary relief for localized itching.
- Stress Management: Stress can exacerbate chronic urticaria in some individuals, so stress reduction techniques may be beneficial.
Emergency Treatment for Severe Angioedema:
- Epinephrine (Adrenaline): For angioedema involving the airway (e.g., swelling of the tongue or throat leading to difficulty breathing), emergency administration of intramuscular epinephrine is crucial and potentially life-saving. This is critical for severe urticaria allergy symptoms pictures that involve the face and neck.
- Emergency Medical Attention: Any signs of difficulty breathing, dizziness, or widespread severe swelling require immediate emergency medical care.
It is imperative for individuals experiencing urticaria allergy symptoms pictures to consult a healthcare professional for an accurate diagnosis and a personalized urticaria allergy treatment plan. Self-medication or prolonged use of potent medications without medical guidance can be harmful. Regular follow-up with a specialist is often necessary, especially for chronic forms of urticaria, to adjust treatments and ensure optimal symptom control and improved quality of life.