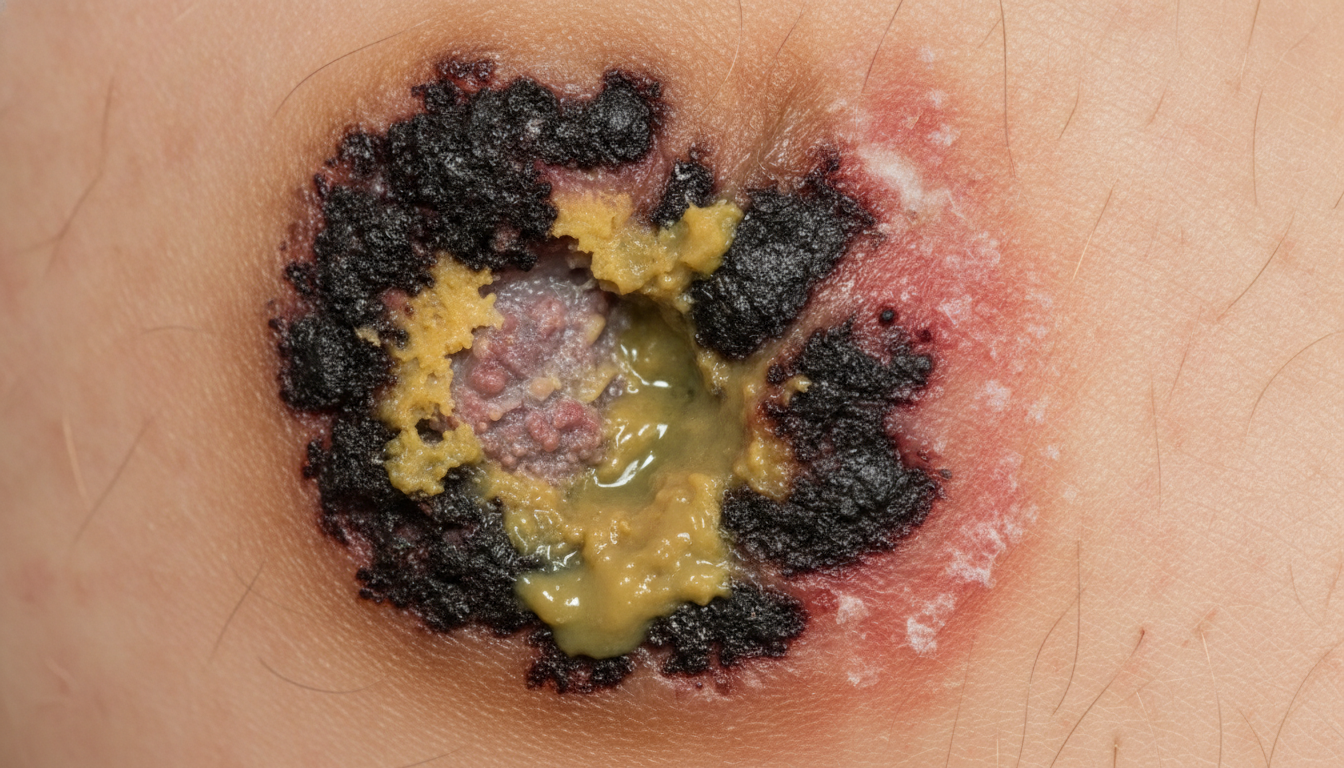
This detailed guide provides a comprehensive overview of Trophic ulcer on the leg symptoms pictures, offering crucial insights for recognizing and understanding this complex condition. We delve into the observable signs, early indicators, and associated skin changes, emphasizing visual and symptomatic characteristics to aid in identification.
Trophic ulcer on the leg Symptoms Pictures
Recognizing the distinct trophic ulcer on the leg symptoms pictures is paramount for timely intervention and effective management. Trophic ulcers are chronic wounds that fail to heal due to underlying pathologies, primarily affecting the lower extremities. The appearance can vary significantly based on the etiology (venous, arterial, neuropathic, or mixed) and the stage of progression. However, common symptomatic and visual characteristics are shared across many types, making identification possible through careful observation of the wound bed, surrounding skin, and patient complaints.
Key symptomatic indicators and visual signs to look for include:
- Wound Appearance and Characteristics:
- Irregular Shape and Size: Trophic ulcers often present with an irregular, non-circular shape, which can range from small, superficial lesions to large, deep wounds. The edges may be ill-defined or punched-out, depending on the cause. Leg ulcer appearance can be highly variable, ranging from pinpoint lesions to several centimeters in diameter.
- Depth of the Ulcer: Depth can range from superficial epidermal loss to deep penetration involving subcutaneous tissue, muscle, or even bone. Deep ulcers are typically more painful and have a higher risk of infection, often presenting with significant tissue loss. Deep leg ulcer symptoms frequently include exposure of underlying structures.
- Wound Bed Color: The color of the wound bed provides crucial information regarding its viability and healing progress.
- Red/Pink: Indicates healthy granulation tissue, suggesting good vascularity and healing potential. This tissue is typically moist and granular.
- Yellow/White: Often points to the presence of slough, which is devitalized, moist, stringy tissue needing debridement to expose healthy tissue.
- Black/Brown: Signifies necrotic tissue (eschar), which is dead, hardened tissue that must be removed for healing to occur. This is a common finding in arterial leg ulcer symptoms and can often be dry and leathery.
- Green/Pus: Suggests an active bacterial infection, often accompanied by a foul odor and increased exudate. Infected leg ulcer symptoms frequently include purulent exudate.
- Exudate (Drainage): The amount and type of fluid draining from the ulcer are significant indicators of the wound’s condition.
- Serous: Clear, watery fluid; normal in small amounts during the inflammatory phase.
- Sero-sanguinous: Pink-tinged, watery fluid; indicates the presence of blood, often normal with healthy granulation.
- Purulent: Thick, opaque, yellow, green, or brown discharge; a strong indicator of infection, often with a distinct odor.
- Sanguinous: Bright red, bloody drainage, potentially indicating trauma to blood vessels.
- Odor: A strong, foul, or putrid odor usually indicates infection or significant tissue necrosis. Odorous leg ulcer is a clear sign of bacterial proliferation and often requires immediate attention.
- Temperature: The temperature of the skin immediately around the ulcer can vary; warmth may indicate inflammation or infection, while coolness may suggest poor circulation.
- Pain Levels Associated with Trophic Ulcers: The character and intensity of pain are crucial in differentiating ulcer types.
- Venous Ulcers: Often described as dull aching, a feeling of heaviness, or throbbing pain, which is typically relieved by elevation of the leg. Pain may worsen with prolonged standing or dependency. Venous ulcer symptoms typically involve less severe pain than arterial ulcers, but can be exacerbated by edema.
- Arterial Ulcers: Typically very painful, often described as severe, burning, or throbbing, especially at night or when the leg is elevated (rest pain). Pain may be partially relieved by dangling the leg (dependency) due to gravity assisting blood flow. This is a hallmark of ischemic leg ulcer symptoms and indicates critical limb ischemia.
- Neuropathic (Diabetic) Ulcers: Often painless due to nerve damage (peripheral neuropathy), which is a significant risk factor as patients may not notice the ulcer until it’s advanced or infected. However, surrounding infection or ischemia can cause pain. Diabetic foot ulcer symptoms are characterized by a lack of protective sensation.
- Location on the Leg: The site of ulceration is a key diagnostic feature.
- Venous Ulcers: Most commonly found on the medial malleolus (inner ankle) and lower calf, in the “gaiter” area. They rarely affect the foot or toes directly unless associated with severe edema. Location of venous leg ulcers is highly specific.
- Arterial Ulcers: Frequently occur on the toes, heels, and anterior tibial area (shin), or anywhere subjected to pressure where blood flow is compromised. Often found at distal points furthest from the heart. Arterial leg ulcer locations are typically on pressure points or bony prominences.
- Neuropathic Ulcers: Predominantly found on pressure points of the foot, such as the plantar surface of the metatarsal heads, heels, and tips of the toes, corresponding to areas of repetitive trauma in insensate feet. Diabetic ulcer location correlates with high-pressure areas.
- Surrounding Skin Changes: The appearance of the skin immediately surrounding the ulcer and on the rest of the limb provides critical diagnostic clues.
- Venous Insufficiency:
- Edema: Swelling of the ankle and lower leg, often pitting, which may resolve with elevation.
- Hyperpigmentation (Hemosiderin Staining): Brownish discoloration due to iron deposits from extravasated red blood cells, giving the skin a “rusty” appearance. Known as venous stasis dermatitis.
- Lipodermatosclerosis: Hardening and thickening of the skin and subcutaneous tissue, often giving the leg an “inverted champagne bottle” or “wooden” appearance. This indicates severe chronic venous insufficiency.
- Atrophie Blanche: White, atrophic, often star-shaped scars, typically surrounded by telangiectasias and hyperpigmentation, indicative of severe microcirculatory damage. These areas are fragile and prone to re-ulceration.
- Eczematous changes: Red, itchy, scaly skin around the ulcer, often weeping, characteristic of stasis eczema.
- Arterial Insufficiency:
- Pallor: Pale, shiny, thin, hairless skin on the affected limb, often cool to the touch.
- Dependent Rubor: Redness that develops when the leg is in a dependent position, due to dilated arterioles attempting to compensate for ischemia.
- Coolness: The affected limb feels noticeably cooler to the touch compared to the unaffected limb or proximal areas.
- Diminished/Absent Pulses: Reduced or absent pedal (dorsalis pedis and posterior tibial) pulses are a critical sign.
- Delayed Capillary Refill: More than 3 seconds for color to return after blanching the skin.
- Neuropathic Conditions (Diabetes):
- Callus Formation: Thick calluses often precede or surround ulcers due to repetitive trauma on insensate skin, acting as a foreign body.
- Dry, Cracked Skin (Xerosis): Due to autonomic neuropathy affecting sweat glands, leading to compromised skin barrier function.
- Charcot Foot Deformity: Bone and joint destruction leading to severe foot deformities, altered biomechanics, and increased pressure points.
- Warmth: The neuropathic foot may paradoxically feel warm due to autonomic neuropathy leading to vasodilation.
- Venous Insufficiency:
Understanding these specific trophic ulcer on the leg symptoms pictures allows for better differentiation and supports a more targeted approach to diagnosis and subsequent treatment. Each visual cue and patient symptom tells a part of the story, essential for managing these complex wounds. Early identification of these leg ulcer symptoms is key to preventing complications and promoting efficient healing.
Signs of Trophic ulcer on the leg Pictures
Beyond the patient’s subjective symptoms, specific signs of trophic ulcer on the leg pictures are objectively observable indicators that a healthcare professional can assess. These signs provide critical information about the underlying etiology, the severity of the condition, and the overall health of the affected limb. Detailed examination of these signs is crucial for proper diagnosis and guiding the management plan for any chronic leg ulcer. A systematic approach to assessment ensures no critical detail is missed, leading to a more accurate understanding of the patient’s pathology.
Observable signs encompass a broader range of clinical findings, including:
- Vascular Assessment Signs: These signs are critical for determining the adequacy of blood flow to the limb.
- Palpable Pulses:
- Absent or Diminished Pulses: A strong indicator of peripheral arterial disease (PAD). Dorsalis pedis and posterior tibial pulses should be assessed for strength and presence. This is a primary sign in arterial leg ulcer signs and necessitates further investigation into arterial supply.
- Normal or Bounding Pulses: Typically seen in venous insufficiency or neuropathic ulcers, as arterial inflow is generally preserved. However, in advanced diabetic neuropathy, calcified arteries may give a falsely strong pulse.
- Capillary Refill Time (CRT):
- Prolonged CRT (>3 seconds): Suggests impaired arterial perfusion, common in PAD. This is a quick and non-invasive way to assess microvascular flow and is often a key ischemic ulcer sign. A CRT of over 5 seconds is highly concerning.
- Normal CRT: Usually found in venous or neuropathic ulcers, assuming adequate circulation.
- Ankle-Brachial Index (ABI):
- Low ABI (<0.9): Confirms significant arterial disease and is a critical diagnostic sign for arterial insufficiency ulcers. An ABI below 0.5 indicates severe ischemia.
- Normal ABI (0.9-1.3): Suggests absence of significant PAD in non-diabetic individuals.
- High ABI (>1.3): May indicate vessel calcification, often seen in diabetic patients, which can give falsely elevated readings and necessitates further investigation (e.g., toe-brachial index or duplex ultrasound) for true arterial status.
- Venous Reflux: Assessed via duplex ultrasound, which reveals incompetent valves in the superficial or deep venous system. This is a definitive sign for venous ulcer development, identifying the source of venous hypertension.
- Elevation Pallor and Dependent Rubor: The limb becomes pale on elevation and turns a dusky red when dependent, indicating severe arterial insufficiency.
- Palpable Pulses:
- Skin and Tissue Condition Signs: These provide visual clues about the local environment and underlying chronic changes.
- Edema:
- Pitting Edema: Common in venous insufficiency, where pressing a finger into the skin leaves an indentation. Venous edema signs are often progressive throughout the day and can vary in severity.
- Non-Pitting Edema: Can be seen in lymphatic obstruction or severe chronic venous disease with fibrotic changes, indicating a more chronic and hardened swelling.
- Temperature Differences:
- Coolness of the Affected Limb: A classic sign of arterial insufficiency, indicating reduced blood flow. Cold limb symptoms are indicative of poor circulation and a risk of critical limb ischemia.
- Warmth Around the Ulcer: May suggest inflammation or localized infection. Diffuse warmth without redness might also be seen in early Charcot neuropathy.
- Skin Texture and Color Changes:
- Hemosiderin Staining: Permanent brownish discoloration on the lower leg, typical of chronic venous insufficiency. This distinctive pigmentation is a key sign of chronic venous leg ulcers.
- Lipodermatosclerosis: Induration and fibrosis of subcutaneous tissue, leading to a hardened, reddish-brown appearance, sometimes giving the limb an “inverted champagne bottle” shape. A severe venous disease sign.
- Atrophie Blanche: Small, white, star-shaped, often painful scars surrounded by telangiectasias (spider veins) and hyperpigmentation, a sign of microvascular damage.
- Shiny, Thin, Hairless Skin: Characteristic of chronic arterial insufficiency due to malnutrition of skin cells. Arterial skin changes are often severe and progressive.
- Cyanosis or Pallor on Elevation: Bluish discoloration or extreme paleness of the limb when elevated, followed by dependent rubor, are strong signs of critical limb ischemia.
- Xerosis (Dry Skin) and Fissures: Especially common in diabetic neuropathy, leading to cracks that serve as entry points for infection.
- Presence of Calluses: In neuropathic ulcers, thick calluses often form over pressure points before or around the ulcer, indicating repeated mechanical stress on an insensate foot. This is a defining diabetic neuropathic ulcer sign.
- Deformities:
- Hammer Toes, Bunions: Common foot deformities that create pressure points and increase the risk of ulceration, particularly in diabetic patients due to altered foot mechanics.
- Charcot Arthropathy: A severe neuro-osteoarthropathy causing progressive destruction of bones and joints, leading to significant foot deformities and altered weight-bearing, a major diabetic foot complication sign.
- Edema:
- Wound Bed and Exudate Signs: Direct observation of the ulcer itself.
- Granulation Tissue: Healthy, pink/red, bumpy tissue indicating healing. Often appears moist and forms a strong bed.
- Slough: Yellow or white, soft, stringy, non-viable tissue that needs removal to allow healing.
- Eschar: Black, hard, leathery necrotic tissue, which acts as a physical barrier to healing and a breeding ground for bacteria.
- Pus/Purulent Exudate: Thick, often colored, and odorous discharge, a definitive sign of infection in leg ulcers.
- Undermining/Tunneling: Extension of the wound under the skin edges or into deeper tissues, indicating extensive tissue destruction and hindering healing by creating dead spaces.
- Epibole (Rolled Edges): When the skin edges roll inward, preventing epithelial cells from migrating across the wound bed, indicating stalled healing. These edges are often thick and calloused.
- Periwound Maceration: Softening and whitening of the skin surrounding the ulcer due to excessive moisture, increasing risk of skin breakdown.
- Periwound Excoriation/Erythema: Redness, scratching, or breakdown of the skin around the ulcer, often due to irritation from exudate or contact dermatitis.
The systematic assessment of these signs of trophic ulcer on the leg pictures provides a comprehensive clinical picture, essential for determining the underlying cause and formulating an effective treatment strategy. Each sign contributes to a holistic understanding of the patient’s condition, crucial for managing chronic leg wounds and preventing further complications, including infection, limb loss, and impaired quality of life.
Early Trophic ulcer on the leg Photos
Early identification of early trophic ulcer on the leg photos and their precursor signs is critical for preventing the progression to full-blown, difficult-to-treat chronic wounds. Before a visible break in the skin occurs, or when the ulcer is still very superficial, the body often sends warning signals through subtle skin changes, unusual sensations, and minor irritations. These early indicators are crucial for intervention and preventing severe leg ulcer development, making vigilant self-monitoring and professional examination vital. Recognizing these subtle shifts can mean the difference between minor intervention and prolonged, complex wound care.
Recognizing these initial signs, sometimes referred to as pre-ulcerative changes, allows for prompt medical attention and lifestyle adjustments. Key early indicators include:
- Subtle Skin Discoloration: These color changes are often the first visible warnings.
- Redness (Erythema): Persistent redness in an area, especially around the ankles or lower calves, that does not resolve with elevation or after pressure is relieved. This can indicate inflammation, early venous stasis, or impending pressure injury.
- Brownish or Rust-Colored Patches: Early hemosiderin staining, appearing as small, faint spots or diffuse patches of brown discoloration. This is an early sign of blood leakage from capillaries due to venous hypertension and red blood cell breakdown. Early venous insufficiency signs often include this subtle pigmentation.
- Dusy or Mottled Appearance: A purplish or reddish-blue discoloration, particularly in dependent positions, suggesting impaired arterial flow (cyanosis) or severe venous congestion. This color change may fluctuate.
- Pallor (Paleness): Localized paleness in an area of the skin, potentially indicating reduced blood supply. This can be more noticeable on elevation of the limb.
- Hyperemia: A brighter red color that appears after brief pressure, indicating reactive hyperemia often seen in pressure areas, which can precede ulceration.
- Skin Texture and Integrity Changes: These indicate a weakening of the skin barrier.
- Dry, Scaly, or Itchy Skin (Pruritus): Often precedes venous ulcers. The skin may feel thin, fragile, or look like it’s cracking. This is an early manifestation of stasis dermatitis, where the skin becomes highly sensitive and prone to breakdown from scratching.
- Localized Swelling (Edema): Intermittent or persistent swelling, particularly around the ankles. While not yet pitting, this indicates fluid accumulation and increased pressure within the tissues. Early leg swelling is a significant warning sign, especially if unilateral.
- Shiny or Taut Skin: The skin may appear stretched and shiny due to underlying edema or diminished tissue nourishment, particularly in arterial insufficiency, where skin becomes atrophic.
- Hair Loss: Thinning or complete loss of hair on the lower legs and feet can be an early sign of peripheral arterial disease, indicating poor circulation and reduced nutrient supply to hair follicles.
- Thickening of Toenails: Discolored, brittle, or thickened toenails (onychomycosis or onychogryphosis), especially when accompanied by other circulatory issues, can point to poor peripheral perfusion and reduced nail plate nutrition.
- Induration: Localized hardening or firming of the skin or subcutaneous tissue, indicating inflammation or early fibrotic changes.
- Sensory Symptoms: These are subjective but crucial for patient reporting.
- Heaviness or Aching in Legs: A common early symptom of venous insufficiency, especially after prolonged standing or sitting. Typically relieved by elevation.
- Cramping or Fatigue (Claudication): Pain, aching, or cramping in the calf, thigh, or buttocks during exercise that consistently subsides with rest. This is a classic early sign of peripheral arterial disease. Early PAD symptoms are often overlooked or attributed to aging.
- Burning or Tingling Sensations (Paresthesias): Can indicate nerve irritation or damage, particularly in early stages of diabetic neuropathy or nerve compression.
- Decreased Sensation (Numbness): Reduced ability to feel pain, temperature, or pressure, especially in the feet. This is a critical early warning sign for diabetic foot ulcers, as protective sensation is lost, making injury unnoticed.
- Increased Sensitivity (Hyperesthesia): Paradoxically, some areas might become overly sensitive to touch or pressure due to nerve involvement or inflammation, preceding an ulcer.
- Restlessness in legs: A feeling of needing to move the legs, often related to discomfort from venous congestion or restless leg syndrome, which can complicate management.
- Pre-Ulcerative Lesions and Minor Trauma: These are physical changes that signal impending breakdown.
- Blisters or Vesicles: Small fluid-filled lesions can develop due to impaired circulation, friction, pressure, or minor burns, and can easily rupture into ulcers.
- Minor Cuts or Abrasions that Don’t Heal: Any small break in the skin that takes an unusually long time to close or appears to worsen is a significant red flag for compromised tissue viability. Non-healing wounds are a critical early indicator of an underlying issue.
- Persistent Red Spots or Pressure Marks: Areas that remain red, discolored, or show signs of blanching/non-blanching after pressure has been relieved, indicating impending tissue breakdown.
- Callus Formation: Particularly on the sole of the foot or over bony prominences. While calluses are common, abnormally thick or rapidly forming calluses, especially in individuals with neuropathy, indicate excessive pressure and high risk of underlying ulceration.
- Fissures or Cracks: Deep cracks, particularly on dry skin (xerosis) in individuals with diabetes, can serve as entry points for bacteria and develop into ulcers.
- Hematoma/Ecchymosis: Blood collections under the skin from minor trauma, which may break down into ulcers, especially with poor circulation.
Awareness of these early trophic ulcer on the leg photos and preceding signs empowers individuals and healthcare providers to take proactive steps. Early intervention, including addressing the underlying cause and meticulous skin care, significantly improves outcomes and prevents the progression to more severe, chronic wounds. Don’t ignore these subtle leg ulcer warning signs; they are the body’s way of signaling a need for attention before a more serious problem develops.
Skin rash Trophic ulcer on the leg Images
The presence of a skin rash trophic ulcer on the leg images can be both a precursor to ulceration and a significant complication, often intensifying patient discomfort and complicating treatment. Various forms of dermatitis, infections, or inflammatory skin conditions can either directly lead to skin breakdown or exacerbate the existing compromised skin integrity around a developing or established trophic ulcer. Understanding these associated skin rashes is vital for accurate diagnosis and comprehensive management of leg skin conditions, as they often require specific treatments beyond standard wound care. These rashes can be indicators of underlying systemic conditions or local reactions to treatments or environmental factors.
Common skin rashes and dermatological conditions observed in conjunction with trophic ulcers include:
- Stasis Dermatitis (Venous Eczema):
- Appearance: Red, inflamed, scaly, and intensely itchy skin, primarily on the lower legs and ankles, often in the “gaiter” area. It can be wet and weeping (acute) or dry, flaky, and thickened (chronic). Often precedes or surrounds venous ulcers.
- Symptoms: Intense pruritus (itching), burning sensation, swelling, and pain. The skin may become hardened (lipodermatosclerosis) and discolored (hyperpigmented) over time due to chronic inflammation and iron deposition.
- Mechanism: Caused by chronic venous insufficiency, leading to pooling of blood in the lower extremities, increased capillary pressure, and leakage of fluid and red blood cells into the surrounding tissue. This extravasation triggers an inflammatory and allergic response.
- Relevance to Ulcers: The inflamed, fragile, and often excoriated skin of stasis dermatitis is highly susceptible to minor trauma, easily breaking down to form venous ulcers. It is a defining feature of venous leg ulcer skin changes and often complicates healing.
- Contact Dermatitis:
- Appearance: Localized redness, itching, blistering, and weeping, typically in the area of contact with an irritant or allergen. The pattern often mirrors the shape of the offending agent.
- Symptoms: Severe itching, burning, pain, and sometimes stinging.
- Mechanism: An allergic reaction (e.g., to wound care products like dressings, adhesives, topical antibiotics such as neomycin, or antiseptics like iodine) or irritation (e.g., from prolonged moisture, harsh soaps, or excessive exudate).
- Relevance to Ulcers: Can occur around any type of ulcer, mimicking infection or exacerbating the wound. It complicates wound healing by causing additional skin damage, inflammation, and discomfort, leading to a vicious cycle of scratching and further breakdown. Allergic reaction leg skin is a frequent complication in chronic wound care.
- Cellulitis:
- Appearance: A spreading area of intense redness, warmth, swelling, and tenderness, often with poorly defined borders. May have associated systemic symptoms like fever, chills, and malaise. Streaking (lymphangitis) may be present.
- Symptoms: Intense pain, throbbing, warmth, and systemic signs of infection.
- Mechanism: A bacterial infection (most commonly Streptococcus pyogenes or Staphylococcus aureus) of the dermis and subcutaneous tissue. Skin breakdown from an ulcer, even a minor one, provides an entry point for bacteria.
- Relevance to Ulcers: A common and serious complication of trophic ulcers, especially venous and diabetic ulcers, potentially leading to osteomyelitis or sepsis. It requires prompt systemic antibiotic treatment to prevent widespread infection. Infected leg ulcer rash often presents as cellulitis and requires immediate attention.
- Fungal Infections (Tinea Pedis/Cruris, Candidiasis):
- Appearance: Red, scaly, itchy patches, often with clear, raised borders, sometimes blistering or macerated. Can appear between toes (athlete’s foot), in skin folds (groin, under pannus), or anywhere with warmth and moisture.
- Symptoms: Itching, burning, peeling skin, malodor.
- Mechanism: Caused by dermatophytes (e.g., Tinea species) or yeasts (e.g., Candida albicans) thriving in warm, moist environments. Compromised immunity, poor hygiene, and presence of chronic edema or exudate can contribute.
- Relevance to Ulcers: While not directly causing ulcers, fungal infections can compromise skin integrity, leading to scratching and secondary bacterial infections, which can then predispose to ulceration or complicate existing ulcers. They also add to patient discomfort and can delay healing. Fungal rash on leg can be debilitating and easily misdiagnosed.
- Eczematous Rashes (General and Asteatotic Eczema):
- Appearance: Broader category including stasis dermatitis, but also atopic eczema or asteatotic (xerotic) eczema. Characterized by inflamed, itchy, dry, and often thickened or cracked skin. Asteatotic eczema appears as “cracked pavement” or “crazy paving” pattern.
- Symptoms: Chronic itching, dryness, occasional weeping, and discomfort.
- Mechanism: Genetic predisposition, environmental triggers, chronic irritation, or severe dryness and impaired skin barrier function. Common in elderly patients with dry skin.
- Relevance to Ulcers: Weakened skin barrier due to chronic eczema makes the leg more vulnerable to injury and ulcer formation. Managing general eczema and leg ulcers is important for healing, as uncontrolled itching can lead to excoriations and secondary infections.
- Purpura and Petechiae:
- Appearance: Purplish or reddish-brown spots that do not blanch under pressure. Petechiae are smaller (pinpoint), purpura are larger. Ecchymoses are larger bruises.
- Symptoms: Usually asymptomatic unless due to inflammation or underlying vasculitis causing pain.
- Mechanism: Extravasation of red blood cells from capillaries, often due to capillary fragility, venous hypertension, trauma, or vasculitis (inflammation of blood vessels).
- Relevance to Ulcers: Can be seen around venous ulcers as part of hemosiderin staining or in vasculitic ulcers where direct vessel damage causes the lesions. Severe purpura can lead to skin necrosis and subsequent ulceration (e.g., warfarin-induced skin necrosis, disseminated intravascular coagulation). Vascular rash on legs requires careful assessment as it may indicate a systemic disease.
- Panniculitis:
- Appearance: Erythematous, tender nodules or plaques in the subcutaneous fat, often on the lower legs.
- Symptoms: Pain, tenderness, warmth, swelling. Can resolve with hyperpigmentation or atrophy.
- Mechanism: Inflammation of the subcutaneous fat. Can be secondary to venous insufficiency (e.g., lipodermatosclerosis), trauma, infection, or systemic disease.
- Relevance to Ulcers: The inflammation and fibrosis associated with panniculitis, particularly lipodermatosclerosis, can lead to chronic skin hardening and predispose to ulceration.
The presence of any skin rash trophic ulcer on the leg images necessitates a thorough evaluation to differentiate between primary dermatological conditions, infectious processes, and reactive skin changes. Accurate identification of these associated rashes is critical for implementing appropriate topical and systemic treatments, thereby supporting wound healing and improving patient comfort. Ignoring these skin changes can significantly impede ulcer resolution and lead to chronic complications of leg wounds with rash, potentially exacerbating the underlying ulcer and delaying recovery.
Trophic ulcer on the leg Treatment
Effective trophic ulcer on the leg treatment is a multidisciplinary endeavor, focusing not only on healing the open wound but also on addressing the underlying pathology that caused the ulcer. The treatment strategy for leg ulcers is highly individualized, depending on the etiology (venous, arterial, neuropathic, or mixed), the size and depth of the ulcer, the presence of infection, and the overall health of the patient. The primary goals are to promote wound closure, prevent infection, manage pain, and prevent recurrence. Implementing a comprehensive treatment plan, often involving a team of specialists including wound care nurses, physicians, vascular surgeons, podiatrists, and dietitians, is crucial for successful outcomes and improving the patient’s quality of life.
Key components of leg ulcer management include:
- Addressing the Underlying Cause: This is the most crucial step, as failure to correct the primary pathology will result in non-healing or recurrence.
- For Venous Ulcers (Chronic Venous Insufficiency):
- Compression Therapy: The cornerstone of venous ulcer treatment. Graded compression (stockings, multilayer bandages, wraps) reduces venous hypertension, decreases edema, and improves venous return. This is essential for healing venous leg ulcers and preventing recurrence. Compression needs to be consistent and correctly applied.
- Leg Elevation: Regularly elevating the legs above heart level helps reduce swelling and venous pooling, especially during rest.
- Pharmacotherapy: Diuretics for severe edema, pentoxifylline to improve microcirculation, or aspirin may be considered. Phlebotonics (e.g., micronized purified flavonoid fraction) can help strengthen vein walls.
- Surgical/Endovascular Interventions: Procedures like vein ablation (laser, radiofrequency), sclerotherapy, or ligation/stripping of incompetent superficial or perforating veins can correct venous reflux and prevent recurrence. Deep venous reconstruction is less common.
- Calf Muscle Pump Exercises: Encouraging ambulation and specific exercises to improve the effectiveness of the calf muscle pump.
- For Arterial Ulcers (Peripheral Arterial Disease – PAD):
- Revascularization: The most critical step. Surgical bypass (grafting) or endovascular procedures (angioplasty, stenting, atherectomy) to restore adequate blood flow to the limb. Without improved perfusion, healing is unlikely. This is fundamental for treating arterial leg ulcers and preventing limb loss.
- Pharmacotherapy: Antiplatelet agents (e.g., aspirin, clopidogrel) to prevent clot formation, statins to manage atherosclerosis and reduce cardiovascular risk, and cilostazol to improve walking distance and reduce pain in claudication.
- Risk Factor Modification: Aggressive management of underlying conditions such as diabetes, hypertension, hyperlipidemia, and absolute smoking cessation. Regular exercise programs (supervised if necessary) are also important for improving collateral circulation.
- Avoidance of Compression: Compression is generally contraindicated in significant arterial disease (ABI < 0.5) as it can further compromise blood flow.
- For Neuropathic (Diabetic) Ulcers:
- Offloading: Reducing pressure on the ulcerated area is paramount. This can involve specialized footwear, therapeutic shoes, total contact casts (TCCs), removable walking boots, crutches, or wheelchairs. This is crucial for diabetic foot ulcer care to prevent repetitive trauma.
- Glycemic Control: Strict management of blood glucose levels to prevent further nerve damage, improve microcirculation, and enhance wound healing. Hemoglobin A1c targets should be individualized.
- Foot Care Education: Regular self-examination for any new wounds or skin changes, proper hygiene, and consistent professional foot care (podiatry) to address calluses, nail problems, and deformities to prevent recurrence.
- Surgical Intervention: May be necessary to correct foot deformities (e.g., Charcot reconstruction, bunionectomy) that create pressure points or to debride necrotic tissue and infected bone (osteomyelitis).
- For Venous Ulcers (Chronic Venous Insufficiency):
- Local Wound Care: These interventions directly address the ulcer bed and surrounding tissue.
- Debridement: Removal of necrotic tissue (eschar) and slough from the wound bed to promote granulation and epithelization. This is essential for reducing bacterial load and allowing healthy tissue to form. Methods include:
- Surgical Debridement: Fastest, used for large amounts of necrotic or infected tissue, often performed in an operating room.
- Mechanical Debridement: Using wet-to-ry dressings (less common now due to non-selective nature), hydrotherapy, or sharp debridement at the bedside.
- Autolytic Debridement: Using occlusive dressings (e.g., hydrocolloids, hydrogels, transparent films) to allow the body’s own enzymes to break down devitalized tissue. This is gentle and selective.
- Enzymatic Debridement: Topical enzymes (e.g., collagenase) applied to the wound to selectively digest necrotic tissue.
- Biological Debridement: Medical-grade maggots (larval therapy) can be highly effective for selective debridement, especially in infected wounds.
- Infection Control:
- Topical Antimicrobials: For localized infection or bioburden reduction (e.g., silver dressings, iodine dressings, honey dressings).
- Systemic Antibiotics: For spreading cellulitis, deep tissue infection, or osteomyelitis, guided by wound cultures and sensitivity tests. Infected leg ulcer treatment often requires oral or intravenous antibiotics, sometimes prolonged courses.
- Antiseptics: Used judiciously (e.g., polyhexanide, povidone-iodine, chlorhexidine) as some can be cytotoxic to healthy cells and impair healing if used inappropriately.
- Moisture Balance: Maintaining an optimal moist wound environment is crucial for cellular activity and healing.
- Dressings: Selection of appropriate dressings (e.g., foams, alginates, hydrofibers, hydrogels, transparent films, collagen dressings) to maintain a moist wound environment.
- Exudate Management: Dressings must be capable of managing the amount of exudate to prevent maceration of surrounding skin while keeping the wound bed moist. Highly absorbent dressings are used for high exudate, while hydrogels are used for dry wounds.
- Pain Management: Addressing pain improves patient comfort and compliance.
- Systemic Analgesics: NSAIDs, acetaminophen, or opioids for severe pain, managed carefully to avoid side effects.
- Topical Anesthetics: Applied directly to the wound before dressing changes or debridement (e.g., lidocaine gel).
- Addressing Underlying Pain Causes: Improving circulation for arterial pain, reducing edema for venous pain, or nerve pain medications for neuropathic pain.
- Debridement: Removal of necrotic tissue (eschar) and slough from the wound bed to promote granulation and epithelization. This is essential for reducing bacterial load and allowing healthy tissue to form. Methods include:
- Advanced Therapies and Adjuncts: For complex or non-healing ulcers.
- Negative Pressure Wound Therapy (NPWT): Applying controlled negative pressure to the wound bed to remove exudate, reduce edema, increase blood flow, promote granulation tissue formation, and stabilize the wound. Effective for complex or non-healing wounds.
- Skin Grafts and Substitutes: For large, non-healing ulcers that are clean and well-vascularized, autologous skin grafts (patient’s own skin), allografts (donor skin), or engineered skin substitutes (e.g., bilayered skin constructs, cellular and acellular matrices) may be used to achieve closure.
- Growth Factors: Topical application of recombinant human growth factors (e.g., PDGF for diabetic foot ulcers) to stimulate cell proliferation, collagen synthesis, and wound healing.
- Hyperbaric Oxygen Therapy (HBOT): Delivers 100% oxygen at increased atmospheric pressure, improving oxygen delivery to ischemic tissues, promoting angiogenesis (new blood vessel formation), and enhancing antibiotic effectiveness. Used for severe diabetic foot ulcers, chronic refractory wounds, or osteomyelitis.
- Ultrasound Therapy: Low-frequency ultrasound may promote wound healing by stimulating cellular activity.
- Patient Education and Lifestyle Modifications: Crucial for long-term prevention and self-management.
- Diet and Nutrition: Adequate protein, vitamins (especially C and A), and minerals (zinc, iron) are vital for wound healing. Malnutrition can severely impede recovery. A consultation with a dietitian may be necessary.
- Smoking Cessation: Smoking significantly impairs circulation, oxygen delivery, and delays wound healing. Cessation is critical.
- Exercise: Appropriate exercise, particularly calf muscle exercises, can improve venous return for venous ulcers and collateral circulation for arterial disease. Consult a physical therapist.
- Weight Management: Reducing obesity can alleviate pressure on legs and improve circulation, reducing the risk of venous disease.
- Regular Monitoring: Consistent follow-up with healthcare providers to monitor healing progress, manage complications, and prevent recurrence.
- Skin Protection: Moisturizing dry skin, protecting fragile areas from trauma, and wearing appropriate, well-fitting footwear (especially for diabetic neuropathy).
- Infection Prevention: Education on early signs of infection and importance of hygiene.
The comprehensive nature of trophic ulcer on the leg treatment underscores the importance of a patient-centered approach. By integrating these various therapeutic modalities, healthcare professionals aim to achieve durable wound closure, prevent complications like infection and amputation, and restore functional mobility, ultimately enhancing the patient’s long-term health and well-being. This integrated approach to chronic wound care is essential for effective healing and prevention of recurrence, requiring active participation from the patient and their support network.