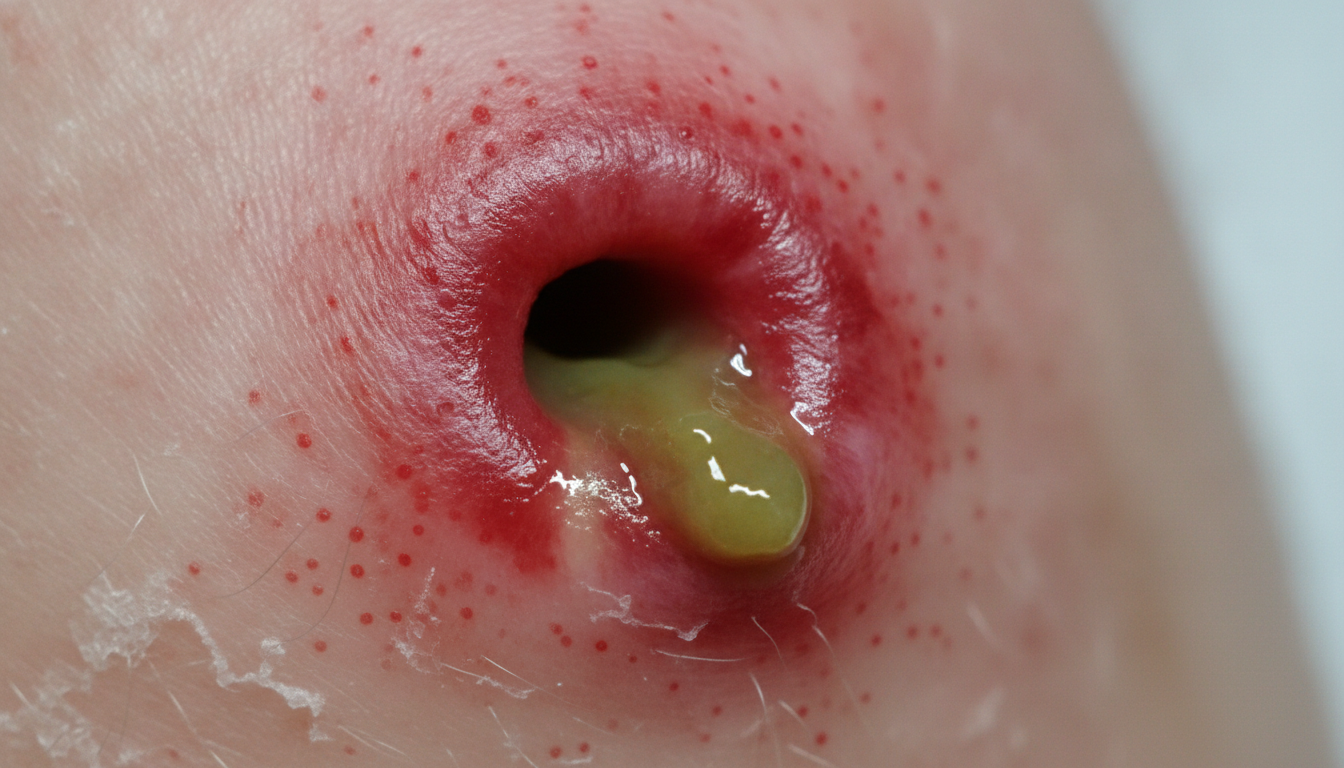
Understanding the specific visual indicators of a common sexually transmitted infection is crucial for timely diagnosis and management. This comprehensive article delves into detailed trichomoniasis in men symptoms pictures, illustrating the varied presentations of this often overlooked condition to aid in recognizing potential signs. Identifying these visual clues early can significantly improve outcomes and prevent further transmission of male trichomoniasis.
Trichomoniasis in men Symptoms Pictures
While often asymptomatic, trichomoniasis in men can manifest through a range of discernible symptoms that warrant prompt attention. These symptoms, when present, primarily affect the urethra and surrounding genital areas, offering crucial visual and tactile cues for identification. Recognizing these specific indicators is vital for early diagnosis of male trichomoniasis symptoms and initiating appropriate treatment. The symptomatic presentation of penile trichomoniasis can vary significantly among individuals, influenced by factors such as the duration of infection, the host’s immune response, and the specific strain of Trichomonas vaginalis.
The most common symptomatic presentations that individuals might observe or experience include, but are not limited to, the following:
- Urethral Discharge: One of the hallmark signs of urethral trichomoniasis is the presence of an abnormal discharge from the penis. This discharge can present in several forms, from a very subtle, thin, and clear fluid to a more noticeable, thick, or purulent exudate.
- Clear or Whitish Discharge: Initially, the discharge associated with trichomoniasis in men might be minimal, often described as clear, watery, or slightly milky. This can be easily overlooked or mistaken for normal physiological secretions. It may become more apparent primarily in the morning or when “milking” the urethra gently from the base towards the tip. Such a scant discharge may only leave a minimal moist spot on underwear or toilet paper, often drying quickly without significant trace, thereby failing to alarm the individual.
- Yellowish-Green or Foamy Discharge: In more pronounced cases of male trichomoniasis, the discharge can evolve into a more distinct yellowish-green hue. This coloration often signifies a higher concentration of inflammatory cells, immune responses, and potentially the presence of secondary bacterial involvement or a more active parasitic burden. Uniquely, though less common in men than in women, a foamy consistency can occasionally be observed in the discharge, which, when present, is highly suggestive of trichomonal infection. This type of discharge typically indicates a more active and established infection, can be more persistent throughout the day, and may necessitate the use of toilet paper or panty liners for management, impacting daily hygiene and comfort.
- Purulent Discharge: Rarely, especially in severe or neglected cases, or when coinfection with other pathogens is present, the discharge might become frankly purulent, appearing thick, opaque, and yellowish, indicating significant inflammation and potential tissue damage. The volume of discharge can range from scant to moderate, and its consistency may vary from thin and watery to thicker and more mucoid. The characteristics of the discharge, including its color, consistency, and volume, are crucial for proper diagnosis of trichomoniasis symptoms men.
- Dysuria (Painful Urination): A significant number of men with symptomatic trichomoniasis report discomfort or pain during urination, a symptom often consistent with urethritis from various causes.
- Burning Sensation: This typically manifests as a burning or stinging sensation that occurs predominantly during the act of micturition, often most intense as urine passes through the inflamed urethra. The discomfort can be experienced along the entire length of the urethra or localized specifically at the urethral meatus (opening). This symptom is often intermittent but can become constant and severe with increasing inflammation, making urination a particularly unpleasant and dreaded experience for affected individuals.
- Irritation during Urination: Beyond just a burning sensation, some individuals describe a general sense of irritation, rawness, or a scratchy feeling within the urethra during voiding. This can be a persistent issue, making trips to the restroom a source of ongoing discomfort. The intensity can range from mild to severe, significantly impacting daily comfort and quality of life, and is a common complaint in male urethritis symptoms.
- Urethral Itching or Irritation: An irritating sensation within the urethra is another common complaint among men suffering from trichomoniasis, often leading to significant distress.
- Internal Itching: This internal itching sensation can be subtle or intensely irritating, often described as a tickling, crawling, or deep-seated itch feeling deep within the penile shaft. It may be intermittent or constant, leading to significant distraction and discomfort, and can sometimes be exacerbated by warmth or after urination.
- Meatal Irritation: The irritation can also be localized specifically to the urethral opening (meatus), presenting as a persistent, uncomfortable sensation that prompts frequent touching, rubbing, or manipulation of the area. This can sometimes lead to visible redness, mild swelling, and minor excoriations (skin abrasions) around the meatus due to persistent scratching or irritation, which further aggravates the discomfort and can be seen in trichomoniasis in men photos.
- Penile Itching and General Discomfort: Beyond the urethra, generalized itching and discomfort can affect the entire penis, particularly the glans (head of the penis) and the foreskin in uncircumcised men, due to proximity and shared inflammatory processes.
- Generalized Penile Itching: This diffuse itching can be a significant source of distress, extending from the tip of the penis along the shaft. It is often worse after sexual activity, during periods of increased warmth and moisture, or after prolonged periods without urination. This symptom contributes significantly to the overall discomfort experienced by men with male trichomoniasis.
- Discomfort and Tenderness: Some men report a general feeling of discomfort, tenderness to touch, or even a dull ache in the penile region. This discomfort is often vague but persistent, and can sometimes radiate to the perineum (area between the anus and scrotum) or suprapubic area, indicating a broader inflammatory process affecting adjacent structures.
- Post-Coital Discomfort or Dyspareunia: While more commonly associated with women, men can also experience discomfort during or after sexual intercourse due to urethral or glans inflammation caused by trichomoniasis.
- Pain during Ejaculation: Inflammation of the urethra or associated glands (like the prostate or epididymis, in rare complicated cases) can lead to pain or a burning sensation specifically during ejaculation. This can significantly impact sexual function, enjoyment, and lead to avoidance of sexual activity.
- Post-Ejaculatory Irritation: Following ejaculation, some men report increased urethral itching, burning, or a general sense of irritation that can persist for several hours. This post-coital irritation is a key indicator that an underlying inflammatory process is at play within the genitourinary tract, suggesting the need for further investigation for penile trichomoniasis.
- Urgency and Frequency of Urination: Although less common than dysuria, some men with significant urethral inflammation due to trichomoniasis may experience increased urinary urgency or frequency, similar to symptoms of a urinary tract infection (UTI) but typically without bacterial growth in urine cultures. The persistent irritation of the urethral lining can trigger bladder sensations, leading to a perceived need to urinate more often than usual, often with a sudden and intense urge that is difficult to postpone. This can disrupt sleep and daily activities.
Signs of Trichomoniasis in men Pictures
Observing the specific physical signs of trichomoniasis in men is paramount for accurate diagnosis, especially given the often non-specific or subtle nature of symptoms. While men with male trichomoniasis may be entirely asymptomatic, when objective signs are present, they are primarily localized to the genital area. These visual cues, though often subtle, can provide strong evidence for the presence of Trichomonas vaginalis infection. A thorough clinical examination, often aided by specific diagnostic tests like nucleic acid amplification tests (NAATs), is crucial to confirm the presence of Trichomonas vaginalis in men.
The key objective signs that may be noted during a physical examination or by careful self-observation, which could indicate male trichomoniasis, include:
- Urethral Erythema (Redness at Meatus): One of the most frequently observed and visually important signs is redness around the urethral opening, indicating local inflammation.
- Perimeatal Redness: The area immediately surrounding the urethral meatus often appears visibly redder than the surrounding glans tissue. This erythema is a direct result of inflammation caused by the parasitic infection and the body’s immune response. The intensity of redness can vary from a faint pink blush to a vivid crimson, depending on the severity and duration of the inflammatory process. This sign can be particularly noticeable upon gentle retraction of the foreskin in uncircumcised men, revealing a distinctly inflamed urethral opening, a key feature in trichomoniasis in men images.
- Localized Swelling: Alongside redness, there might be subtle edema (swelling) of the urethral lips or the tissue immediately surrounding the meatus, making the opening appear slightly pouting or swollen. This swelling can contribute to the sensation of discomfort, tightness, or a perceived narrowing at the urethral meatus.
- Visible Urethral Discharge: While previously described under symptoms as something the patient experiences, the visible discharge is a significant objective sign that a clinician can directly observe.
- Observation of Exudate: A healthcare provider might observe discharge directly emerging from the urethral meatus spontaneously, without any manipulation, especially in more severe cases. More commonly, discharge might be elicited by gently “milking” the urethra from the base of the penis towards the tip. The characteristics—including color (e.g., clear, watery, milky, yellowish-green, purulent), consistency (e.g., thin, thick, mucoid, foamy), and volume—are critical diagnostic indicators for penile trichomoniasis. A thin, watery, white discharge is often an early visible sign, potentially evolving to a thicker, yellowish-green or purulent discharge in more advanced or symptomatic cases.
- Staining on Underwear: Patients may report or present with visible staining on their underwear, particularly at the tip of the penis, which can range from a light smear to a more substantial wet patch, providing tangible evidence of urethral exudate. This staining provides an excellent indirect visual cue of ongoing urethral activity related to male urethritis symptoms, even if direct discharge is not immediately apparent during examination.
- Balanitis (Inflammation of the Glans Penis): Inflammation of the glans is a less common but significant objective sign of trichomoniasis, especially in uncircumcised men where moisture, warmth, and friction can contribute to parasitic proliferation and secondary irritation.
- Glans Erythema: The glans penis may appear generally red and inflamed. This redness can be diffuse, covering a broad area, or patchy, affecting specific areas more than others. The inflamed skin might appear shiny, irritated, or slightly macerated. This inflammation is a direct response to the presence of the parasite or secondary bacterial overgrowth facilitated by the primary infection.
- Small Punctate Lesions or Erosions: In some instances of trichomoniasis-induced balanitis, one might observe tiny, pinpoint red spots or petechiae (small, non-blanching red or purple spots) on the surface of the glans. These punctate lesions represent localized areas of inflammation, capillary dilation, or minor superficial erosions. While not a typical “rash” in the dermatological sense, these inflammatory changes are visually distinct and indicative of surface irritation, providing visual information for trichomoniasis images men.
- Tenderness and Swelling of the Glans: The inflamed glans is often tender to touch and may appear slightly swollen, contributing to general discomfort and possibly making hygiene difficult. The presence of balanitis often signifies a more advanced or irritating infection, potentially complicating patient comfort and daily activities.
- Posthitis (Inflammation of the Foreskin): In uncircumcised men, inflammation of the foreskin often accompanies balanitis, leading to a combined condition known as balanoposthitis.
- Foreskin Redness and Swelling: The inner surface of the foreskin can become visibly red, swollen, and tender. This inflammation can sometimes make retraction of the foreskin difficult or painful (phimosis) or, if retracted, make it difficult to return to its normal position (paraphimosis), although these are rare complications. The visual appearance can be quite striking, with marked erythema and edema.
- Maceration or Excoriation: Due to persistent moisture, inflammation, irritation, and possibly scratching, the skin of the foreskin might show signs of maceration (softening and whitening due to prolonged moisture entrapment) or excoriation (skin damage from scratching). These signs are indirect indicators of ongoing irritation and inflammation associated with trichomoniasis in men and can be a source of secondary bacterial or fungal infections.
- Absence of Visible Signs (Asymptomatic Presentation): It is crucial to emphasize that a significant proportion of men with trichomoniasis are entirely asymptomatic and exhibit no visible signs or symptoms upon examination. This makes routine screening of high-risk individuals and partners of infected women critically important for controlling the spread of this STI. The absence of visible signs does not rule out infection and highlights the necessity of laboratory confirmation for definitive diagnosis of Trichomonas vaginalis in men. These asymptomatic carriers are silent spreaders, making early detection challenging but vital for public health.
Early Trichomoniasis in men Photos
Identifying early trichomoniasis in men can be particularly challenging due to the often subtle or entirely absent initial symptoms. However, understanding what to look for in these nascent stages of infection is crucial for preventing progression and transmission. Early signs of male trichomoniasis are often easily overlooked or mistaken for minor, non-specific irritations. These initial manifestations are typically mild and may be intermittent, making a high index of suspicion necessary for timely detection, especially when viewing Trichomoniasis in men photos showcasing initial presentations.
The initial phase of trichomoniasis in men often presents with very discreet indicators:
- Subtle Urethral Irritation: This is perhaps the most common and earliest felt symptom.
- Mild Itching or Tickling Sensation: Patients may report a very faint, occasional itching or tickling sensation within the urethra. This feeling is often not bothersome enough to seek immediate medical attention and can be easily dismissed as a minor irritation or sensitivity to clothing, soaps, or detergents. It might be felt only at specific times, such as after urination, after sexual activity, or during periods of prolonged sitting. The fleeting nature of this symptom contributes to its frequent oversight.
- Slight Discomfort upon Urination: The dysuria in early stages is usually very mild, manifesting as a slight sting, a sensation of unusual warmth, or an unusual sensation at the very beginning or end of urination, rather than overt pain. This mild discomfort can be transient, appearing for a day or two and then seemingly disappearing, only to return later. Such intermittency often leads individuals to believe the issue has resolved spontaneously, delaying diagnosis of early trichomoniasis symptoms men.
- Scant or Transient Discharge: The earliest forms of penile discharge are exceptionally subtle and often require careful observation to detect.
- Clear or Whitish Meatal Moisture: At its very onset, male trichomoniasis might only produce a barely perceptible, clear, or very faintly whitish moisture at the urethral opening. This is often noticed only when specifically looking for it, such as after expressing the urethra from the base of the penis towards the tip, or first thing in the morning before voiding. It may be so minimal that it only leaves a barely visible moist spot or thin film on underwear or toilet paper, quickly drying without significant trace. This subtle nature makes it easily overlooked as a significant symptom of trichomoniasis in men.
- Intermittent Nature: This scant discharge might not be constant. It could appear for a short period and then seemingly resolve, leading individuals to believe the issue has passed, only for it to recur days or weeks later. This intermittent nature makes it challenging for individuals to recognize it as a persistent issue requiring medical evaluation, hindering early diagnosis.
- Mild Perimeatal Redness: The earliest visual sign around the urethral opening can be very slight and easily mistaken for general irritation.
- Faint Erythema: There may be a very subtle, light pink hue around the urethral meatus, barely distinguishable from the normal skin tone of the glans. This minimal redness can be easily attributed to normal friction, vigorous masturbation, or local irritation from soaps, body washes, or clothing, making it difficult to differentiate as a specific sign of infection. It lacks the intense, fiery redness often associated with bacterial urethritis, making it less alarming visually.
- No Apparent Swelling: In the very early stages, there is typically no significant edema or swelling of the urethral lips, making the visual presentation even less striking and thus less likely to prompt concern for STD symptoms men.
- Lack of Overt Symptoms (High Asymptomatic Rate): It is paramount to reiterate that the most common “early sign” of trichomoniasis in men is often the complete absence of any noticeable symptoms or visible signs. A very high percentage of infected men remain asymptomatic for prolonged periods, sometimes indefinitely. This asymptomatic status does not mean the infection is benign; these men can still transmit the parasite to their sexual partners, and in rare cases, can develop complications like epididymitis or prostatitis. Therefore, the early stages are often clinically silent, underscoring the importance of partner notification and presumptive treatment if a female partner tests positive for Trichomonas vaginalis, even in the absence of male symptoms.
- Transient Symptoms Mimicking Other Conditions: Early male trichomoniasis symptoms can be so non-specific and transient that they are often mistaken for minor irritation, a mild urinary tract infection (UTI) that resolves on its own, or even allergies. This transient and vague presentation contributes significantly to delayed diagnosis and ongoing transmission cycles. The individual might experience a day or two of mild burning or itching, and then the symptoms might subside, leading them to believe no serious issue exists.
For these reasons, identifying early trichomoniasis in men often relies heavily on epidemiological links (e.g., recent sexual contact with an infected partner) and subsequent laboratory testing, rather than distinct visual cues alone. The subtle nature of initial signs makes detailed patient history and awareness of risk factors essential in suspecting and diagnosing Trichomonas vaginalis in men during its nascent phase, highlighting the importance of comprehensive sexual health screenings.
Skin rash Trichomoniasis in men Images
It is important to clarify that trichomoniasis in men does not typically present with a characteristic, distinct dermatological “skin rash” in the way that viral infections like herpes (with its vesicular lesions) or syphilis (with its secondary macular or papular rash) do. The term “skin rash” might lead to expectations of widespread, papular, vesicular, or pustular lesions. Instead, any “rash-like” appearance associated with male trichomoniasis is primarily due to localized inflammation and irritation of the glans penis or foreskin (known as balanitis or posthitis) resulting from the parasitic infection. These manifestations are generally localized to the genital area and represent inflammatory changes rather than a systemic dermatological eruption. Understanding these specific local inflammatory signs is crucial when assessing for trichomoniasis rash men.
The “rash-like” signs that might be observed in cases of penile trichomoniasis include:
- Localized Erythema on the Glans Penis or Inner Foreskin: This is the most prevalent visual manifestation of surface inflammation.
- Patchy or Diffuse Redness: The most common visual manifestation is areas of redness on the glans penis. This erythema can be patchy, appearing in irregular spots or streaks, or more diffuse, covering a larger surface area of the glans. In uncircumcised men, the inner surface of the foreskin can also display significant redness, often exacerbated by moisture and friction. This redness is a direct result of the inflammatory response to the Trichomonas vaginalis parasite and any associated secondary irritation or opportunistic bacterial overgrowth.
- Bright Red Appearance: In more inflamed states, the affected skin can appear quite bright red, sometimes with a shiny or glistening quality, particularly in areas where skin folds or persistent moisture are prevalent, as the parasite thrives in such environments. This intense coloration can be alarming and is often accompanied by significant local discomfort.
- Irritated or Inflamed Patches of Skin: Beyond mere redness, the texture and feel of the affected skin can also change.
- Mildly Edematous Areas: Alongside redness, there might be subtle swelling (edema) of the affected skin, making it appear slightly puffy, engorged, or raised compared to surrounding healthy tissue. This edema contributes to the sensation of local discomfort, tightness, or even a feeling of fullness in the glans.
- Slightly Macerated Appearance: Especially in uncircumcised men, the warm, moist environment under the foreskin, coupled with chronic inflammation, can lead to a macerated (softened, whitish, sometimes wrinkled) appearance of the inflamed skin. This is not a direct lesion of trichomoniasis but rather a consequence of persistent inflammation and moisture retention, providing an environment conducive to microbial overgrowth, which can compound the irritation and appear as a “rash.”
- Small, Pinpoint Red Lesions (Punctate Erythema): In some instances, the inflammation can create discrete visual anomalies.
- Petechiae-like Spots: In some instances, the inflammation on the glans can manifest as very tiny, discrete red dots, sometimes referred to as punctate erythema or petechiae-like lesions. These are not raised papules but rather small areas of capillary leakage or intense localized inflammation within the superficial skin layers. They can be sparse or numerous, giving the glans a speckled red appearance, which can be a key visual cue in trichomoniasis images men.
- Absence of Vesicles or Ulcers: Crucially, these lesions are typically not vesicles (fluid-filled blisters), papules (raised bumps), or frank ulcers (open sores), which distinguishes them from other STIs like herpes or chancroid. The inflammatory reaction is generally superficial and does not usually involve deep tissue necrosis or blister formation.
- Mild Scaling or Dryness in Irritated Areas: Chronic inflammation can sometimes lead to changes in skin texture.
- Fine Desquamation: In areas of chronic irritation or inflammation, particularly on the glans or foreskin, there might be very fine, superficial scaling or a dry, flaky appearance as the skin attempts to heal and shed inflamed cells. This is a non-specific sign of skin irritation and repair, and can sometimes be accompanied by a feeling of tightness, dryness, or peeling.
- Absence of Typical Dermatological Lesions: It is critical to reiterate that trichomoniasis does not cause classic papules, vesicles, pustules, warts, or chancre-like lesions that are characteristic of other sexually transmitted infections. If such lesions are present, clinicians should consider coinfection with other pathogens or an alternative diagnosis. The “rash” associated with male trichomoniasis is primarily an inflammatory reaction, not a specific parasitic skin eruption, making the distinction vital for accurate diagnosis and management. The lack of distinct, primary skin lesions can sometimes make visual diagnosis difficult and requires careful differentiation from other conditions.
Therefore, when considering skin rash trichomoniasis in men images, one should expect to see generalized redness, irritation, and possibly small punctate inflammatory spots on the glans or foreskin, rather than a distinctive, lesion-specific rash. These visual changes are often accompanied by the urethral symptoms previously described, such as discharge and dysuria, forming a constellation of signs that can point towards a diagnosis of Trichomonas vaginalis infection in men. Prompt clinical evaluation and laboratory testing are essential to confirm the diagnosis and rule out other causes of genital irritation or inflammation.
Trichomoniasis in men Treatment
Effective treatment for trichomoniasis in men is crucial not only for alleviating symptoms and discomfort but also for preventing long-term complications and, most importantly, for stopping further transmission of the infection to sexual partners. The treatment regimens are highly effective, primarily relying on specific antibiotic medications known as nitroimidazoles. A comprehensive approach involves appropriate medication, rigorous adherence, simultaneous partner notification and treatment, and the adoption of preventative measures. Understanding the specifics of trichomoniasis treatment men is vital for successful eradication and sustained sexual health.
The primary medications used to treat Trichomonas vaginalis in men are nitroimidazoles, which effectively kill the parasite:
- Metronidazole: This is the most commonly prescribed and highly effective medication for trichomoniasis.
- Single-Dose Regimen: The Centers for Disease Control and Prevention (CDC) generally recommends a single oral dose of 2 grams of metronidazole. This one-time dose is preferred due to its simplicity, which can lead to significantly higher patient adherence, making it a very practical approach for STD treatment men. It is effective in curing most uncomplicated cases of male trichomoniasis. The medication should be taken at once, typically with food to minimize gastrointestinal upset.
- Multi-Day Regimen: An alternative approach, sometimes used for symptomatic men, in cases of suspected or confirmed treatment failure, or when adherence to a single large dose is a concern, involves taking 500 mg of metronidazole orally twice a day for 7 days. This extended course ensures sustained therapeutic levels of the drug, particularly in situations where a single dose might be insufficient for complete eradication, or where the parasitic load is particularly high. Both regimens are highly effective against Trichomonas vaginalis.
- Important Considerations with Metronidazole:
- Alcohol Avoidance: Patients must be strongly advised to completely avoid alcohol consumption during treatment with metronidazole and for at least 24-72 hours after the last dose. Alcohol can interact with metronidazole, leading to a severe disulfiram-like reaction characterized by nausea, projectile vomiting, severe abdominal cramps, flushing, headaches, and palpitations. This is a critical patient education point for successful trichomoniasis treatment men and needs to be emphasized clearly.
- Gastrointestinal Side Effects: Common side effects include nausea, vomiting, abdominal cramping, diarrhea, and a distinctly unpleasant metallic taste in the mouth. Taking the medication with food can help mitigate some of these gastrointestinal disturbances, and ensuring adequate hydration is also beneficial.
- Tinidazole: Tinidazole is another highly effective nitroimidazole antibiotic, offering a valuable alternative, often reserved for cases of metronidazole intolerance, treatment failure, or when drug resistance is suspected.
- Single-Dose Regimen: Similar to metronidazole, tinidazole is typically prescribed as a single oral dose of 2 grams. It offers a comparable efficacy profile to metronidazole and can be a valuable alternative for male trichomoniasis treatment, especially for patients who have previously failed metronidazole or experienced intolerable side effects.
- Important Considerations with Tinidazole:
- Alcohol Avoidance: Like metronidazole, tinidazole also interacts negatively and severely with alcohol, necessitating complete abstinence from alcohol during treatment and for an extended period of at least 72 hours after the last dose to prevent disulfiram-like reactions. This longer abstinence period compared to metronidazole should be clearly communicated to the patient.
- Side Effect Profile: The side effect profile is similar to metronidazole, including gastrointestinal upset (nausea, abdominal pain), a metallic taste, and dizziness, though some patients may tolerate tinidazole better than metronidazole. This individual variability in tolerability can make tinidazole a preferred option for some.
Beyond medication, several critical aspects ensure successful management and prevention of re-infection for trichomoniasis in men:
- Partner Treatment: Simultaneous treatment of all sexual partners is absolutely essential for preventing re-infection of the index patient and for controlling the spread of Trichomonas vaginalis within the community.
- Mandatory Co-Treatment: Even if a partner is asymptomatic, they should be tested and, if positive, treated concurrently. Failure to treat all sexual partners is the most common reason for treatment failure and recurrent infections in the index patient. This concept is fundamental to all comprehensive STD treatment men protocols and public health strategies.
- Expedited Partner Therapy (EPT): In many jurisdictions, Expedited Partner Therapy (EPT) allows for a patient to pick up prescriptions or medications for their partner(s) without the partner having to be seen by a healthcare provider. This facilitates faster treatment, reduces barriers to care for sexual partners, and significantly improves treatment uptake and effectiveness in breaking the chain of transmission.
- Abstinence During Treatment: Patients should be advised to abstain from any sexual intercourse (vaginal, anal, or oral) for at least 7 days after both the patient and all their sexual partners have completed their full course of treatment and are completely asymptomatic. This period ensures that the medication has had sufficient time to eradicate the parasite from both individuals and prevents early re-exposure before full parasitic clearance.
- Follow-up Testing (Test of Cure – TOC):
- Recommendations for Men: While a routine “test of cure” (TOC) is not universally recommended for asymptomatic men after successful trichomoniasis treatment, it is strongly advised for men with persistent symptoms despite treatment, if there is a strong suspicion of re-infection, or if their treated female partner experiences recurrence. The TOC typically involves highly sensitive nucleic acid amplification tests (NAATs) performed several weeks after treatment completion (e.g., 3 months after treatment) to detect any residual or recurrent infection.
- Importance for Public Health: For ongoing surveillance, in clinical trial settings, or for high-risk individuals (e.g., those with multiple partners), TOC remains valuable to confirm eradication and monitor for potential drug resistance.
- Prevention and Counseling:
- Condom Use: Consistent and correct use of barrier methods, particularly latex condoms, can significantly reduce the risk of acquiring and transmitting Trichomonas vaginalis and other sexually transmitted infections. Education on proper condom application and disposal is crucial.
- Safe Sex Practices: Comprehensive counseling on safe sexual practices, including limiting the number of sexual partners, avoiding unprotected sex, and consistent condom use, is vital for long-term prevention of all STIs, including Trichomoniasis in men.
- Screening for Other STIs: Given that individuals diagnosed with one STI are at a higher risk for acquiring or having concomitant infections with others, it is advisable to screen for other common sexually transmitted infections (e.g., chlamydia, gonorrhea, HIV, syphilis, hepatitis B) when trichomoniasis is diagnosed. This ensures a holistic approach to sexual health.
- Management of Persistent or Recurrent Infections:
- Re-evaluation: If symptoms persist or recur after initial treatment, a thorough re-evaluation is necessary. This includes confirming strict adherence to medication, assessing for re-exposure from an untreated or newly infected partner, and considering potential drug resistance of the Trichomonas vaginalis strain.
- Alternative Regimens: For resistant cases, higher doses or longer courses of metronidazole or tinidazole might be prescribed. For example, a 7-day course of metronidazole 500 mg orally twice daily might be extended for persistent cases, or tinidazole 500 mg twice daily for 5 days or 1 gram daily for 5 days may be considered. In extremely rare and highly resistant cases, expert consultation with an infectious disease specialist is recommended, and parenteral (intravenous) administration of metronidazole has been used, though this is highly unusual for male trichomoniasis.
- Referral to Specialist: In complex or highly resistant cases, referral to an infectious disease specialist or a genitourinary medicine clinic may be warranted for specialized management of male trichomoniasis, including resistance testing if available.
In summary, the treatment of trichomoniasis in men is straightforward with appropriate medication, but its success hinges on rigorous adherence, comprehensive partner treatment, and thorough patient education regarding safe sexual practices and strict alcohol avoidance. Early diagnosis and diligent follow-through on all aspects of treatment and prevention are key to eradicating the infection, preventing its spread, and maintaining optimal sexual health.