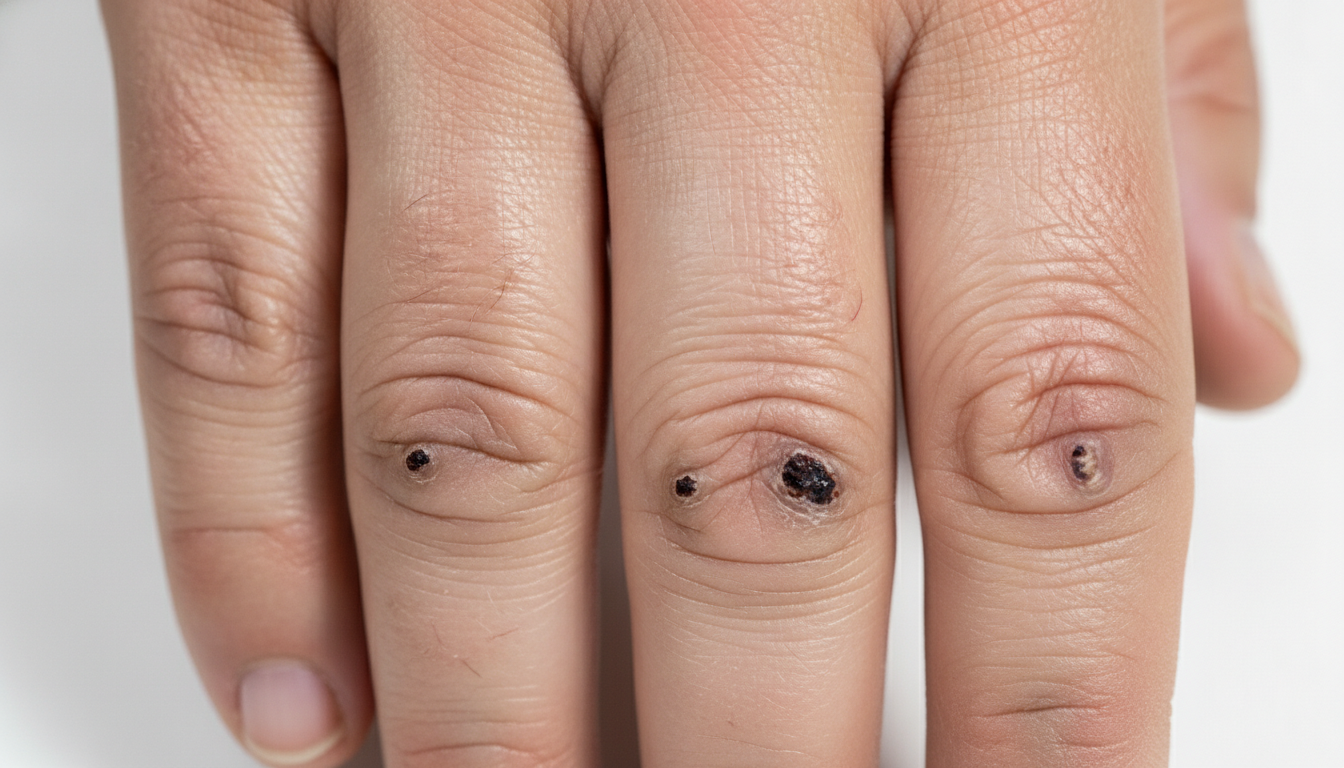
This article provides a detailed visual guide to Systemic scleroderma symptoms pictures, showcasing the diverse manifestations of this complex condition. Observing Systemic scleroderma symptoms pictures can help in understanding the progression and impact of the disease on various body systems, particularly the skin.
Systemic scleroderma Symptoms Pictures
Systemic scleroderma presents a wide array of visual symptoms, predominantly affecting the skin, which are crucial for early recognition and ongoing management. Examining Systemic scleroderma symptoms pictures often reveals the progressive nature of skin thickening and other related changes. The hallmark visual characteristic in Systemic scleroderma symptoms pictures is the hardening and tightening of the skin, a process known as fibrosis, which can significantly alter appearance and function. This skin involvement can be widespread (diffuse cutaneous systemic scleroderma) or limited to specific areas (limited cutaneous systemic scleroderma), each with distinct patterns visible in Systemic scleroderma symptoms pictures.
Key skin manifestations often highlighted in Systemic scleroderma symptoms pictures include:
- Skin Thickening and Hardening:
- Sclerodactyly: A prominent feature in Systemic scleroderma symptoms pictures, characterized by tight, shiny skin on the fingers and toes, making it difficult to bend or fully extend digits. This often gives the fingers a tapered or sausage-like appearance.
- Forearm and Arm Involvement: In diffuse Systemic scleroderma, skin thickening extends above the elbows and knees, reaching the trunk, a severity often captured in comprehensive Systemic scleroderma symptoms pictures.
- Facial Changes: Pictures frequently show a mask-like facial appearance due to tight skin, often accompanied by microstomia (a small mouth opening), radial furrowing (lines radiating from the mouth), and difficulty smiling or making facial expressions. The nose may appear pinched.
- Generalized Skin Tightness: The skin over affected areas can become taut, smooth, and shiny, losing its normal folds and elasticity. This can restrict movement of joints and is a common sight in Systemic scleroderma symptoms pictures showcasing advanced disease.
- Raynaud’s Phenomenon:
- Triphasic Color Changes: Raynaud’s phenomenon is an extremely common initial symptom, vividly displayed in many Systemic scleroderma symptoms pictures. It involves episodic constriction of small blood vessels in response to cold or stress, leading to distinct color changes in the fingers and toes.
- Pallor (White): The affected digits turn stark white due to lack of blood flow, often accompanied by numbness and coldness.
- Cyanosis (Blue): As oxygen in the trapped blood depletes, the digits may turn blue or purplish.
- Erythema (Red): Upon rewarming, blood flow returns, causing the digits to become red and sometimes painful or tingly.
- Critical Ischemia: Severe Raynaud’s can lead to complications such as digital ulcers (open sores on fingertips) and even gangrene, which are starkly visible in severe Systemic scleroderma symptoms pictures.
- Triphasic Color Changes: Raynaud’s phenomenon is an extremely common initial symptom, vividly displayed in many Systemic scleroderma symptoms pictures. It involves episodic constriction of small blood vessels in response to cold or stress, leading to distinct color changes in the fingers and toes.
- Digital Ulcers and Pitting Scars:
- Painful Open Sores: These are common on the fingertips or around the nails, often appearing as small, necrotic lesions in Systemic scleroderma symptoms pictures. They result from reduced blood flow and are prone to infection.
- Pitting Scars: After ulcers heal, small depressions or “pitting” can remain on the fingertips, a tell-tale sign of chronic microvascular damage often visible in Systemic scleroderma symptoms pictures of the hands.
- Edema (Swelling):
- Puffy Fingers and Hands: In the early stages, Systemic scleroderma symptoms pictures often show noticeable swelling, particularly of the fingers and hands, giving them a “puffy” appearance before significant hardening occurs. This can also affect the feet and face.
- Non-Pitting Edema: Unlike typical edema, the swelling in scleroderma may not pit when pressed, gradually progressing to induration and skin thickening.
- Pigmentary Changes:
- Hyperpigmentation: Darkening of the skin is common, especially in areas of tight skin, giving a mottled appearance in some Systemic scleroderma symptoms pictures.
- Hypopigmentation (“Salt and Pepper” Appearance): Scattered areas of lighter, depigmented skin mixed with darker, hyperpigmented skin can create a characteristic “salt and pepper” look, particularly on the forearms and trunk, which is distinct in Systemic scleroderma symptoms pictures.
- Telangiectasias:
- Visible Capillaries: These are small, dilated blood vessels that appear as tiny red spots or spider veins on the skin, commonly seen on the face, lips, palms, and mucous membranes in many Systemic scleroderma symptoms pictures. They are benign but can be cosmetically bothersome.
- Calcinosis Cutis:
- Calcium Deposits: Firm, white or yellowish deposits of calcium can form under the skin, often over bony prominences or joints, particularly on the fingers and elbows. In Systemic scleroderma symptoms pictures, these can sometimes be seen eroding through the skin, leading to painful ulcers and infection.
Understanding these visual cues from Systemic scleroderma symptoms pictures is vital for differential diagnosis and guiding treatment strategies for Systemic scleroderma patients. The progression seen in various Systemic scleroderma symptoms pictures underscores the importance of monitoring skin changes closely.
Signs of Systemic scleroderma Pictures
Beyond the primary symptoms, specific signs of Systemic scleroderma become apparent in detailed Systemic scleroderma pictures, offering further diagnostic clues. These signs are often subtle initially but become more pronounced as the disease progresses. Observing these characteristic signs in Systemic scleroderma pictures helps clinicians assess disease activity and organ involvement. The visual evidence from Systemic scleroderma pictures provides invaluable insights into the multifaceted nature of the condition, from subtle microvascular changes to overt musculoskeletal manifestations.
Detailed examination of Systemic scleroderma pictures often reveals the following specific signs:
- Nail Fold Capillary Changes:
- Microvascular Abnormalities: A crucial diagnostic sign visible under a capillaroscope but sometimes hinted at in high-resolution Systemic scleroderma pictures of the nail folds. These changes include dilated and tortuous capillaries, loss of capillaries, and hemorrhagic spots, indicating underlying vascular damage.
- Visible Red Spots: Sometimes, small red or dark spots (hemorrhages) are visible at the base of the nails, reflecting capillary damage.
- Mouth and Oral Cavity Changes:
- Microstomia: A reduction in the size of the mouth opening, making dental hygiene and eating difficult. Systemic scleroderma pictures frequently show a noticeably smaller oral aperture.
- Radial Furrowing: Lines or wrinkles radiating outwards from the lips, a direct result of skin tightening around the mouth, prominently featured in many facial Systemic scleroderma pictures.
- Gingival Recession: Tightening of facial skin can also affect gum tissue, leading to gum recession.
- Difficulty with Tongue Protrusion: Tightening of the frenulum beneath the tongue can restrict its movement.
- Joint Contractures and Mobility Restrictions:
- Flexion Contractures: Due to skin tightening over joints, particularly the fingers, elbows, and knees, Systemic scleroderma pictures often show joints stuck in a bent position. This significantly impairs range of motion.
- Difficulty with Grasping: The inability to fully extend fingers or grasp objects is a common functional impairment evident from Systemic scleroderma pictures of affected hands.
- Arthralgia and Arthritis: While not directly visible as a “sign” in Systemic scleroderma pictures, joint pain and inflammation often accompany the physical limitations.
- Hair and Skin Appendage Changes:
- Hair Loss: General thinning or loss of hair, especially in areas of severely tight skin, can be observed in some Systemic scleroderma pictures.
- Dry, Itchy Skin (Pruritus): The hardened skin often loses its natural oils and moisture, leading to dryness and persistent itching. While itching isn’t visible, excoriations (scratch marks) sometimes are.
- Reduced Sweating: Damaged sweat glands in affected skin can lead to reduced sweating in those areas.
- Skin Ulceration Beyond Digits:
- Pressure Ulcers: Tight, thin skin over bony prominences can be more susceptible to pressure sores, especially in bedridden or less mobile patients, which can be seen in advanced Systemic scleroderma pictures.
- Trauma-Induced Ulcers: Reduced elasticity makes the skin more fragile and prone to tears or ulcers from minor trauma.
- Gastrointestinal Manifestations (Indirectly Visual):
- Weight Loss and Malnutrition: While not a direct visual sign of scleroderma itself, Systemic scleroderma pictures of patients with severe GI involvement (e.g., malabsorption, dysphagia) may show signs of significant weight loss and muscle wasting.
- Esophageal Dysmotility: Although not visually apparent externally, severe esophageal involvement can sometimes lead to visible signs such as regurgitation or chronic cough affecting general appearance.
- Pulmonary Hypertension and Fibrosis (Indirectly Visual):
- Cyanosis (Lips/Nail Beds): In severe cases of pulmonary involvement (e.g., pulmonary hypertension or interstitial lung disease), reduced oxygenation can manifest as bluish discoloration of the lips or nail beds, a critical sign to look for in Systemic scleroderma pictures of the face and hands.
- Clubbing of Digits: While less common than in other chronic lung diseases, severe pulmonary fibrosis can, in rare instances, lead to clubbing of the fingers, visible in hand Systemic scleroderma pictures.
These specific signs, when observed in Systemic scleroderma pictures, contribute significantly to the overall clinical picture and help in monitoring disease progression and the effectiveness of Systemic scleroderma treatment. Early recognition of these signs through careful review of Systemic scleroderma pictures is paramount for timely interventions.
Early Systemic scleroderma Photos
Identifying Systemic scleroderma in its nascent stages is critical for better outcomes, and early Systemic scleroderma photos play a pivotal role in this. These photos capture the subtle, often overlooked, initial changes that precede widespread fibrosis and severe organ damage. Early Systemic scleroderma photos typically highlight the first noticeable skin alterations and vascular phenomena. The ability to distinguish these nascent signs in early Systemic scleroderma photos can significantly shorten the diagnostic delay, paving the way for proactive management and interventions.
Here are the key indicators often seen in early Systemic scleroderma photos:
- Puffy Fingers (Edematous Phase):
- Initial Swelling: One of the most common and earliest signs, characterized by non-pitting swelling of the fingers and hands. Early Systemic scleroderma photos often show fingers that appear noticeably plump or “sausage-like.”
- Morning Stiffness: Patients may report morning stiffness accompanying the swelling, which is not directly visible but contributes to the context of early Systemic scleroderma photos.
- Distal Swelling: The swelling typically starts distally, affecting the tips of the fingers, before potentially progressing proximally.
- Raynaud’s Phenomenon Onset:
- Frequent Attacks: Early Systemic scleroderma photos often depict recurrent episodes of digital color changes (pallor, cyanosis, rubor) in response to cold or stress. This can be one of the very first symptoms, sometimes preceding skin thickening by months or even years.
- Severity of Attacks: While initial attacks may be mild, their increasing frequency and intensity, along with prolonged color changes, can be indicative of underlying systemic disease, even if not directly captured in static early Systemic scleroderma photos.
- Absence of Digital Ulcers: In very early stages, significant digital ulcers may not be present, distinguishing it from more advanced cases.
- Subtle Skin Thickening:
- Slight Induration: While not as prominent as in later stages, early Systemic scleroderma photos might show subtle firmness or tightness of the skin, often starting on the fingers (sclerodactyly). The skin may lose some of its normal pliability.
- Shiny Appearance: The skin over the fingers or hands may begin to appear slightly shiny, indicating the very beginning of dermal fibrosis.
- Reduced Wrinkles: Fine lines or wrinkles, especially over the knuckles, may start to diminish, a subtle but observable change in early Systemic scleroderma photos.
- Nail Fold Capillary Abnormalities (Microscopic):
- Early Capillary Changes: Though requiring magnification, the presence of dilated loops, microhemorrhages, or slight loss of capillaries can be seen. While not visible to the naked eye, it’s a critical early marker that informs the interpretation of other early Systemic scleroderma photos.
- Absence of Severe Angiopathy: Large avascular areas or extensive capillary loss are typically not seen in the very early stages.
- Mild Facial Tightening:
- Subtle Expression Changes: Early Systemic scleroderma photos of the face might reveal very slight tightening around the mouth, or a reduction in the ease of smiling, before full microstomia develops.
- Perioral Lines: Initial fine lines radiating from the lips might become slightly more prominent.
- Musculoskeletal Symptoms:
- Joint Swelling and Pain: While not a visual ‘photo’ symptom, early Systemic scleroderma photos showing puffy fingers often accompany reports of non-erosive arthritis or arthralgia.
- Tenderness: General tenderness in affected areas of the skin or joints can be a subjective complaint in early stages.
- General Fatigue and Malaise:
- Non-Specific Symptoms: While not appearing in early Systemic scleroderma photos, systemic symptoms like persistent fatigue, general weakness, and unexplained weight loss can be present in the early stages and should prompt further investigation alongside visual cues.
The collection and careful review of early Systemic scleroderma photos are essential for monitoring disease progression and initiating appropriate Systemic scleroderma treatment strategies. Prompt identification based on these visual cues can significantly impact the long-term prognosis for individuals with Systemic scleroderma.
Skin rash Systemic scleroderma Images
While Systemic scleroderma is not typically characterized by a “rash” in the conventional sense of an eruptive, itchy, or inflammatory skin eruption, there are several distinctive skin changes and manifestations that might be misinterpreted as or accompany a rash. These unique skin presentations are critical for identification in Systemic scleroderma images. Understanding these visual characteristics is key to differentiating Systemic scleroderma skin involvement from other dermatological conditions. The term “skin rash Systemic scleroderma images” often refers to the specific, non-inflammatory skin alterations that are hallmarks of the disease’s cutaneous fibrosis and vascular damage, rather than a typical allergic or infective rash.
Here are the common skin manifestations often searched for under “skin rash Systemic scleroderma images”:
- Sclerodermatous Skin Changes (The Primary “Rash” in Scleroderma):
- Tightness and Shininess: The most prevalent visual feature in skin rash Systemic scleroderma images is the progressive tightening, thickening, and shiny appearance of the skin. This isn’t a rash, but a fundamental change in skin texture and elasticity. It often starts on the fingers (sclerodactyly) and can spread.
- Loss of Skin Folds: Normal skin creases, especially over joints, disappear as the skin becomes taut. This smooth, waxy appearance is distinct in skin rash Systemic scleroderma images.
- Induration: The skin feels firm and tethered, not easily pinched or lifted, a feature clearly visible through palpation but also conveyed by the taut appearance in skin rash Systemic scleroderma images.
- Color Variation: Affected skin may appear pale, waxy, hyperpigmented (darker), or show a “salt and pepper” pattern.
- Telangiectasias:
- Spider Veins: These are small, dilated blood vessels that appear as bright red spots or fine lines on the skin, resembling spiderwebs. They are common on the face, lips, palms, and mucous membranes. These distinct vascular lesions are frequently highlighted in skin rash Systemic scleroderma images.
- Mat-like Telangiectasias: In some cases, numerous telangiectasias cluster together, forming larger, red, mat-like areas.
- Calcinosis Cutis:
- Subcutaneous Lumps: Firm, white, or yellowish deposits of calcium under the skin, often over bony prominences (fingers, elbows, knees). When these deposits break through the skin, they can appear as chalky white material surrounded by inflamed skin, which can look like a persistent, ulcerated “rash” in skin rash Systemic scleroderma images.
- Associated Ulcers: The skin overlying calcinosis can ulcerate, leading to chronic, painful sores that might be mistaken for an unusual rash or persistent lesion.
- Pigmentary Changes:
- Hyperpigmentation: Diffuse darkening of the skin, resembling a tan but often uneven, can be a feature in skin rash Systemic scleroderma images, particularly in areas of chronic inflammation or friction.
- Salt and Pepper Pigmentation: Areas of depigmentation (lightening) interspersed with hyperpigmentation, creating a mottled or freckled appearance, especially on the forearms and trunk, is a specific visual sign often sought in skin rash Systemic scleroderma images.
- Digital Ulcers and Pitting Scars:
- Ischemic Lesions: While not a rash, these painful sores on the fingertips, which can be necrotic (dark tissue) or open, are critical to identify in skin rash Systemic scleroderma images related to hand involvement. They represent severe microvascular damage.
- Healed Pits: Small, permanent depressions on the fingertips are visual markers of previous ulcers.
- Pruritus and Excoriations:
- Itchy Skin: The tight, dry, and often inflamed skin can be intensely itchy. While pruritus itself isn’t a visual rash, the resulting excoriations (scratch marks), erythema (redness), and secondary skin infections (e.g., impetigo-like lesions) due to scratching can appear as a “rash” in some skin rash Systemic scleroderma images.
- Lichenification: Chronic scratching can lead to thickening and darkening of the skin in affected areas.
- Edema (Early Stage):
- Puffy Appearance: In the initial inflammatory phase, particularly of the hands and face, swelling can make the skin appear red and somewhat “puffy,” which might be confused with an acute inflammatory rash in skin rash Systemic scleroderma images. This typically progresses to induration.
- Specific Overlap Syndromes:
- Dermatomyositis-like Rash: In patients with overlap features of dermatomyositis, true rashes like Gottron’s papules (red or violaceous papules over knuckles) or heliotrope rash (purplish discoloration around the eyelids) can be present. These are true rashes but occur in the context of an overlap syndrome.
- Lupus-like Rash: Some patients with scleroderma may also have features of lupus, including malar rash (butterfly rash on the face) or discoid lupus lesions. These would be true rashes, but they indicate an overlap condition rather than pure scleroderma.
Therefore, when reviewing “skin rash Systemic scleroderma images,” it is essential to distinguish the unique sclerodermatous changes from typical inflammatory rashes. The visual cues provided by these images are fundamental for accurate diagnosis and tailored Systemic scleroderma treatment.
Systemic scleroderma Treatment
Systemic scleroderma treatment is a complex, multidisciplinary endeavor aimed at managing symptoms, slowing disease progression, preventing organ damage, and improving quality of life. Given the heterogeneity of Systemic scleroderma symptoms pictures and the diverse organ involvement, treatment plans are highly individualized. There is currently no cure for Systemic scleroderma, so therapies focus on mitigating the specific manifestations and complications observed in Systemic scleroderma symptoms pictures and other diagnostic assessments. Early initiation of appropriate Systemic scleroderma treatment is crucial, especially for preventing irreversible damage to vital organs.
The main approaches to Systemic scleroderma treatment include:
Pharmacological Treatments:
Medications are tailored to the specific organ systems involved and the severity of symptoms.
- Immunosuppressants and Immunomodulators:
- Methotrexate: Often used for skin involvement and inflammatory arthritis, particularly in early diffuse cutaneous systemic scleroderma. Helps to reduce skin thickening and joint inflammation.
- Mycophenolate Mofetil (MMF): Effective for slowing skin thickening and often used in patients with interstitial lung disease (ILD) to stabilize or improve lung function.
- Cyclophosphamide: A more potent immunosuppressant, typically reserved for severe or rapidly progressive interstitial lung disease or severe systemic vasculitis. Its use requires careful monitoring due to potential side effects.
- Azathioprine: May be used for maintenance therapy, especially for ILD or skin involvement, after initial control with other agents.
- Rituximab: A B-cell depleting agent, increasingly used for refractory skin disease and interstitial lung disease in Systemic scleroderma.
- Tocilizumab: An IL-6 receptor antagonist, showing promise in some patients with rapidly progressing skin fibrosis and joint involvement.
- Vasodilators and Antiplatelet Agents (for Raynaud’s and Vascular Complications):
- Calcium Channel Blockers (e.g., Nifedipine, Amlodipine): First-line therapy for Raynaud’s phenomenon to reduce frequency and severity of attacks and improve blood flow.
- Phosphodiesterase-5 (PDE5) Inhibitors (e.g., Sildenafil, Tadalafil): Used for severe Raynaud’s, digital ulcers, and pulmonary hypertension. They promote vasodilation.
- Prostaglandin Analogs (e.g., Iloprost, Epoprostenol): Given intravenously for severe Raynaud’s, critical digital ischemia, and pulmonary hypertension. These are powerful vasodilators.
- Endothelin Receptor Antagonists (ERAs) (e.g., Bosentan, Ambrisentan): Primarily used for pulmonary arterial hypertension (PAH) and to prevent new digital ulcers.
- Anticoagulants/Antiplatelet Agents (e.g., Aspirin): May be used to prevent clot formation in patients with severe Raynaud’s or digital ulcers.
- Antifibrotic Agents:
- Nintedanib: An oral tyrosine kinase inhibitor approved for the treatment of systemic scleroderma-associated interstitial lung disease (SSc-ILD) to slow the rate of decline in lung function.
- Gastrointestinal Management:
- Proton Pump Inhibitors (PPIs) (e.g., Omeprazole): Essential for managing gastroesophageal reflux disease (GERD), a very common manifestation of Systemic scleroderma, to prevent esophagitis and strictures.
- Prokinetics (e.g., Metoclopramide): Used to improve esophageal and gastric motility in some patients.
- Antibiotics: For small intestinal bacterial overgrowth (SIBO), which can cause bloating and malabsorption.
- Renal Crisis Management:
- ACE Inhibitors (e.g., Captopril): The cornerstone of treatment for scleroderma renal crisis, a life-threatening complication, to lower blood pressure and protect kidney function. Aggressive and prompt treatment is critical.
Non-Pharmacological and Supportive Treatments:
These therapies complement medications and are vital for managing daily symptoms and improving quality of life.
- Physical and Occupational Therapy:
- Stretching and Exercise: To maintain joint mobility, prevent contractures, and improve strength, crucial given the skin tightening seen in Systemic scleroderma symptoms pictures.
- Hand Exercises: Specific exercises to maintain dexterity and function of the fingers and hands.
- Splinting: May be used to prevent or correct joint contractures.
- Energy Conservation Techniques: To manage fatigue.
- Skin Care:
- Moisturizers and Emollients: To combat dry, itchy skin and maintain skin integrity.
- Avoiding Harsh Soaps: To prevent further skin irritation.
- Wound Care: Meticulous care for digital ulcers and other skin lesions to prevent infection and promote healing. This involves dressings, topical antibiotics, and debridement if necessary.
- Raynaud’s Phenomenon Management:
- Warm Clothing: Wearing layers, gloves, and warm socks.
- Avoiding Cold Exposure: Minimizing exposure to cold temperatures.
- Biofeedback: Techniques to help control body temperature.
- Smoking Cessation: Crucial to reduce vasoconstriction and improve blood flow.
- Pain Management:
- NSAIDs: For mild joint pain or inflammation (used cautiously due to potential GI side effects).
- Analgesics: As needed for chronic pain.
- Nutrition and Diet:
- Small, Frequent Meals: To manage reflux and improve nutrient absorption.
- Soft Foods: For patients with dysphagia or microstomia.
- Nutritional Supplements: To address malabsorption or weight loss.
- Upright Position After Eating: To reduce reflux.
- Psychological Support:
- Counseling and Support Groups: To help cope with the chronic nature of the disease, body image changes (often visible in Systemic scleroderma symptoms pictures), and psychological impact.
- Addressing Depression and Anxiety: Common in chronic illnesses.
- Surgical Interventions (Rare):
- Digital Sympathectomy: Rarely performed for severe, refractory digital ischemia or ulcers.
- Amputation: In extreme cases of gangrene.
- Calcium Deposit Removal: Surgical excision of particularly large, painful, or infected calcinosis deposits.
- Joint Contracture Release: Surgery to improve function in severe, debilitating contractures.
Continuous monitoring of organ function, disease activity, and side effects of Systemic scleroderma treatment is essential. Regular follow-up with a rheumatologist and other specialists (e.g., pulmonologist, gastroenterologist, dermatologist, nephrologist) ensures a comprehensive and adaptive Systemic scleroderma treatment plan, aiming to improve the overall prognosis and quality of life for individuals living with this challenging condition.