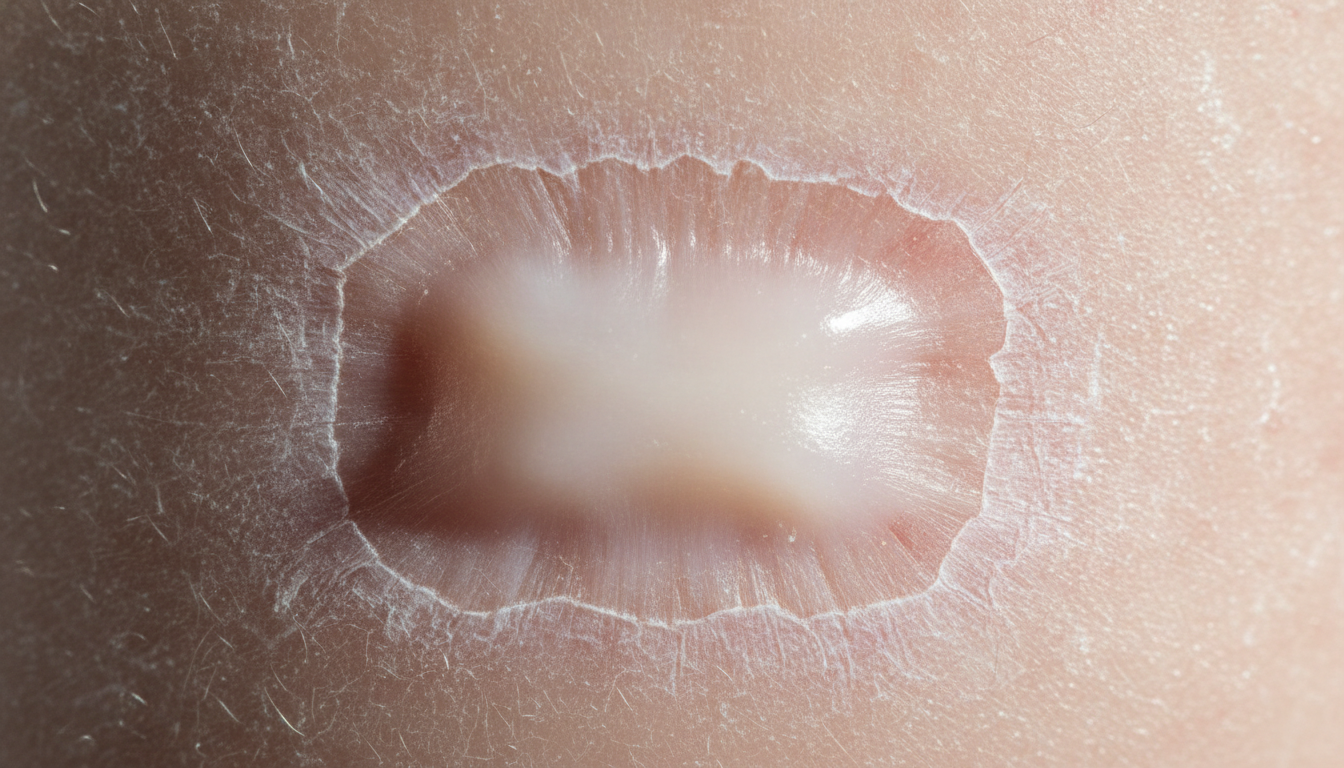
This comprehensive guide delves into the visual manifestations of Synechiae, offering detailed descriptions to accompany Synechiae symptoms pictures. Understanding these visual cues is crucial for early identification and appropriate management, especially when observing the characteristic patterns associated with various forms of Synechiae across different anatomical sites.
Synechiae Symptoms Pictures
When examining Synechiae symptoms pictures, observers will typically note the presence of abnormal fibrous adhesions, which are essentially bands of scar tissue that connect surfaces that are normally separate. These adhesions can vary significantly in appearance, ranging from thin, delicate membranes to thick, dense, and opaque bands, depending on their location, etiology, and duration. The visual presentation of synechiae is often highly indicative of the underlying pathology, whether it stems from inflammation, trauma, infection, or a congenital anomaly. For instance, genital synechiae, particularly labial adhesions in prepubertal girls, often appear as a pale, translucent, or sometimes whitish membrane spanning the labia minora. This fusion can obscure the urethral and vaginal openings to varying degrees, from partial to complete occlusion. The visual impact on the genitalia is unmistakable, often showing a smooth, uninterrupted surface where there should be distinct separation.
Intraocular synechiae, visible through ophthalmological examination, present as adhesions within the eye. Posterior synechiae involve the iris adhering to the anterior capsule of the lens, often appearing as irregular pupil shapes (festooned pupil) when the pupil dilates, with pigmented spots from the iris adhering to the lens. Anterior synechiae involve the iris adhering to the cornea or trabecular meshwork, potentially visible as an irregular iris margin or iris tissue pulled towards the periphery of the cornea. These ocular adhesions restrict pupil movement and can impede aqueous humor outflow, leading to complications like glaucoma. The characteristic visual features in Synechiae symptoms pictures include:
- Vulvar Synechiae (Labial Adhesions):
- Appearance: A pale, whitish, or translucent membrane bridging the labia minora.
- Location: Typically in the midline, extending from the clitoris towards the perineum.
- Degree of Fusion: Can be partial, allowing small openings for urine, or complete, fully obscuring the vaginal introitus and urethra.
- Texture: Often smooth and contiguous with the surrounding skin, sometimes with a faint visible demarcation line.
- Associated Symptoms: Urinary symptoms (spraying, dribbling), recurrent urinary tract infections (UTIs), local irritation, difficulty with hygiene.
- Penile Synechiae:
- Appearance: Adhesions between the glans penis and the foreskin (prepuce), often appearing as localized bands or broader areas of fusion.
- Location: Most commonly post-circumcision, where raw surfaces adhere during healing, or due to inflammation in uncircumcised males.
- Degree of Fusion: Can range from small, discrete bands near the corona to more extensive adherence restricting foreskin retraction.
- Texture: Fibrous and often pale, contrasting with the more vascularized glans tissue.
- Associated Symptoms: Difficulty with foreskin retraction, pain during erection or hygiene, accumulation of smegma, recurrent infections (balanitis).
- Intraocular Synechiae (Anterior and Posterior):
- Posterior Synechiae:
- Appearance: Iris tissue adherent to the lens capsule, visible as irregular pupil margins, especially upon dilation.
- Pigmentation: Often dark pigment clumps from the iris epithelium are visible on the lens surface.
- Impact: Impaired pupil reactivity, potential for pupillary block glaucoma.
- Anterior Synechiae:
- Appearance: Iris tissue adhering to the corneal endothelium or trabecular meshwork.
- Location: Often visible at the angle of the anterior chamber, pulling the iris anteriorly.
- Impact: Obstruction of aqueous outflow, leading to elevated intraocular pressure and secondary glaucoma.
- Posterior Synechiae:
- Nasal Synechiae:
- Appearance: Fibrous bands bridging adjacent nasal structures, such as the septum to the turbinates or turbinates to the lateral nasal wall.
- Location: Within the nasal cavity, often post-surgical intervention (e.g., septoplasty, turbinate reduction) or trauma.
- Texture: Whitish to pinkish fibrous tissue, often robust enough to impede airflow.
- Associated Symptoms: Nasal obstruction, difficulty breathing through the nose, post-nasal drip, epistaxis (nosebleeds) upon disruption.
- Uterine Synechiae (Asherman’s Syndrome):
- Appearance (Hysteroscopic): Fibrous bands or sheets within the uterine cavity, varying from delicate to dense and vascularized.
- Location: Connecting opposing walls of the uterus, potentially partially or completely obliterating the cavity.
- Associated Symptoms: Amenorrhea, hypomenorrhea, recurrent miscarriage, infertility, pelvic pain. While not externally visible, the symptoms are severe and functional.
Each type of synechiae presents with distinct visual characteristics, making careful observation of Synechiae symptoms pictures an invaluable tool for clinical understanding and patient education. The degree of tissue fusion, color, location, and the functional impairment caused are critical aspects highlighted in photographic documentation.
Signs of Synechiae Pictures
Observing signs of Synechiae pictures helps clinicians and patients identify the objective, measurable indicators of these adhesive conditions. Unlike symptoms, which are subjective experiences, signs are observable during a physical examination or through specialized imaging. A key sign in many forms of synechiae is the visible obliteration of normal anatomical landmarks. For example, in vulvar adhesions, the normal separation of the labia minora is replaced by a fused membrane, making it difficult or impossible to visualize the clitoris, urethral meatus, or vaginal introitus without gentle traction. The presence of such a membrane itself is a definitive sign, often appearing as a uniform, pale bridge of tissue.
In the context of penile adhesions, a significant sign is the inability to fully retract the foreskin (prepuce) over the glans penis, even with gentle attempts. This restriction often reveals specific fibrous bands connecting the glans to the inner surface of the foreskin. These bands are distinct from congenital phimosis, as they represent acquired scar tissue. The physical examination of a patient with suspected synechiae will meticulously look for these adhesive structures. Furthermore, any associated signs of inflammation or infection, such as erythema (redness), edema (swelling), or discharge, which might have contributed to the synechiae formation, are also important diagnostic clues.
For intraocular synechiae, the signs are directly visualized during an ophthalmological exam. The most prominent sign of posterior synechiae is an irregular, scalloped, or distorted pupil shape, especially noticeable after the application of mydriatic (pupil-dilating) drops. The iris fails to dilate uniformly, remaining tethered to the lens at points of adhesion. Pigment deposits on the anterior lens capsule also serve as a strong indicator. In anterior synechiae, gonioscopy (a specialized examination of the anterior chamber angle) reveals iris tissue adhering to the trabecular meshwork or cornea. These visual signs directly demonstrate the anatomical alteration caused by the adhesions. The key signs of Synechiae include:
- Genital Synechiae:
- Visible Fusion: Direct observation of skin or mucosal surfaces being abnormally joined.
- Obscured Openings: Inability to fully visualize the urethra and/or vagina due to an overlying membrane in vulvar synechiae.
- Restricted Movement: Inability to retract the foreskin in penile synechiae, or restricted separation of labia.
- Erythema/Inflammation: Secondary signs of irritation, redness, or mild swelling around the fused areas, often indicating an ongoing inflammatory process or hygiene issues.
- Discharge: Accumulation of urine, smegma, or other secretions trapped behind the adhesions, leading to local irritation or infection.
- Ocular Synechiae:
- Irregular Pupil Shape: Distortion of the pupil (e.g., festooned pupil) due to adhesions tethering the iris to the lens or cornea.
- Pigment on Lens: Presence of dark, irregular pigment deposits on the anterior lens capsule, indicating posterior synechiae.
- Shallow Anterior Chamber: In cases of extensive anterior synechiae or pupillary block, the anterior chamber may appear shallower.
- Elevated Intraocular Pressure: A measurable sign, often a consequence of synechiae impeding aqueous outflow, leading to glaucoma.
- Absence of Red Reflex (Severe Cases): In very severe or long-standing posterior synechiae with secondary cataract, the red reflex may be diminished.
- Nasal Synechiae:
- Direct Visualization: Endoscopic or rhinoscopic visualization of fibrous bands connecting nasal structures.
- Nasal Obstruction: Objective measurement of airflow reduction using rhinomanometry or patient-reported persistent blockage.
- Mucosal Changes: Localized irritation, crusting, or inflammation at the site of adhesion or surrounding tissues due to altered airflow.
- Epistaxis: Evidence of recurrent nosebleeds, often from trauma to the delicate adhesion tissue.
- Uterine Synechiae (Hysteroscopy):
- Direct Visualization: Hysteroscopic confirmation of fibrous bands or septa within the uterine cavity.
- Cavity Distortion: Visualization of a distorted, partially, or completely obliterated uterine cavity.
- Endometrial Thinning: Areas of endometrial damage or atrophy associated with the synechiae.
- Absence of Normal Endometrial Undulations: A smooth, featureless uterine wall where folds should be present.
The careful documentation of these objective signs of Synechiae, often accompanied by photographic or video evidence, is essential for accurate diagnosis, monitoring disease progression, and planning effective interventions. These visible cues provide concrete evidence of the anatomical changes that result in functional impairment and patient discomfort.
Early Synechiae Photos
Identifying early Synechiae photos is crucial for prompt intervention and preventing the progression to more extensive and complicated adhesions. In the initial stages, synechiae may appear subtle, often as delicate, thin membranes or nascent fibrous bands that are easily missed without careful scrutiny. The key to recognizing early synechiae lies in detecting these minor changes before they consolidate into dense, robust scar tissue. For example, in early vulvar synechiae, a faint, translucent film might be observed beginning to bridge the posterior labia minora. This early stage might present with minimal symptoms or only very mild urinary issues, such as a slightly altered urine stream, making visual identification paramount.
Similarly, early penile synechiae might manifest as very fine, almost thread-like adhesions between the glans and foreskin, often visible only during a careful and complete retraction attempt. These initial bands are usually pale and delicate, contrasting with the more pronounced, thicker bands seen in established adhesions. The importance of early detection cannot be overstated, as intervention at this stage is typically simpler, less invasive, and more successful. Often, non-surgical methods such as topical creams are highly effective for mild synechiae, preventing the need for surgical separation later. The differentiation between early and established synechiae often lies in the thickness, vascularity, and resilience of the adhesive tissue. Early adhesions tend to be avascular or poorly vascularized, pliable, and relatively easy to separate, while older adhesions are thicker, denser, and more fibrous.
In the eye, early intraocular synechiae might present as very subtle irregularities in the pupil margin, perhaps only one or two small points of adhesion between the iris and lens, detectable only after pharmacological pupil dilation. These nascent adhesions may not yet cause significant visual impairment or elevated intraocular pressure, but their presence signals an underlying inflammatory process that needs urgent attention. Recognizing these subtle initial changes in early Synechiae photos enables clinicians to initiate treatment before extensive scarring occurs, thus preserving function and preventing long-term complications. Key features in early Synechiae photos to look for include:
- Vulvar Synechiae (Early Stage):
- Faint Translucency: A very thin, almost invisible, film or web-like structure beginning to form, often centrally or posteriorly.
- Incomplete Fusion: The membrane may not fully span the labia, leaving small gaps or fenestrations.
- Pliable Tissue: The adhesions feel soft and yield slightly to gentle separation attempts, unlike rigid, dense adhesions.
- Minimal Symptoms: Often asymptomatic or very mild irritation, occasional urinary stream deviation.
- Normal Surrounding Tissue: Absence of significant inflammation or redness of the adjacent labia.
- Penile Synechiae (Early Stage):
- Fine Fibrous Strands: Delicate, thread-like adhesions, often singular or few, connecting the glans to the foreskin.
- Partial Retraction Difficulty: Foreskin retraction is only slightly impeded, not completely blocked.
- Localized Adhesion Points: Adhesions appear as distinct, small points of attachment rather than broad sheets.
- Minimal Discomfort: Pain or discomfort only upon forceful or complete retraction.
- Absence of Extensive Scarring: No visible significant fibrous plaque or thick, white scar tissue.
- Intraocular Synechiae (Early Stage):
- Isolated Adhesion Points: One or two small areas where the iris is tethered to the lens (posterior) or cornea (anterior).
- Mild Pupil Irregularity: Slight distortion of the pupil margin, particularly noticeable after mydriatics.
- Faint Pigment Deposits: Minimal, sparse pigment granules on the lens capsule.
- Normal Intraocular Pressure: Usually no significant elevation in early stages, as outflow pathways are not yet extensively blocked.
- Subtle Inflammatory Signs: May be accompanied by mild anterior chamber inflammation (flare and cells) indicating recent uveitis.
- Nasal Synechiae (Early Stage):
- Delicate Mucosal Bridges: Thin, vascularized mucosal bands bridging nasal structures, rather than thick scar tissue.
- Small Size: Adhesions are limited in extent, not significantly obstructing the nasal passage.
- Easily Separable: May be separated with minimal effort during endoscopic examination.
- Mild Nasal Symptoms: Intermittent or mild nasal blockage, not constant or severe.
- Recent Surgical History: Often seen within weeks to months post-nasal surgery, indicating healing complications.
The ability to distinguish these subtle findings in early Synechiae photos from established, more problematic adhesions is key to implementing timely and less invasive treatments, thereby improving patient outcomes and minimizing the long-term impact of these conditions. Regular follow-up and patient education on what to observe are critical in these scenarios.
Skin rash Synechiae Images
When reviewing skin rash Synechiae images, it’s important to understand that synechiae themselves are not typically a “rash.” Instead, they are the result of inflammatory skin or mucosal conditions, trauma, or surgical interventions that lead to tissue fusion during healing. Therefore, these images often depict the *consequences* of a preceding rash-like inflammatory process, or they might show synechiae coexisting with an ongoing dermatological condition that predisposes to their formation. A classic example is lichen sclerosus, a chronic inflammatory skin condition that frequently affects the anogenital region and is a primary cause of vulvar synechiae in both children and adults. Skin rash Synechiae images in this context would show the characteristic white, thin, crinkled “parchment paper” skin of lichen sclerosus alongside the resulting adhesions.
Another scenario involves severe or recurrent inflammatory processes, such as vulvovaginitis or balanitis, which, if left untreated or poorly managed, can lead to erosions and subsequent fibrous healing with adhesion formation. In such cases, skin rash Synechiae images might display areas of active inflammation (redness, scaling, excoriation, maceration) adjacent to or underlying the developing synechiae. For instance, a child with persistent candidal diaper rash that extends to the labia might develop synechiae as part of the healing process. The visual presentation of the rash itself, such as its distribution, morphology, and associated symptoms, provides critical clues about the etiology of the synechiae. It emphasizes that synechiae are often not isolated entities but part of a broader dermatological or inflammatory picture.
In surgical contexts, although not a “rash,” the initial post-operative wound healing can be considered a form of localized inflammation. If raw surfaces are allowed to approximate, synechiae can form. Images might show granulation tissue, erythema, and signs of wound healing alongside the initial fibrous connections. Therefore, skin rash Synechiae images are less about a single entity and more about the spectrum of inflammatory and healing processes that culminate in synechiae formation. It requires a keen eye to connect the predisposing skin condition with the subsequent development of tissue fusion. Key aspects to consider when evaluating skin rash Synechiae images include:
- Lichen Sclerosus (Predisposing Condition):
- Appearance: Whitish, atrophic, crinkled, “parchment-like” skin in the anogenital region.
- Associated Features: Loss of normal labial architecture (clitoral hood fusion, labial flattening), purpura, fissures, and the formation of synechiae (e.g., labial adhesions, perianal scarring).
- Synechiae Appearance: Often appear as pale, rigid bands formed within the sclerotic tissue.
- Symptoms: Pruritus (itching), dyspareunia, pain, often preceding the visual synechiae.
- Severe Inflammatory Dermatitis (e.g., Atopic Dermatitis, Contact Dermatitis, Psoriasis):
- Appearance: Erythematous, scaly, eczematous, or lichenified plaques in affected areas, potentially leading to excoriations and secondary infection.
- Location: If occurring in intertriginous or mucosal areas (e.g., groin, labia, glans), intense inflammation can lead to raw surfaces and subsequent adhesion formation.
- Synechiae Formation: Post-inflammatory healing can result in delicate to robust adhesions, often with a history of recurrent flares.
- Symptoms: Intense itching, burning, pain, preceding the development of fusion.
- Infectious Vulvovaginitis or Balanitis:
- Appearance: Erythema, edema, discharge (e.g., candidiasis, bacterial vaginosis), often with erosions or ulcerations.
- Location: Affecting the vulva, vagina, or glans penis/foreskin.
- Synechiae Formation: Persistent or severe inflammation and subsequent healing with raw surface apposition can lead to localized adhesions.
- Symptoms: Itching, burning, pain, dysuria, malodor, often indicating active infection.
- Post-Traumatic or Post-Surgical Healing (with inflammation):
- Appearance: Granulation tissue, areas of re-epithelialization, surgical scars, sometimes with erythema or signs of local infection.
- Location: Any area where raw surfaces come into prolonged contact during healing (e.g., nasal cavity post-septoplasty, labia post-trauma).
- Synechiae Formation: Fibrous bands forming between adjacent healing surfaces.
- History: Recent trauma or surgery is a strong indicator.
Understanding the interplay between inflammatory skin conditions (rashes) and synechiae formation is vital for accurate diagnosis and comprehensive management. Skin rash Synechiae images serve as a powerful educational tool to highlight these causal relationships, promoting a holistic view of the patient’s dermatological and anatomical health.
Synechiae Treatment
Synechiae treatment aims to separate the adhered tissues and prevent recurrence, thereby restoring normal anatomy and function, and alleviating symptoms. The approach to treatment is highly dependent on the location, extent, etiology, and duration of the synechiae, as well as the patient’s age and overall health. For many forms of synechiae, particularly genital synechiae in children, conservative management is often the first line of treatment, utilizing topical medications to encourage separation. However, more extensive or resistant adhesions may require surgical intervention, known as adhesiolysis. Post-treatment care is crucial for preventing recurrence, often involving barrier methods, regular separation exercises, or continued use of topical agents.
In cases of vulvar synechiae (labial adhesions) in prepubertal girls, the cornerstone of treatment is typically topical estrogen cream. This method is highly effective due to the undeveloped nature of the labial tissue in young girls, which responds well to hormonal stimulation, leading to thinning and eventual separation of the adhesion. Gentle digital separation by a clinician can also be performed, often after softening the adhesion with cream. For older, denser, or recurrent labial adhesions, a minor surgical procedure might be necessary. Similarly, penile synechiae can often be managed with gentle manual lysis or the application of topical corticosteroids, though surgical adhesiolysis might be required for resistant cases, especially those causing functional problems.
Intraocular synechiae treatment is more complex and often involves a combination of medical and surgical approaches. Medical management primarily focuses on aggressively treating the underlying inflammation (e.g., uveitis) with corticosteroids to prevent further adhesion formation. For existing posterior synechiae, pupil dilation drops (mydriatics) are used to mechanically break the adhesions. If medical methods fail, or if complications like pupillary block glaucoma develop, surgical procedures such as laser iridotomy or surgical synechiolysis (using instruments to break adhesions) may be necessary. Nasal synechiae treatment almost invariably requires surgical lysis, often endoscopically, to remove the fibrous bands and restore nasal airflow. Post-operative measures, such as placement of nasal splints or stents and regular saline irrigations, are vital to prevent re-adhesion. Detailed lists of Synechiae treatment options include:
- Non-Surgical Management (Conservative Treatment):
- Topical Estrogen Cream (for Genital Synechiae, especially labial):
- Mechanism: Promotes epithelialization and thinning of the adhesion, leading to spontaneous separation.
- Application: Small amount applied directly to the adhesion once or twice daily for 2-4 weeks.
- Success Rate: High, often exceeding 80-90% for labial adhesions in children.
- Follow-up: Crucial to prevent recurrence with continued, less frequent application or barrier creams.
- Topical Corticosteroid Creams (for various types, especially inflammatory causes):
- Mechanism: Reduces inflammation, softens fibrous tissue, and can aid in separation.
- Application: Applied directly to the adhesion, as prescribed, for a specific duration.
- Uses: Effective for penile synechiae, or labial synechiae in older girls/women with underlying inflammatory conditions like lichen sclerosus.
- Gentle Manual Lysis/Separation:
- Technique: Performed by a clinician, often after applying topical cream to soften the adhesion.
- Indications: For thin, delicate adhesions that can be separated with minimal force.
- Post-Procedure: Application of barrier creams or estrogen cream to prevent re-adhesion.
- Mydriatic Eye Drops (for Posterior Intraocular Synechiae):
- Mechanism: Dilates the pupil, mechanically breaking delicate adhesions between the iris and lens.
- Medications: Cyclopentolate, atropine, phenylephrine.
- Application: Used to achieve maximum pupil dilation, often repeatedly.
- Topical Estrogen Cream (for Genital Synechiae, especially labial):
- Surgical Management (Adhesiolysis):
- Surgical Lysis/Separation (for Genital and Nasal Synechiae):
- Technique: Incision or blunt dissection of the fibrous bands using surgical instruments (scalpel, scissors, or laser).
- Anesthesia: Local, regional, or general anesthesia depending on extent and patient age.
- Indications: Failed conservative treatment, thick/dense adhesions, functional impairment (e.g., urinary obstruction, significant pain, nasal blockage).
- Post-operative Care: Crucial for preventing recurrence; may involve barrier creams, estrogen, dilators, or splints.
- Laser Synechiolysis/Iridotomy (for Intraocular Synechiae):
- Technique: YAG laser used to break posterior synechiae or create a peripheral iridotomy to relieve pupillary block.
- Advantages: Minimally invasive, precise, rapid procedure.
- Indications: Persistent pupillary block, resistant posterior synechiae, or anterior synechiae impacting aqueous humor outflow.
- Hysteroscopic Adhesiolysis (for Uterine Synechiae/Asherman’s Syndrome):
- Technique: Endoscopic removal of intrauterine adhesions using scissors, electrosurgery, or laser under direct visualization.
- Goal: Restore normal uterine cavity architecture to improve fertility and menstrual function.
- Post-operative Care: Often includes estrogen therapy to promote endometrial regrowth, IUD placement, or balloon insertion to prevent re-adhesion.
- Surgical Lysis/Separation (for Genital and Nasal Synechiae):
- Prevention of Recurrence:
- Topical Maintenance Therapy: Continued, less frequent use of estrogen or barrier creams after successful separation of genital synechiae.
- Dilators/Stents: Placement of temporary devices (e.g., nasal splints, uterine balloons, vaginal dilators) to keep surfaces separated during healing.
- Regular Separation Exercises: Gentle manual separation by the patient or caregiver, especially important for genital adhesions.
- Anti-inflammatory Agents: Continued management of underlying inflammatory conditions (e.g., uveitis, lichen sclerosus) to prevent new adhesion formation.
- Hygiene: Meticulous anogenital hygiene to prevent irritation and infection that can predispose to adhesions.
Effective Synechiae treatment involves a multidisciplinary approach, often combining medical and surgical interventions tailored to the specific type and severity of the adhesions. Patient education regarding the nature of synechiae, the chosen treatment plan, and the importance of post-treatment care is vital for achieving successful long-term outcomes and minimizing recurrence rates.