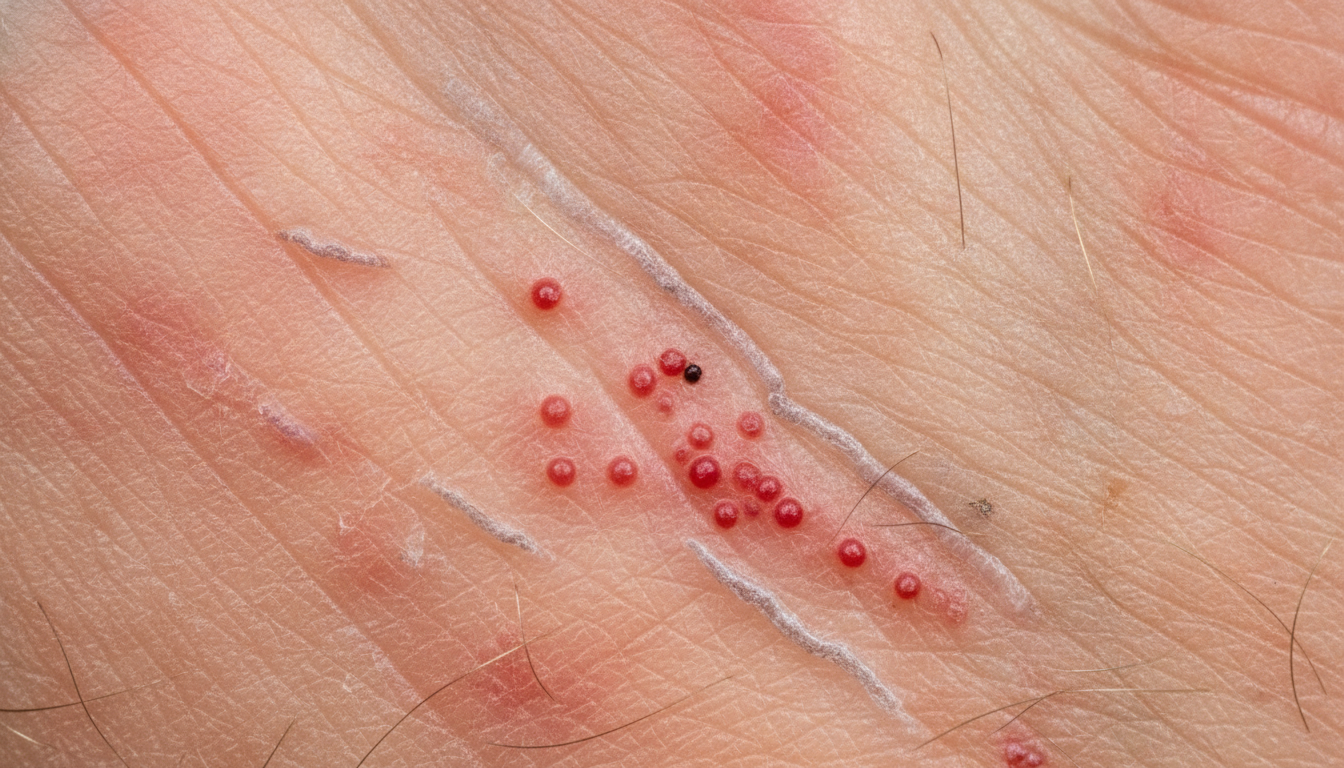
Understanding the visual manifestations of scabies is crucial for timely identification and treatment. This detailed guide explores the various scabies on the body symptoms pictures, providing comprehensive insights into how this parasitic infestation presents across different skin types and affected areas. Early recognition of these signs can significantly improve outcomes and prevent widespread transmission of scabies on the body.
Scabies on the body Symptoms Pictures
Recognizing scabies on the body symptoms pictures is paramount for effective diagnosis and treatment of this highly contagious parasitic skin infestation. The symptoms are primarily caused by the female scabies mite burrowing into the top layer of the skin to lay eggs, triggering an allergic reaction in the host. The most defining symptom is an intensely itchy rash that tends to worsen at night, often disrupting sleep. This persistent pruritus is not merely a nuisance but a hallmark sign that prompts individuals to seek medical attention for their scabies on the body.
Key Scabies on the Body Symptoms for Identification:
- Intense Pruritus (Itching): This is the most common and distressing symptom of scabies on the body. The itching is typically severe and generalized, though often more pronounced in certain areas. It frequently intensifies during the night, when the skin is warm, likely due to increased mite activity or the body’s heightened sensitivity. The unrelenting itch leads to significant discomfort, sleep deprivation, and reduced quality of life, making it a critical indicator in scabies on the body symptoms pictures.
- Scabies Burrows: These are tiny, irregular, raised, grayish-white or flesh-colored lines on the skin surface, typically a few millimeters to a centimeter long. These distinct tunnels are created by the female mite as it excavates its way through the stratum corneum. While pathognomonic for scabies, these burrows can be challenging to identify, especially in individuals with extensive excoriations or thick skin. Common sites for finding burrows include the web spaces between the fingers, wrists, elbows, armpits, navel, areolae (especially in women), and external genitalia. In infants, burrows may be found on the palms and soles. Visualizing these burrows is a definitive diagnostic clue often highlighted in scabies on the body pictures.
- Papules: Small, red, raised bumps are a frequent manifestation of scabies on the body. These papules often appear in clusters and can be found widely distributed across the body, though they prefer warmer, protected areas. They are a direct result of the immune response to mite antigens, feces, and eggs within the skin. These lesions are highly itchy and contribute significantly to the overall rash presentation in scabies on the body symptoms pictures.
- Vesicles: Small, fluid-filled blisters can accompany the papules, particularly in children or those with a heightened allergic reaction. These vesicles are usually clear or yellowish and indicate a more inflammatory response to the mite infestation. Their presence can sometimes make diagnosis challenging as they might resemble other dermatological conditions, but their specific distribution pattern with other scabies symptoms is key.
- Nodules: Scabies nodules are firm, reddish-brown, intensely itchy lumps, typically 5-10 mm in diameter. They often persist for weeks or even months after successful eradication of the mites, representing a persistent immunological reaction. Common locations for these nodules include the groin, buttocks, armpits, and genitals. Nodular scabies is a less common but distinctive presentation, frequently seen in children or those with delayed diagnosis.
- Excoriations: Due to the severe itching, patients with scabies on the body inevitably scratch the affected areas. This scratching leads to skin abrasions, linear scratch marks, and superficial erosions known as excoriations. These excoriations can sometimes obscure primary scabies lesions and make the identification of burrows more difficult. They are a common feature in most scabies on the body pictures illustrating active infestation.
- Crusting and Scaling: In severe forms, particularly crusted scabies (also known as Norwegian scabies), the skin can become thick, scaly, and crusted. This hyperkeratotic presentation results from an overwhelming mite burden, sometimes thousands to millions of mites, due to an impaired immune response. Crusted scabies lesions are highly contagious and represent a significant public health concern, often featuring extensive skin thickening and deep fissures in scabies on the body symptoms pictures.
- Secondary Bacterial Infections: Constant scratching can break the skin barrier, creating entry points for bacteria, most commonly Staphylococcus aureus and Streptococcus pyogenes. This can lead to secondary bacterial infections such as impetigo (honey-colored crusts), cellulitis (red, swollen, painful skin), or even more severe systemic infections. These secondary infections often complicate the clinical picture and require additional antibiotic treatment.
The distribution of scabies on the body symptoms is often symmetrical and tends to spare the head and neck in adults, except in cases of crusted scabies or in infants and immunocompromised individuals. Understanding these specific manifestations helps healthcare providers and individuals alike to accurately interpret scabies on the body symptoms pictures and pursue timely intervention. Awareness of these visual cues is crucial for containing outbreaks and preventing chronic suffering from scabies on the body.
Signs of Scabies on the body Pictures
The clinical presentation of scabies on the body is characterized by a specific set of signs that, when observed, strongly indicate an active infestation. These signs are often the focus of diagnostic investigation and are crucial for interpreting signs of scabies on the body pictures. While itching is the patient’s primary complaint, the objective signs reveal the underlying parasitic activity and the body’s reaction to it. Early and accurate identification of these signs can lead to prompt treatment, thereby minimizing discomfort and preventing further spread of scabies.
Observable Signs of Scabies on the Body:
- Characteristic Scabies Burrows: As previously mentioned, burrows are pathognomonic for scabies. These fine, wavy, thread-like lines, measuring 2-15 mm in length, appear slightly raised and are often lighter or darker than the surrounding skin. At one end of the burrow, a small dark speck may be visible, which is the mite itself. Locations include:
- Web spaces of fingers: A classic site, often showing delicate, linear tracks.
- Flexor aspects of wrists: Burrows and small papules are commonly found here.
- Elbows: Especially on the olecranon process.
- Armpits (axillae): Often sites of intense itching and papule formation.
- Belt line and navel: Areas subject to pressure and warmth.
- Nipples and areolae (women): Highly susceptible areas, often presenting with papules and itching.
- Genitalia (men): Scrotum and penis often show highly inflamed papules or nodules.
- Buttocks: Frequently affected, particularly in sedentary individuals.
- Knees: Less common but can present with papules.
- Soles of feet and palms of hands (infants/young children): In adults, these areas are typically spared unless crusted scabies is present.
The ability to visualize these burrows, sometimes enhanced with dermoscopy or ink tests, is a definitive diagnostic skill when examining scabies on the body pictures.
- Erythematous Papules: These small (1-3 mm), red, solid bumps are the most common visible lesion in scabies on the body. They represent an inflammatory reaction to the mite and its products. Their distribution is key, often found in the aforementioned classic sites, but also frequently on the torso, inner thighs, and around the waist. These papules are intensely itchy and often appear in clusters or in a scattered pattern.
- Vesicles and Pustules: Small blisters (vesicles) or pus-filled bumps (pustules) can be present, especially in individuals with sensitive skin or those developing secondary bacterial infections. Vesicles are more common in children. Pustules signal bacterial superinfection, often manifesting with signs of inflammation like redness and warmth around the lesion.
- Nodular Scabies: This distinct presentation involves reddish-brown, firm, pea-sized nodules, typically found in the axillae, groin, buttocks, and scrotum. These are granulomatous reactions to retained mite antigens, persisting for extended periods even after successful treatment. They can be intensely itchy and are a significant diagnostic sign for chronic or persistent scabies, making their appearance in scabies on the body pictures quite recognizable.
- Excoriations and Crusting: The persistent scratching (excoriations) can lead to linear lesions, punctate erosions, and even secondary skin infections. In cases of crusted scabies, extensive areas of thick, hyperkeratotic crusting with fissures and scales will be observed, particularly on the hands, feet, elbows, and buttocks. This severe presentation, characterized by a high mite load, is highly contagious and distinctive in signs of scabies on the body pictures.
- Distribution Pattern: A crucial diagnostic sign is the specific distribution of lesions. While the exact pattern can vary, scabies on the body typically affects:
- Interdigital spaces of hands
- Flexor surfaces of wrists and elbows
- Anterior axillary folds
- Areolae in females
- Umbilicus
- Lower buttocks and inner thighs
- External genitalia in males (scrotum, penis)
- Hands and feet (especially palms and soles in infants/immunocompromised)
- Waistline
The head and neck are generally spared in immunocompetent adults. This classic pattern helps distinguish scabies from other pruritic dermatoses.
- Presence of Mites, Eggs, or Fecal Matter (Scabies Mite Faeces): Microscopic examination of skin scrapings from suspicious lesions (especially burrows) can reveal the mites, eggs, or fecal pellets (scybala). This is the definitive diagnostic method and is often implied when discussing the objective signs visible in scabies on the body pictures, though the mites themselves are rarely visible to the naked eye.
Understanding these comprehensive signs facilitates accurate diagnosis and treatment planning for individuals suffering from scabies on the body. Healthcare professionals rely on a combination of patient history, clinical examination, and sometimes confirmatory tests to establish a diagnosis, effectively leveraging the visual information provided by typical signs of scabies on the body pictures.
Early Scabies on the body Photos
Identifying early scabies on the body photos is often challenging due to the initial mildness and non-specific nature of symptoms. The incubation period for scabies varies; for a first-time infestation, symptoms may not appear for two to six weeks after exposure, as it takes time for the body to develop an allergic reaction to the mites, their eggs, and their fecal matter. However, in re-infestations, symptoms can emerge much faster, within one to four days, due to pre-existing sensitization. Recognizing these subtle initial signs is critical for prompt intervention and preventing the spread of scabies on the body.
Characteristics of Early Scabies on the Body:
- Mild Itching: In the very early stages of a primary infestation, the itching associated with scabies on the body might be intermittent and less severe than in established cases. It may be easily dismissed as general skin irritation or dryness. However, it often begins to show a pattern of worsening at night or after a hot bath or shower, which should raise suspicion. This initial mild pruritus is a key early indicator, though it rarely appears distinctly in early scabies on the body photos.
- Faint or Sparse Burrows: The hallmark scabies burrows may be present, but they are often very short, few in number, and difficult to spot in the early phase. They might be only a few millimeters long and less inflamed. Careful inspection of classic sites like the finger webs, wrists, and elbows is necessary to detect these subtle initial tracks. In early scabies on the body photos, these burrows can be elusive and might require magnification to be clearly visible.
- Small, Scattered Red Bumps (Papules): The initial rash often manifests as isolated, small, red papules (pimples or bumps). These may be mistaken for insect bites, folliculitis, or other minor skin irritations. They are not yet widespread and may not be intensely inflamed. These small, non-specific lesions can be easily overlooked, making precise identification challenging, even for experienced eyes reviewing early scabies on the body photos.
- Absence of Widespread Excoriations: Because the itching is not yet at its peak intensity, there will typically be fewer or no excoriations (scratch marks) in the earliest stages. The skin might appear relatively intact, apart from the small, primary lesions. This absence of extensive damage differentiates early scabies from more established infestations.
- Localized Presentation: Early scabies on the body tends to be more localized to the point of initial contact or preferred mite sites before spreading. Common early areas include:
- Between the fingers
- Wrists
- Elbows
- Around the navel
- Ankles
- Genitalia
The spread to other parts of the body typically occurs as the mite population increases and the host’s immune response develops.
- No Significant Crusting or Vesiculation: Crusting, severe scaling, or widespread blistering is highly unlikely in the early stages of a typical scabies infestation. These more severe manifestations are indicative of a prolonged or complicated course of scabies on the body, such as crusted scabies.
- Symptom Progression Over Time: A key aspect of early scabies is the progression of symptoms. What starts as mild, intermittent itching and a few scattered bumps will, over weeks, evolve into intense, nocturnal pruritus and a more widespread, polymorphous rash. This evolution helps confirm the diagnosis if initial symptoms were ambiguous. Understanding this timeline is crucial for interpreting what might be seen in sequential early scabies on the body photos.
Due to the often subtle nature of initial symptoms, suspicion of early scabies on the body is often raised by a history of recent exposure to an infested individual or close contact, especially within a household or institutional setting. Healthcare providers use a combination of patient history, detailed physical examination, and sometimes dermoscopy or skin scrapings to confirm the diagnosis, particularly when faced with ambiguous early scabies on the body photos. Timely diagnosis and treatment are essential to prevent the infestation from becoming more widespread and to alleviate the considerable discomfort caused by scabies on the body.
Skin rash Scabies on the body Images
The skin rash associated with scabies on the body is one of the most visible and diagnostic features of the infestation, though its appearance can be highly variable. The rash is a result of an allergic reaction to the presence of the mites, their eggs, and their fecal matter within the skin. It is typically polymorphous, meaning it can present with a variety of lesion types, making its interpretation in skin rash scabies on the body images a nuanced process. Understanding the characteristics and distribution of this rash is crucial for accurate diagnosis and differentiating scabies from other pruritic skin conditions.
Characteristics of the Scabies Skin Rash:
- Polymorphous Nature: The rash is not uniform and can include various primary and secondary lesions, such as:
- Papules: Small, red, raised bumps are the most common component of the scabies rash. They can be discrete or confluent, appearing widely across affected areas.
- Vesicles: Tiny, clear, fluid-filled blisters, often seen alongside papules, particularly in children or individuals with highly reactive skin.
- Pustules: Small, pus-filled lesions, usually indicative of secondary bacterial infection due to scratching.
- Nodules: Firm, reddish-brown, intensely itchy lumps, especially in chronic cases or specific locations like the groin and axillae.
- Burrows: While distinct from the general rash, these minute, linear tracks are often interspersed within the rash and are a definitive sign.
This varied presentation makes comprehensive evaluation of skin rash scabies on the body images essential for diagnosis.
- Intense Pruritus: The rash is invariably accompanied by severe itching, which is typically worse at night and with warmth. This unrelenting itch leads to significant patient distress and often influences the appearance of the rash through scratching.
- Excoriations: Scratching due to the severe itch results in linear scratch marks, erosions, and sometimes weeping or crusting, which are prominent features in most skin rash scabies on the body images. These secondary lesions can sometimes obscure the primary scabies lesions.
- Distribution Pattern: The scabies rash has a characteristic distribution that helps distinguish it from other conditions. Common areas affected include:
- Interdigital webs of hands: Often the first and most common site.
- Flexor aspects of wrists and elbows: Inner wrist and elbow creases.
- Axillae (armpits): Especially the anterior folds.
- Periumbilical region: Around the navel.
- Waistline: Where clothing is tight or rubs against the skin.
- Areolae (nipples) in women.
- Genitalia: Scrotum and penis in men, labia in women.
- Buttocks.
- Lower back.
- Inner thighs.
- Soles of feet and palms of hands in infants and immunocompromised individuals.
The head and neck are typically spared in immunocompetent adults. This specific topographical distribution is a vital clue when examining skin rash scabies on the body images.
- Crusted Scabies Rash (Norwegian Scabies): This severe form presents with an atypical, widespread, hyperkeratotic rash that can resemble psoriasis or eczema. The skin becomes thick, crusted, scaly, and often fissured, particularly on the hands, feet, elbows, and buttocks. This form harbors an enormous mite burden and is highly contagious, exhibiting a dramatically different appearance in skin rash scabies on the body images compared to typical scabies. The itching may be less pronounced in some immunocompromised individuals with crusted scabies.
- Secondary Skin Changes: Chronic scratching and inflammation can lead to lichenification (thickening of the skin with exaggerated skin markings) in affected areas. Pigmentary changes, such as post-inflammatory hyperpigmentation or hypopigmentation, can also occur, particularly in individuals with darker skin tones, further complicating the interpretation of skin rash scabies on the body images.
The appearance of the scabies rash on the body can be influenced by several factors, including the patient’s immune status, hygiene practices, and the duration of the infestation. Because the rash can mimic many other dermatological conditions, a thorough clinical history, physical examination, and sometimes confirmatory tests (such as skin scrapings) are essential for accurate diagnosis. Examining high-quality skin rash scabies on the body images can serve as an invaluable educational tool for recognizing the diverse manifestations of this persistent and highly contagious skin disease.
Scabies on the body Treatment
Effective scabies on the body treatment is crucial not only to relieve the distressing symptoms but also to prevent further spread of the infestation to close contacts and within communities. Treatment typically involves topical scabicides or, in certain circumstances, oral medications. It’s imperative that treatment is administered to the infested individual and all close contacts, even if they are asymptomatic, to break the cycle of transmission. Environmental measures also play a significant role in successful eradication of scabies on the body.
Comprehensive Scabies on the Body Treatment Strategies:
- Topical Scabicides: These are the first-line treatments for typical scabies on the body.
- Permethrin Cream 5%: This is the most commonly prescribed and highly effective topical treatment. It is considered safe for most individuals, including children over 2 months of age and pregnant women.
- Application: The cream should be applied to all skin surfaces from the neck down to the soles of the feet. In infants, young children, and immunocompromised individuals, it should also be applied to the scalp, face, and ears.
- Duration: It is typically left on for 8-14 hours (usually overnight) and then thoroughly washed off.
- Repeat Treatment: A second application is generally recommended 7-14 days after the first to kill any newly hatched mites, as the first application may not kill eggs.
- Crotamiton Cream 10% or Lotion: Less effective than permethrin but can be an alternative, especially if permethrin is contraindicated.
- Application: Applied daily for 3-5 days.
- Duration: Left on for 24 hours between applications.
- Lindane Lotion 1%: While effective, its use is restricted due to potential neurotoxicity, particularly in children, pregnant women, the elderly, and individuals with extensive skin excoriations. It is generally reserved for cases unresponsive to other treatments.
- Sulfur Ointment (5-10%): An older but effective treatment, especially for infants and pregnant women where permethrin might be a concern. It has a strong odor and can be messy.
- Application: Applied nightly for 3-7 nights.
- Benzyl Benzoate Lotion 25%: Used in some regions, but can be irritating and should be avoided in young children.
- Permethrin Cream 5%: This is the most commonly prescribed and highly effective topical treatment. It is considered safe for most individuals, including children over 2 months of age and pregnant women.
- Oral Medications: Used for severe cases, crusted scabies, or when topical treatments are impractical or ineffective.
- Ivermectin: An oral antiparasitic drug.
- Dosage: Typically given as a single dose of 200 micrograms per kilogram of body weight.
- Repeat Treatment: A second dose 7-14 days later is usually recommended to ensure complete eradication, especially for crusted scabies.
- Usage: Particularly useful for crusted scabies, large-scale outbreaks in institutions, or in individuals unable to apply topical treatments effectively. It is generally not recommended for pregnant women, breastfeeding mothers, or children weighing less than 15 kg.
- Ivermectin: An oral antiparasitic drug.
- Treatment of Household Contacts and Close Contacts: This is a critical component of scabies on the body treatment. All household members and other close contacts (e.g., sexual partners) should be treated simultaneously, even if they show no symptoms. This prevents re-infestation and controls outbreaks. Failure to treat contacts is a common reason for treatment failure and recurrent infestations.
- Management of Symptoms Post-Treatment:
- Post-Scabies Itch: Itching and rash can persist for up to 2-4 weeks after successful eradication of mites, as it takes time for the body’s immune reaction to subside and for dead mites/eggs to be cleared from the skin. This is not necessarily a sign of treatment failure.
- Relief Measures: Oral antihistamines can help reduce itching. Topical corticosteroids (e.g., hydrocortisone cream) can be applied to soothe inflamed skin and reduce post-scabies pruritus and rash.
- Moisturizers: Emollients can help restore the skin barrier, which may have been disrupted by scratching and the infestation itself.
- Environmental Decontamination: While mites typically cannot survive long off the human body (usually 2-3 days), taking certain steps can help minimize risk, especially in cases of crusted scabies where mite load is exceptionally high.
- Laundry: Wash all clothing, bedding, and towels used by the infested person and contacts during the 3 days prior to treatment. Use hot water (at least 122°F or 50°C) and machine dry on a hot cycle.
- Items that cannot be washed: Items that cannot be washed can be dry-cleaned or sealed in plastic bags for at least 72 hours (3 days) to starve the mites.
- Vacuuming: Vacuum carpets and upholstered furniture, and dispose of the vacuum bag immediately after use.
- No need for fumigation: Extensive house cleaning or fumigation is generally not necessary for typical scabies infestations.
- Addressing Secondary Bacterial Infections: If secondary bacterial infections (e.g., impetigo, cellulitis) are present due to scratching, oral or topical antibiotics may be required in addition to the scabies treatment.
- Follow-up: A follow-up visit with a healthcare provider is often recommended within a few weeks to assess treatment success and address any persistent symptoms or concerns regarding scabies on the body.
Adherence to treatment protocols, comprehensive treatment of all contacts, and proper environmental hygiene are essential for successful eradication of scabies on the body and preventing recurrence. Prompt recognition of scabies on the body symptoms pictures facilitates this crucial process, leading to better patient outcomes and public health management.