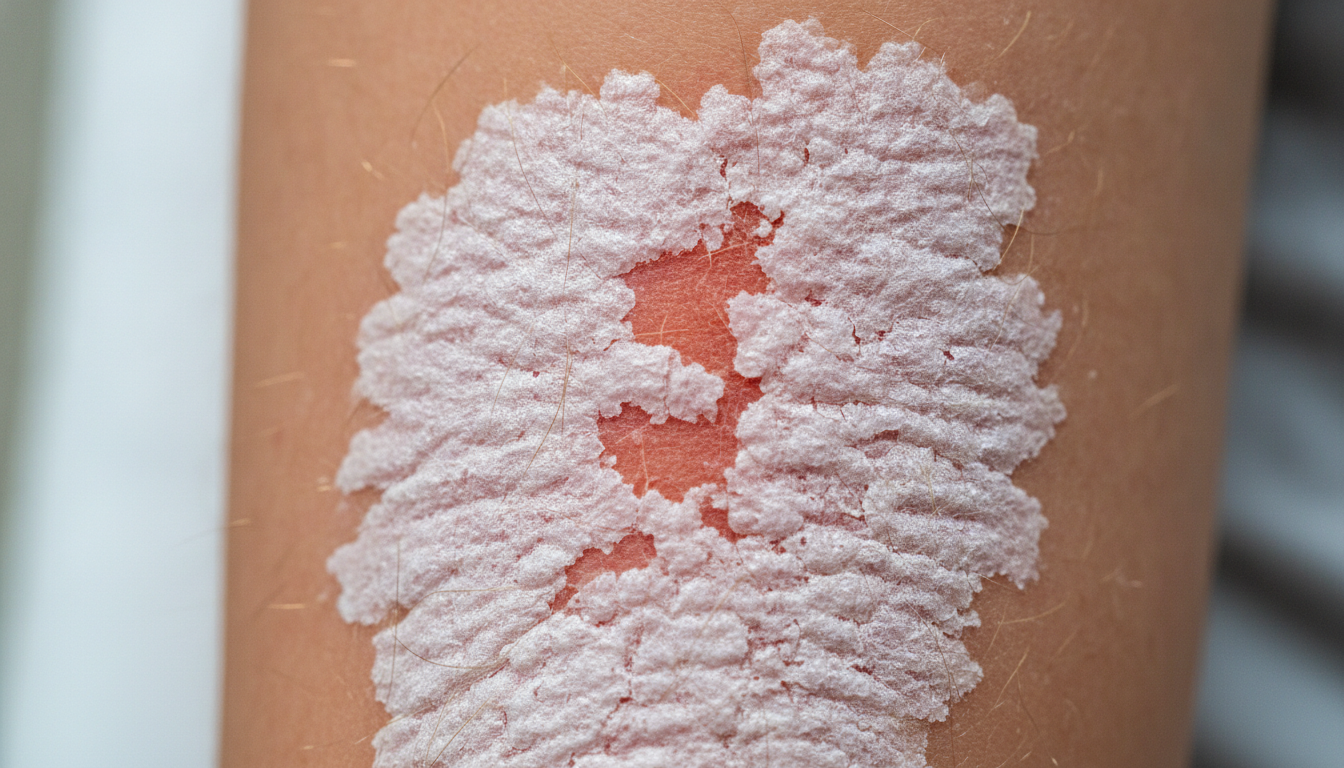
Recognizing Psoriasis on the elbows symptoms pictures is crucial for timely diagnosis and effective management of this chronic skin condition. This article provides an in-depth visual and descriptive guide to help individuals and healthcare professionals understand the specific manifestations of psoriasis affecting the elbow regions. By examining detailed descriptions of lesions, early signs, and various presentations, we aim to enhance understanding of elbow psoriasis.
Psoriasis on the elbows Symptoms Pictures
Understanding the characteristic appearance of psoriasis on the elbows symptoms pictures is paramount for identification. Psoriasis, particularly plaque psoriasis, frequently targets extensor surfaces such as the elbows, presenting with distinct and often uncomfortable symptoms. These symptoms typically manifest as well-demarcated patches of inflamed skin, which are usually raised and have a thickened, scaly surface. The severity and specific characteristics can vary significantly among individuals, influencing the overall visual presentation of elbow psoriasis.
The primary symptom observed in elbow psoriasis images is the presence of erythematous (red) plaques. These lesions are almost invariably covered by silvery-white scales, which are layers of dead skin cells that accumulate due to an accelerated skin cell turnover rate. The scales can range from fine and loosely adherent to thick, tenacious, and tightly bound to the underlying skin. When these scales are scratched or picked off, pinpoint bleeding may occur, a phenomenon known as the Auspitz sign, although this is more of a diagnostic sign than a primary symptom.
Common symptomatic features of psoriasis on the elbows include:
- Erythema: Profound redness of the affected skin, often appearing as patches with a vivid red or salmon-pink hue. This redness is a result of increased blood flow to the inflamed area. In individuals with darker skin tones, the redness might appear purplish or brownish, and post-inflammatory hyperpigmentation can be more pronounced after resolution.
- Scaling: The hallmark silvery-white or greyish scales that are dry and flaky. These scales are formed from an overproduction of skin cells and can be shed easily, leading to a constant dusting of skin flakes. The thickness of the scales can vary from a thin, almost invisible film to thick, crusted layers that can be quite noticeable.
- Thickness/Elevation: The affected skin patches are typically raised above the surrounding healthy skin, forming distinct plaques. This elevation is due to both the accumulation of scales and the thickening of the underlying epidermal and dermal layers. The plaques can feel firm or leathery to the touch.
- Itching (Pruritus): A significant and often debilitating symptom, itching can range from mild irritation to severe, persistent pruritus that interferes with daily activities and sleep. Constant scratching can exacerbate the condition, leading to skin breakdown, infection, and further thickening of the plaques (lichenification).
- Dryness and Cracking: The skin within the psoriatic plaques is often extremely dry, especially at the edges or within deep fissures that may develop, particularly if the skin is stretched or subjected to friction. Cracking can be painful and may lead to bleeding and increased risk of infection.
- Pain: While itching is more common, pain can occur, especially if the plaques are severely inflamed, cracked, or located in areas subject to frequent movement and friction, such as the elbows. The stretching of dry, thickened skin can be acutely painful.
- Well-Demarcated Borders: The plaques usually have clear, distinct borders that separate them sharply from the surrounding healthy skin. This characteristic helps differentiate psoriasis from other skin conditions that might have more diffuse or irregular margins.
- Symmetry: Psoriasis on the elbows often presents symmetrically, affecting both elbows, though one side might be more severely affected than the other. This symmetrical distribution is a common pattern for chronic plaque psoriasis.
When examining psoriasis on the elbows pictures, it’s vital to note the distinct coloration and texture. The vibrant redness beneath the scales, the sharp demarcation, and the typical location on the outer aspects of the elbows are key identifiers. These areas are prone to trauma and friction, which can act as a trigger for psoriasis development or flare-ups, a phenomenon known as the Koebner phenomenon or isomorphic response. The presence of these combined symptoms provides a strong indication of an elbow psoriasis flare-up, necessitating medical evaluation for proper diagnosis and management of the chronic condition.
Signs of Psoriasis on the elbows Pictures
While symptoms are what a patient feels and observes, signs are objective indicators a clinician looks for when diagnosing psoriasis on the elbows. The clinical signs are crucial for confirming a diagnosis and distinguishing psoriasis from other dermatological conditions. When viewing signs of psoriasis on the elbows pictures, a trained eye can identify several key dermatological features that are highly suggestive of psoriasis. These signs help solidify the diagnosis and guide treatment strategies for affected individuals with psoriasis on the elbow skin.
Key clinical signs visible in psoriasis on the elbows pictures include:
- Erythematous Plaques with Silvery Scales: As detailed in symptoms, the visible manifestation of these red, raised patches covered with silvery scales is the most definitive sign. The scales are often described as micaceous or lamellar, meaning they resemble mica or are arranged in thin layers. The uniform appearance across the lesion, especially on the elbow, is a strong indicator.
- Auspitz Sign: This sign is elicited when the silvery scales are gently scraped away, revealing pinpoint bleeding from dilated capillaries in the dermal papillae. This phenomenon is highly characteristic of psoriasis, although not exclusive to it. It indicates an underlying vascular abnormality and thinned epidermis.
- Koebner Phenomenon (Isomorphic Response): This is the appearance of new psoriatic lesions at sites of skin trauma, scratching, or injury. On the elbows, repetitive friction, scratching, or minor abrasions can trigger new plaques to form within previously unaffected skin areas. This sign is observed over time rather than instantaneously but is a significant diagnostic clue.
- Oil Spot or Salmon Patch Nails: While not directly on the elbow, nail changes are common comorbidities of psoriasis and can indirectly support an elbow psoriasis diagnosis. These include pitting (small depressions in the nail plate), onycholysis (separation of the nail from the nail bed), subungual hyperkeratosis (thickening of the skin under the nail), and discoloration, particularly the characteristic “oil drop” or “salmon patch” sign beneath the nail plate.
- Plaque Distribution and Symmetry: Psoriasis often affects extensor surfaces symmetrically. Observing similar plaques on both elbows, knees, lower back, and scalp strengthens the diagnosis. The precise location on the outer, prominent part of the elbow joint is highly typical for chronic plaque psoriasis.
- Histopathological Features (Biopsy): Although not a visual sign on the skin’s surface, a skin biopsy can reveal microscopic features that are definitive for psoriasis. These include acanthosis (epidermal hyperplasia), parakeratosis (retention of nuclei in the stratum corneum), elongated rete ridges, dilation of blood vessels in the dermal papillae, and inflammatory cell infiltrates (e.g., Munro microabscesses). This is typically used in atypical or recalcitrant cases.
- Evidence of Lichenification: In chronic, long-standing plaques, especially those subjected to persistent scratching, the skin can become thickened and leathery with exaggerated skin lines. This is a secondary change but a sign of chronic inflammation and scratching, often seen in psoriasis on the elbows.
- Plaque Margins: The sharp, distinct borders of psoriatic plaques, often with a subtle peripheral halo of redness, are a consistent sign. The clarity of these margins differentiates them from other conditions with more indistinct borders.
The combination of these signs, particularly the characteristic plaques with silvery scales, Auspitz sign, and typical distribution, makes the diagnosis of psoriasis on the elbows quite straightforward for experienced dermatologists. Careful examination of psoriasis elbow pictures helps in identifying these subtle yet critical diagnostic cues. Understanding these signs is not only for diagnosis but also for monitoring the disease progression and response to various elbow psoriasis treatments. Prompt recognition based on these visual signs can lead to earlier intervention and better disease management, improving the quality of life for individuals with psoriasis skin rash on elbows.
Early Psoriasis on the elbows Photos
Identifying early psoriasis on the elbows photos can be challenging but is crucial for prompt intervention and potentially slowing disease progression. Unlike fully developed plaques, early lesions may be subtle, making them easier to overlook or misdiagnose as other common skin irritations. The initial presentation of elbow psoriasis often starts much smaller and less pronounced than the well-known chronic plaques. Recognizing these nascent signs is vital for individuals who suspect they might be developing psoriasis on their elbows.
The characteristics of early psoriasis on the elbows typically include:
- Small, Red Papules: Psoriasis often begins as small, red, elevated bumps (papules). These initial lesions may be only a few millimeters in diameter and might not immediately display the classic thick, silvery scales. They may appear as simple red spots on the skin.
- Fine Scaling: While thick scales are characteristic of established psoriasis, early lesions may present with only very fine, thin, and often translucent scales. These scales might be barely noticeable and less adherent than those seen in chronic plaques. They may appear as a slight flakiness on the surface of the red papules.
- Slight Itching or Mild Irritation: Early psoriatic lesions on the elbows might cause a mild itchy sensation or a feeling of slight irritation, rather than the intense pruritus associated with more advanced disease. This can often be mistaken for dry skin or a minor allergic reaction.
- Localized Redness: The initial redness might be localized to very small areas, often round or oval in shape. The vivid, widespread erythema of mature plaques is typically absent in the earliest stages. The color might be a lighter pink compared to the deeper red of established lesions.
- Slow Growth: These early papules tend to grow slowly, gradually expanding in size and developing more pronounced features over weeks to months. They may coalesce with adjacent papules to form larger plaques. This slow progression can sometimes delay recognition.
- Triggered Appearance: Sometimes, early lesions can appear following a specific trigger, such as a localized injury (Koebner phenomenon), a period of stress, or an infection. Observing a new red patch develop after a scratch or bump on the elbow can be a clue to early onset elbow psoriasis.
- Absence of Clear Demarcation: In very early stages, the borders of the lesions might not be as sharply defined as in chronic plaques. They may blend more subtly into the surrounding healthy skin before becoming distinctly elevated and well-demarcated.
- Asymmetry (Initially): While chronic psoriasis often presents symmetrically, early lesions might initially appear on one elbow before affecting the other. However, it’s common for both elbows to eventually develop lesions.
It is important to differentiate early psoriasis on the elbows from other common skin conditions that can appear similar. These include contact dermatitis, eczema (atopic dermatitis), fungal infections (tinea corporis), and sometimes even dry skin patches. For instance, eczema lesions tend to be less well-demarcated, more intensely itchy, and often have a weeping or crusting appearance, whereas fungal infections typically have an advancing, raised border with central clearing.
If individuals notice persistent red, slightly scaly patches on their elbows, even if they are small and seemingly benign, it is advisable to consult a dermatologist. Early diagnosis of psoriasis on the elbows allows for the initiation of targeted elbow psoriasis treatment strategies that can help manage the condition more effectively and potentially prevent the development of widespread or more severe plaques. Examining beginning psoriasis elbows images can aid in this early recognition, empowering individuals to seek professional medical advice without delay.
Skin rash Psoriasis on the elbows Images
The term “skin rash psoriasis on the elbows images” effectively captures the visual appearance of psoriatic lesions, which are indeed a type of inflammatory skin rash. On the elbows, this rash is highly characteristic and often serves as a classic presentation of chronic plaque psoriasis. Understanding the nuances of this specific rash helps in differentiating it from other dermatological conditions and appreciating the impact of the disease on the skin. The appearance of the psoriasis rash on the elbows can vary in intensity and extent, from small, isolated patches to large, confluent areas covering the entire extensor surface of the joint.
Detailed characteristics of the psoriasis skin rash on the elbows:
- Classic Plaque Morphology: The most common form of psoriasis on the elbows is plaque psoriasis, characterized by well-defined, raised, red patches (plaques) covered with silvery-white scales. These plaques can vary in size from small, coin-sized lesions to larger patches several centimeters in diameter. The texture is often rough and dry.
- Coloration: The underlying skin of the rash is typically erythematous, ranging from a vibrant salmon-pink to a deep red. In individuals with darker skin tones, the rash might present with purplish, violaceous, or hyperpigmented hues, making the redness less obvious but still distinct from the surrounding skin. Post-inflammatory hyperpigmentation is also common in skin of color after active lesions subside.
- Scale Characteristics: The scales are key to identifying the psoriasis elbow rash. They are typically dry, silvery, and stratified, meaning they form in layers. When scratched, these scales can detach easily, creating a “snowstorm” effect. The thickness of the scales correlates with the activity and chronicity of the lesion. They adhere tightly in the center of the plaque but can be looser at the edges.
- Border Definition: A striking feature of the elbow psoriasis rash is its sharply demarcated borders. The edges of the rash are usually distinct and elevated, clearly separating the affected skin from healthy skin. This clear border helps distinguish it from more diffuse rashes like eczema.
- Potential for Fissuring: Due to extreme dryness and the constant movement of the elbow joint, the rash can develop painful cracks or fissures within the plaques, especially if the skin is thick and inflexible. These fissures can bleed and increase the risk of secondary bacterial infections.
- Sensation of the Rash: Beyond the visual aspect, the rash often causes significant itching (pruritus), which can range from mild to severe. Some individuals also report a burning sensation or discomfort, particularly when the skin is very dry or cracked.
- Response to Trauma (Koebner Phenomenon): New lesions of the psoriasis skin rash can develop at sites of skin injury, such as scratches, cuts, or sunburn. This response is common for psoriatic rashes and highlights the sensitivity of psoriatic skin to physical trauma.
- Variants of Psoriatic Rash on Elbows: While plaque psoriasis is dominant, other forms can occasionally involve the elbows, though less commonly as primary sites:
- Guttate Psoriasis: Appears as small, drop-like, red, scaly spots. While often widespread on the trunk and limbs, these small lesions can appear on the elbows, especially after a streptococcal infection.
- Inverse Psoriasis (Intertriginous Psoriasis): This form affects skin folds. While rare on the outer elbow, it can affect the inner crease of the elbow (ante-cubital fossa) in some cases, appearing as smooth, red, shiny lesions without typical scales due to moisture in the area.
- Pustular Psoriasis: Characterized by sterile pus-filled blisters (pustules) on red, inflamed skin. Localized pustular psoriasis can occur on the palms and soles, but generalized pustular psoriasis can affect any skin surface, including the elbows, though it is a severe and rare variant.
Observing skin rash psoriasis on the elbows images provides a clear visual representation of this chronic inflammatory condition. The consistency of the rash’s appearance across different individuals, with the classic red plaques and silvery scales, makes it a recognizable dermatological entity. Understanding these visual cues is essential for both self-assessment and medical diagnosis, prompting appropriate investigation and management strategies for this persistent and often uncomfortable elbow skin rash. Early and accurate identification is key to mitigating the impact of the rash and improving patient outcomes for psoriatic elbow lesions.
Psoriasis on the elbows Treatment
Treating psoriasis on the elbows involves a multi-faceted approach aimed at reducing inflammation, slowing skin cell turnover, alleviating symptoms, and improving the patient’s quality of life. The choice of elbow psoriasis treatment depends on several factors, including the severity and extent of the condition, the presence of associated psoriatic arthritis, patient preferences, and response to previous therapies. Effective management of psoriatic lesions on the elbows often requires a combination of topical, light-based, and systemic treatments. This section outlines comprehensive treatment options for psoriasis on the elbows.
I. Topical Treatments for Psoriasis on the Elbows:
These are often the first line of defense for mild to moderate elbow psoriasis, applied directly to the affected skin.
- Corticosteroids:
- Mechanism: Reduce inflammation and suppress immune activity.
- Types: Available in various potencies (low, medium, high, very high). High-potency corticosteroids (e.g., clobetasol propionate, halobetasol propionate) are frequently used for thick plaques on the elbows due to the skin’s thickness and resilience in this area.
- Application: Typically applied once or twice daily for a limited duration to avoid side effects.
- Side Effects: Skin thinning (atrophy), striae (stretch marks), telangiectasias (spider veins), and hypopigmentation with prolonged use. Pulsed therapy (intermittent use) is often recommended.
- Vitamin D Analogues:
- Mechanism: Slow down the overgrowth of skin cells and reduce inflammation.
- Examples: Calcipotriene (calcipotriol), calcitriol.
- Application: Usually applied once or twice daily. Can be used alone or in combination with topical corticosteroids for enhanced efficacy and reduced side effects.
- Side Effects: Skin irritation, burning, stinging. Less risk of skin atrophy compared to corticosteroids.
- Topical Retinoids:
- Mechanism: Normalize skin cell growth and reduce inflammation.
- Example: Tazarotene.
- Application: Applied once daily. Often effective for thick plaques but can cause significant irritation.
- Side Effects: Irritation, redness, photosensitivity. Not recommended during pregnancy.
- Coal Tar:
- Mechanism: Reduces scaling, itching, and inflammation.
- Forms: Available in creams, ointments, shampoos, and bath solutions.
- Application: Applied daily. Can be messy and has a strong odor.
- Side Effects: Skin irritation, folliculitis, photosensitivity. Can stain clothing and bedding.
- Anthralin:
- Mechanism: Reduces skin cell proliferation and normalizes skin cell growth.
- Application: Applied in short-contact therapy (10-30 minutes) due to its irritant nature and staining properties.
- Side Effects: Significant skin irritation, staining of skin, hair, and clothing. Requires careful application.
- Calcineurin Inhibitors:
- Mechanism: Suppress immune responses in the skin, reducing inflammation and redness.
- Examples: Tacrolimus ointment, pimecrolimus cream.
- Application: Used off-label for psoriasis, particularly in sensitive areas or for individuals who cannot tolerate corticosteroids.
- Side Effects: Burning, itching at the application site. No risk of skin atrophy.
- Salicylic Acid:
- Mechanism: Keratolytic agent that helps remove scales and soften plaques, allowing other topical medications to penetrate better.
- Application: Often used in combination with other topical treatments or as a standalone preparation for descaling.
- Side Effects: Skin irritation.
II. Phototherapy (Light Therapy) for Psoriasis on the Elbows:
Utilizes specific wavelengths of ultraviolet light to slow skin cell growth and reduce inflammation. Effective for widespread or recalcitrant elbow psoriasis.
- Narrowband UVB (NB-UVB):
- Mechanism: Emits a specific range of UVB light (311-312 nm) that is highly effective for psoriasis.
- Application: Administered in a doctor’s office or specialized clinic, typically 2-3 times per week. Home units are also available for suitable candidates.
- Side Effects: Sunburn-like reactions, increased risk of skin cancer with long-term cumulative exposure.
- Excimer Laser:
- Mechanism: Delivers high-dose monochromatic UVB light directly to localized plaques, sparing healthy skin.
- Application: Ideal for specific, well-demarcated plaques like those often found on the elbows. Sessions are typically quicker.
- Side Effects: Similar to NB-UVB, but localized, primarily erythema or blistering at the treated site.
- PUVA (Psoralen plus UVA):
- Mechanism: Psoralen (a light-sensitizing medication, taken orally or applied topically) is followed by exposure to UVA light.
- Application: Less commonly used now due to higher risk of side effects and the availability of newer therapies.
- Side Effects: Nausea (oral psoralen), severe sunburn, increased risk of skin cancer and cataracts.
III. Systemic Treatments for Psoriasis on the Elbows:
Reserved for moderate to severe psoriasis on the elbows, extensive disease, or when topical and phototherapy treatments are insufficient. These medications affect the entire body.
- Oral Medications:
- Methotrexate: An immunosuppressant that slows the growth of skin cells and reduces inflammation. Used weekly.
- Cyclosporine: A potent immunosuppressant used for severe psoriasis, especially for rapid control of flares. Used for shorter durations due to potential kidney toxicity and high blood pressure.
- Acitretin: An oral retinoid that helps normalize skin cell growth. Often used for pustular or erythrodermic psoriasis but can be effective for chronic plaque psoriasis.
- Apremilast (Otezla): A phosphodiesterase-4 (PDE4) inhibitor that modulates inflammatory pathways. Generally well-tolerated.
- Deucravacitinib (Sotyktu): A selective allosteric tyrosine kinase 2 (TYK2) inhibitor, newer oral systemic option targeting specific inflammatory pathways.
- Biologics (Injectable/Infusion):
- Mechanism: Target specific parts of the immune system involved in psoriasis inflammation. Generally highly effective and have improved safety profiles compared to older systemic drugs.
- Types:
- TNF-alpha inhibitors: Adalimumab (Humira), Etanercept (Enbrel), Infliximab (Remicade).
- IL-12/23 inhibitors: Ustekinumab (Stelara).
- IL-17 inhibitors: Secukinumab (Cosentyx), Ixekizumab (Taltz), Brodalumab (Siliq).
- IL-23 inhibitors: Guselkumab (Tremfya), Risankizumab (Skyrizi), Tildrakizumab (Ilumya).
- Application: Administered via subcutaneous injection (self-administered by patient) or intravenous infusion (in a clinic setting).
- Side Effects: Increased risk of infections (especially upper respiratory infections), injection site reactions. Requires careful screening for tuberculosis and other infections prior to initiation.
IV. Lifestyle and Home Management for Psoriasis on the Elbows:
These strategies complement medical treatments and help manage symptoms and prevent flare-ups of elbow psoriasis.
- Moisturization: Regular and liberal application of thick, emollient moisturizers helps to hydrate the skin, reduce dryness, soften scales, and improve skin barrier function. Petroleum jelly, heavy creams, and ointments are often recommended.
- Avoiding Triggers: Identifying and avoiding known triggers such as stress, smoking, excessive alcohol consumption, certain medications (e.g., lithium, beta-blockers), and skin trauma can help prevent flare-ups.
- Gentle Skin Care: Avoiding harsh soaps, hot water, and vigorous scrubbing can minimize irritation to the psoriatic skin on the elbows.
- Diet and Nutrition: While no specific diet cures psoriasis, some individuals report benefits from anti-inflammatory diets or omega-3 fatty acid supplementation. Maintaining a healthy weight can also improve treatment outcomes.
- Stress Management: Stress is a well-known trigger for psoriasis flares. Techniques like yoga, meditation, mindfulness, and regular exercise can help manage stress levels.
Consultation with a dermatologist is essential for an accurate diagnosis and a personalized psoriasis on the elbows treatment plan. Given the chronic nature of psoriasis, ongoing management and regular follow-ups are crucial to achieve and maintain disease control, manage potential side effects of treatments, and adapt the therapeutic strategy as needed. The goal is to reduce inflammation, clear the skin, alleviate discomfort, and ultimately enhance the overall quality of life for individuals living with psoriasis on the elbow skin.
By understanding the spectrum of available therapies, individuals can work with their healthcare providers to find the most effective and tolerable regimen for managing their specific presentation of elbow psoriasis symptoms. New treatments are continuously being developed, offering increasing hope for better control of this challenging condition.
Regular application of prescribed medications, consistent moisturization, and attention to lifestyle factors form the cornerstone of successful long-term management for psoriasis on the elbows. This proactive approach helps to minimize discomfort and keep the skin as clear as possible, improving both physical and psychological well-being. Ultimately, effective management of psoriasis on the elbows symptoms pictures requires a comprehensive and individualized treatment strategy.