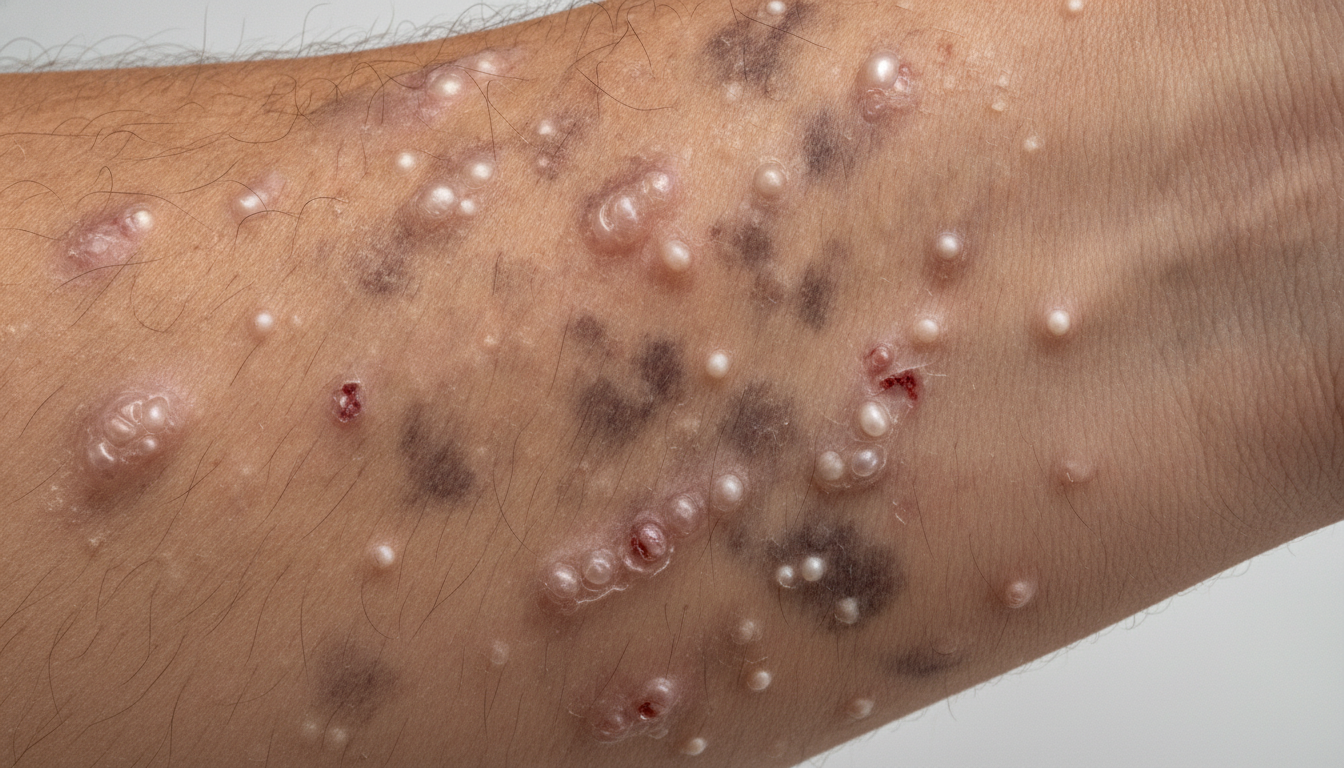
This article provides a visual guide to the varied manifestations of porphyria, offering detailed descriptions of how the condition presents on the skin and other visible signs. By exploring porphyria symptoms pictures, individuals and healthcare professionals can gain a clearer understanding of this complex group of disorders.
Porphyria Symptoms Pictures
Porphyria is characterized by a diverse range of symptoms, many of which manifest visibly on the skin, making them suitable for photographic documentation. These visible manifestations are crucial for diagnosis and monitoring, and understanding them provides invaluable insight into the patient’s experience. The broad spectrum of porphyria types means that symptoms can vary significantly, encompassing acute neurological crises that may impact facial expression or body posture, and chronic cutaneous signs that permanently alter skin texture and appearance. Recognizing these visual cues is the first step in identifying and managing the condition effectively.
The skin is a primary canvas for porphyria symptoms pictures, particularly in the cutaneous porphyrias. Patients often present with extreme photosensitivity, leading to severe reactions upon sun exposure. These reactions can range from immediate burning, stinging, and itching sensations to profound swelling, erythema, and eventually, blistering. The blisters themselves can be quite dramatic, varying in size from small vesicles to large, tense bullae. These lesions typically appear on sun-exposed areas such as the hands, forearms, face, and neck. When these blisters rupture, they can lead to erosions, crusting, and a high risk of secondary bacterial infection, which further complicates the visual presentation. Chronic blistering and trauma can result in significant scarring, often described as atrophic or hypertrophic, and can be quite disfiguring over time.
Beyond acute blistering, other chronic skin changes frequently observed in porphyria symptoms pictures include a distinctive pattern of hyperpigmentation. This darkening of the skin can be patchy, diffuse, or concentrated in sun-exposed areas, giving the skin a mottled or tanned appearance even without recent sun exposure. This hyperpigmentation can be particularly noticeable on the face and dorsum of the hands. Another prominent feature, especially in Porphyria Cutanea Tarda (PCT), is hypertrichosis, characterized by excessive fine hair growth. This vellus hair can appear on the temples, cheeks, and other areas, contributing to the altered aesthetic of the patient. The skin also tends to exhibit increased fragility, meaning minor trauma or friction can cause skin tears and wounds, which are slow to heal and prone to infection.
Long-term complications visible in porphyria symptoms pictures may include milia, which are small, white, keratin-filled cysts that form on the skin, particularly in areas where blisters have previously healed. These milia are often seen on the back of the hands and fingers. In some severe cases, especially in Congenital Erythropoietic Porphyria (CEP), chronic damage can lead to a condition resembling scleroderma-like changes, where the skin becomes thickened, hardened, and less elastic, particularly on the face and extremities. This can restrict joint movement and lead to further functional impairment. Understanding the progression and variety of these cutaneous signs is vital for accurate diagnosis and ongoing patient care, forming the core of any comprehensive collection of porphyria symptoms pictures.
Detailed visible signs include:
* Acute blistering and bullae:
* Location: Dorsal hands, fingers, forearms, face, neck, scalp.
* Characteristics: Tense, fluid-filled vesicles or bullae, often appearing after sun exposure.
* Evolution: Rupture easily, leading to erosions, crusts, and secondary infection.
* Healing: Leaves significant scarring, milia, and dyspigmentation.
* Skin fragility:
* Manifestation: Minor trauma (e.g., rubbing, scratching) causes skin tears or blisters.
* Consequences: Chronic wounds, increased risk of infection, impaired healing.
* Hyperpigmentation:
* Appearance: Patchy or diffuse darkening of the skin.
* Distribution: Predominantly sun-exposed areas (face, hands, neck), but can be generalized.
* Color: Tan to dark brown, often irregular.
* Hypertrichosis/Hirsutism:
* Description: Excessive growth of fine, dark hair.
* Location: Most commonly on the temples, cheeks, forehead, and forearms.
* Significance: A prominent feature in Porphyria Cutanea Tarda (PCT).
* Milia:
* Description: Small, white, dome-shaped cysts.
* Location: Frequently found on the back of the hands, fingers, and face in areas of previous blistering.
* Formation: Result of healing from blisters and erosions.
* Scleroderma-like changes:
* Appearance: Skin thickening and induration.
* Location: Primarily on the face and hands, mimicking systemic sclerosis.
* Impact: Can lead to taut skin, reduced elasticity, and joint contractures.
* Erythema and edema:
* Occurrence: Immediate reactions to sun exposure, particularly in Erythropoietic Protoporphyria (EPP).
* Characteristics: Redness, swelling, burning, itching, stinging sensations.
* Progression: Can develop into purpuric lesions or chronic lichenification.
* Erythrodontia (red teeth):
* Specific to: Congenital Erythropoietic Porphyria (CEP).
* Appearance: Reddish-brown discoloration of teeth, visible under UV light.
* Cause: Deposition of porphyrins in dental tissue.
* Urine discoloration:
* Appearance: Reddish-brown or purple urine, especially after standing or upon exposure to light.
* Visibility: Not a direct skin symptom, but a crucial visible diagnostic sign.
* Cause: Excretion of excess porphyrins and porphyrin precursors.
* Acro-osteolysis:
* Appearance: Resorption of terminal phalanges of fingers and toes.
* Visibility: Can lead to shortened, stubby digits and deformities.
* Severity: A severe, chronic complication, particularly in CEP.
* Corneal scarring and blindness:
* Appearance: Ocular damage from chronic porphyrin deposition and photosensitivity.
* Impact: Visual impairment, potentially leading to blindness.
* Severity: Severe, chronic complication, particularly in CEP.
* Pseudoporphyria:
* Appearance: Clinical features resembling porphyria cutanea tarda (blistering, fragility, milia, scarring).
* Cause: Induced by certain medications (e.g., NSAIDs, furosemide, tetracyclines) or renal failure, without porphyrin abnormalities.
* Differentiation: Important for accurate diagnosis, as treatment differs significantly.
Signs of Porphyria Pictures
Capturing the varied signs of porphyria in pictures allows for a comprehensive understanding of the condition’s impact on patients. These signs extend beyond simple skin lesions, encompassing a spectrum of visible changes that are critical for clinical assessment and diagnostic pathways. While acute porphyrias like Acute Intermittent Porphyria (AIP), Hereditary Coproporphyria (HCP), and Variegate Porphyria (VP) are primarily known for their neurovisceral attacks, the profound distress, altered posture, or subtle neurological deficits during an attack can also be documented visually. However, it is the cutaneous porphyrias that offer the most dramatic and consistent visual evidence for porphyria symptoms pictures.
Porphyria Cutanea Tarda (PCT) is the most common form of cutaneous porphyria and presents with highly characteristic signs. Pictures of PCT patients frequently show a combination of the following:
* Chronic Blistering and Erosions: The dorsal aspects of the hands, fingers, and forearms are commonly affected. Blisters can range from small vesicles to large bullae, often appearing after minimal sun exposure or trauma. These rupture easily, leaving shallow erosions that heal slowly and frequently become crusted.
* Milia: Small, pearly white cysts are almost pathognomonic for PCT and often found on the back of the hands, fingers, and around the eyes. They are remnants of healed blisters.
* Skin Fragility: Patients often exhibit thin, delicate skin that tears easily with minor friction or bumps, leading to chronic wounds and scars. This fragility contributes significantly to the cumulative skin damage evident in PCT pictures.
* Hyperpigmentation: A distinctive patchy or diffuse darkening of the skin, most prominent on sun-exposed areas (face, neck, hands), giving a mottled appearance. This can sometimes be mistaken for tanning.
* Hypertrichosis: Increased fine hair growth, particularly noticeable on the temples, cheeks, and forehead, is a classic sign. This vellus hair can be dark and quite prominent.
* Scleroderma-like Changes: In advanced or chronic cases, the skin can become thickened, hardened, and waxy, particularly on the face, scalp, and neck, resembling localized scleroderma. This can lead to a mask-like facial appearance and limited movement.
* Subepidermal Blister Formation: Histopathological pictures would reveal the characteristic separation of the epidermis from the dermis, a hallmark of PCT.
For Congenital Erythropoietic Porphyria (CEP), also known as Günther’s Disease, the signs are often severe and appear very early in life. Pictures of CEP patients, especially children, often show:
* Severe Photosensitivity: Extreme vulnerability to sunlight, leading to extensive blistering, ulceration, and infection from infancy. The photosensitivity is much more severe than in PCT.
* Erythrodontia: A striking reddish-brown discoloration of the teeth due to porphyrin deposition. This is often visible under normal light and fluoresces intensely red under UV light, making for dramatic pictures.
* Hemolytic Anemia and Splenomegaly: While not directly visible on the skin, the pallor associated with severe anemia can be evident in patient pictures, and an enlarged spleen might be palpable or visible as abdominal distension.
* Urine Discoloration: Red or reddish-brown urine is an early and consistent sign, often noticed by parents in infancy. Pictures of urine samples would show this distinct color change.
* Mutilating Scars and Deformities: Chronic, recurrent blistering, infection, and tissue destruction can lead to severe scarring, loss of digits (acro-osteolysis), facial deformities (e.g., loss of nasal cartilage), and contractures, resulting in profound physical disfigurement.
* Corneal Damage: Porphyrin deposition in the eyes can cause photophobia, conjunctivitis, keratitis, and ultimately lead to corneal scarring and blindness, which can be seen in detailed ophthalmological pictures.
Erythropoietic Protoporphyria (EPP) and X-linked Protoporphyria (XLP) present with distinct signs, differing from the blistering porphyrias. Pictures of EPP/XLP patients typically show:
* Acute, Non-Blistering Photosensitivity: Unlike PCT or CEP, EPP/XLP reactions to sun exposure typically do not involve blistering initially. Instead, patients experience intense burning, stinging, itching, and tingling sensations, followed by erythema (redness) and edema (swelling) of the exposed skin.
* Urticarial Plaques: In some cases, hive-like raised red welts can appear on sun-exposed skin.
* Petechiae and Purpura: Small red or purple spots, indicating bleeding under the skin, can sometimes be seen in chronic sun-exposed areas.
* Crusting and Lichenification: Over time, chronic rubbing and scratching due to intense itching can lead to skin thickening (lichenification) and crusting.
* Pseudovesicles and Pseudo-scars: Subtle, raised lesions that can resemble vesicles but are firm to the touch, and linear depressions or pock-like scars, particularly on the knuckles, can be observed. These are often described as “wax-like” thickening.
* Facial Changes: A characteristic “cobblestone” appearance of the knuckles and thickened facial skin, especially around the nose and mouth, due to chronic light exposure and fibroblast stimulation.
* Jaundice: In cases with severe liver involvement, yellowing of the skin and whites of the eyes (scleral icterus) can be a significant visible sign.
* Gallstones: While not directly visible on the skin, severe EPP/XLP can lead to protoporphyrin deposition in the bile, forming gallstones, which can cause symptoms leading to surgical intervention.
These detailed visual signs, captured in porphyria symptoms pictures, serve as invaluable tools for medical professionals, enabling them to differentiate between the various forms of porphyria and initiate appropriate diagnostic and therapeutic interventions. The specific appearance of lesions, their distribution, and their evolution over time all contribute to a comprehensive clinical picture.
Detailed list of visible signs and their characteristics:
* Porphyria Cutanea Tarda (PCT):
* Skin Lesions:
* Blisters/Bullae: Tense, fragile, often hemorrhagic, appearing on hands, forearms, face, scalp. Rupture to form erosions and crusts.
* Milia: Small, firm, white cysts, especially on dorsal hands and periorbital areas, post-blister healing.
* Skin Fragility: Easy tearing of skin with minor trauma.
* Hyperpigmentation: Mottled, patchy, or diffuse darkening, prominent in sun-exposed areas.
* Hypertrichosis: Fine, dark hair growth on temples, cheeks, forearms.
* Sclerodermoid Plaques: Thickened, hardened skin, typically on face, neck, scalp, mimicking scleroderma.
* Atrophic Scarring: Thin, depressed scars from healed lesions.
* Systemic Signs (potentially visible):
* Urine Discoloration: Reddish-brown urine, especially after standing.
* Hepatomegaly: Enlarged liver, sometimes causing visible abdominal distension.
* Congenital Erythropoietic Porphyria (CEP) / Günther’s Disease:
* Severe Photosensitivity: Extensive, severe blistering, bullae, and ulceration from early infancy on all sun-exposed skin.
* Erythrodontia: Distinctive reddish-brown discoloration of deciduous and permanent teeth, fluorescing red under Wood’s lamp.
* Mutilating Lesions: Chronic and recurrent infections leading to severe scarring, loss of digits (acro-osteolysis), facial cartilage erosion (nose, ears), and contractures.
* Ocular Involvement: Photophobia, conjunctivitis, keratitis, corneal scarring, and eventual blindness from porphyrin deposition.
* Hair Changes: Increased hair growth (hypertrichosis), sometimes coarse, on exposed areas.
* Urine Discoloration: Deep red or reddish-brown urine from birth.
* Pallor: Due to severe hemolytic anemia.
* Splenomegaly: Enlarged spleen, sometimes visible or palpable.
* Erythropoietic Protoporphyria (EPP) / X-linked Protoporphyria (XLP):
* Acute Photosensitivity Reactions:
* Subjective Sensations: Intense burning, stinging, itching, tingling within minutes of sun exposure.
* Objective Signs: Erythema (redness), edema (swelling) of exposed skin.
* Urticarial Plaques: Transient, hive-like lesions.
* Petechiae/Purpura: Small blood spots from capillary damage.
* Chronic Skin Changes:
* Lichenification: Thickened, leathery skin from chronic rubbing.
* Crusting: From chronic scratching or exudation.
* Pseudo-scars: Pock-like or linear depressions, particularly on knuckles and dorsal hands.
* Perioral/Periorbital Thickening: Waxy induration around the mouth and eyes.
* Cobblestone Appearance: On knuckles and dorsal hands.
* Liver Involvement (visible in severe cases):
* Jaundice: Yellowing of skin and sclera due to cholestasis or liver failure.
* Xanthelasma-like lesions: Rarely, around the eyes due to lipid deposition secondary to cholestasis.
* Acute Intermittent Porphyria (AIP), Hereditary Coproporphyria (HCP), Variegate Porphyria (VP):
* No Primary Skin Lesions (AIP): AIP typically lacks cutaneous manifestations.
* Cutaneous Manifestations (HCP, VP): HCP and VP can exhibit blistering photosensitivity similar to PCT, but often less severe and not always present. Skin signs are generally identical to PCT when present.
* Neurological/Psychiatric Manifestations (Acute Attacks):
* Facial Expression: Signs of severe pain, distress, anxiety, or confusion.
* Motor Weakness: Visible paralysis or paresis, affecting gait, posture, or limb movement.
* Autonomic Instability: Profuse sweating, pallor, or flushed skin.
* Urine Discoloration: Darkening of urine (reddish-brown) during attacks.
* Hepatoerythropoietic Porphyria (HEP):
* Presents similarly to severe CEP but typically has a later onset (childhood).
* Severe Photosensitivity with blistering, hypertrichosis, and chronic skin damage.
* Hemolytic Anemia and splenomegaly.
* Red Urine.
Early Porphyria Photos
Identifying early porphyria photos is critical because early diagnosis can significantly impact disease progression and patient outcomes. The initial symptoms of porphyria can often be subtle, non-specific, and easily misdiagnosed, particularly when looking at early porphyria photos. This makes awareness of their varied presentations paramount. For acute porphyrias, early signs are often neurological and visceral, not directly visible on the skin, but their impact on a patient’s overall presentation can be subtle yet discernible.
In Acute Intermittent Porphyria (AIP), Hereditary Coproporphyria (HCP), and Variegate Porphyria (VP), early symptoms typically precede any visible skin manifestations (with AIP having no cutaneous signs at all). Early porphyria photos might depict:
* Subtle signs of distress: Patients might appear anxious, withdrawn, or in pain. Facial expressions might convey discomfort, tension, or fatigue even without overt skin lesions.
* Mild abdominal distension or guarding: While internal, severe abdominal pain can sometimes lead to visible tenseness or distension of the abdomen.
* Changes in mood or behavior: Photos might capture unusual agitation, confusion, or depression, reflecting early neurological involvement.
* Early neurological weakness: Subtle signs like a slight limp, difficulty with fine motor skills, or changes in gait that might be caught in candid early porphyria photos.
* Urine changes: Although not a direct physical symptom on the patient’s body, pictures of urine samples showing a reddish hue, particularly after standing in light, can be one of the earliest objective indicators.
For Porphyria Cutanea Tarda (PCT), the most common cutaneous porphyria, early porphyria photos would focus on nascent skin changes. These are often less severe than in established disease and can be easily overlooked or attributed to other common skin conditions. Early PCT photos might show:
* Mild skin fragility: Patients may notice their skin tearing easily with minor bumps or friction, leading to small, superficial wounds that are slow to heal. These might be documented as small erosions or scabs.
* Occasional small blisters: Rather than widespread bullae, early PCT might feature isolated, small vesicles or blisters, particularly on the dorsal hands or forearms after significant sun exposure. These may be mistaken for common sunburn blisters.
* Increased sun sensitivity: Patients might report an unusual burning sensation or prolonged redness after sun exposure, even before overt blistering occurs. This subjective experience would precede visible signs.
* Faint hyperpigmentation: Subtle darkening of the skin, especially on the face or hands, which might be initially dismissed as a natural tan or age spots. The patchy or mottled quality might not yet be pronounced.
* Scattered fine hair growth (hypertrichosis): A slight increase in vellus hair on the temples or cheeks, which might be very fine and easily missed.
* Absence of prominent milia or scarring: These develop later, after repeated blistering and healing cycles. Early porphyria photos of PCT would typically lack these features.
In Erythropoietic Protoporphyria (EPP) and X-linked Protoporphyria (XLP), the earliest signs are characterized by acute photosensitivity without immediate blistering. Early porphyria photos for EPP/XLP would attempt to capture:
* Acute erythema and edema: Immediately after sun exposure, the affected skin areas (face, hands, forearms) might show noticeable redness and swelling. These reactions are typically short-lived and resolve within hours to days, but can be quite intense.
* Subjective distress: Pictures might show individuals shielding themselves from the sun, looking uncomfortable, or scratching due to the intense burning, itching, or stinging sensations they experience.
* Mild skin thickening: Over months to a few years, subtle waxy thickening of the skin, particularly on the knuckles or around the mouth, might become visible before the characteristic “cobblestone” changes fully develop.
* Lack of blistering: Crucially, early EPP/XLP photos would typically not show the large, tense blisters seen in PCT or CEP, which helps differentiate these conditions.
For Congenital Erythropoietic Porphyria (CEP) / Günther’s Disease, early porphyria photos capture symptoms that often present in infancy or early childhood, making them dramatically distinct:
* Red urine in diapers: This is often one of the first and most striking signs, presenting as a reddish-brown stain on diapers. Pictures of affected diapers can be very informative.
* Severe blistering and photosensitivity in infants: Even minimal sun exposure can cause severe, widespread blistering on exposed skin. These blisters are often large, hemorrhagic, and easily infected, leading to significant scarring very early in life. Early photos would show the dramatic response to light.
* Fragile skin: The skin of infants with CEP is extremely fragile, leading to easy tearing and poor wound healing, visible as multiple small wounds or scabs.
* Early erythrodontia: While permanent teeth are more distinctly affected, even deciduous teeth can show some reddish discoloration if the disease is very severe, which might be visible in early childhood dental photos.
Capturing these initial and subtle manifestations in early porphyria photos helps in raising suspicion for porphyria, prompting appropriate diagnostic testing, and allowing for timely intervention to prevent more severe, irreversible damage. The early presentation dictates the urgency and type of subsequent investigation.
Detailed list of early visible signs and their context:
* Acute Intermittent Porphyria (AIP), Hereditary Coproporphyria (HCP), Variegate Porphyria (VP) (Acute Porphyrias):
* Behavioral/Emotional Changes: Unexplained anxiety, irritability, agitation, or signs of depression. Photos might capture a patient looking unusually distressed or withdrawn.
* Subtle Neurological Symptoms: Early muscle weakness (e.g., slight foot drop, difficulty lifting objects), tremors, or sensory disturbances that are not yet severe but detectable in movement or posture.
* Abdominal Discomfort: Signs of discomfort, slight guarding of the abdomen, or facial expressions indicating pain, even if no visible swelling.
* Urine Discoloration: Reddish or dark urine, especially on standing, collected and photographed. This is often the first objective sign for an acute attack.
* Porphyria Cutanea Tarda (PCT) (Cutaneous Porphyria):
* Mild Skin Fragility: Small, superficial skin tears or erosions on the hands or forearms from minor trauma.
* Occasional Blisters: Isolated, small vesicles or bullae on sun-exposed areas (e.g., dorsal hands) after prolonged sun exposure, often healing without significant scarring initially.
* Increased Sun Sensitivity: Reports of exaggerated redness, burning, or prolonged reaction to sun compared to usual, without immediate severe blistering.
* Subtle Hyperpigmentation: Faint, patchy darkening of skin on face or hands, easily mistaken for tanning.
* Mild Hypertrichosis: Barely noticeable increase in fine, vellus hair on temples or cheeks.
* Absence of Milia/Significant Scars: These are typically later developments.
* Erythropoietic Protoporphyria (EPP) / X-linked Protoporphyria (XLP) (Erythropoietic Porphyrias):
* Immediate Photosensitivity Reaction: Within minutes of sun exposure, intense subjective symptoms (burning, stinging, itching) followed by visible erythema and edema on exposed skin.
* Transient Swelling/Redness: Photos capturing acute swelling and redness that resolves within hours or days, without blister formation.
* No Initial Blistering: Key differentiating factor from other cutaneous porphyrias.
* Subtle Waxy Thickening: Very fine, almost imperceptible thickening of skin on knuckles or face over time, preceding distinct pseudo-scars.
* Photophobia: Increased sensitivity to light in the eyes, manifesting as squinting or avoidance of bright environments.
* Congenital Erythropoietic Porphyria (CEP) (Erythropoietic Porphyria):
* Red Diapers: Deep reddish-brown staining of infant diapers due to high porphyrin excretion.
* Early Severe Blistering: Extensive, large, hemorrhagic blisters and bullae on any sun-exposed skin of an infant, leading to immediate concern.
* Extreme Skin Fragility: Skin tearing easily with minimal contact, leading to multiple open wounds.
* Anemia-related Pallor: Visible paleness of the skin and mucous membranes due to severe hemolytic anemia.
* Feeding Difficulties/Irritability: Due to generalized discomfort and chronic illness.
* Early Erythrodontia: Faint reddish discoloration of primary teeth, visible even in infancy.
Skin rash Porphyria Images
The term “skin rash porphyria images” encapsulates the diverse dermatological manifestations that are central to the diagnosis and management of cutaneous porphyrias. These images typically showcase the unique patterns of skin damage that differentiate porphyrias from other skin conditions and among different types of porphyria. The skin lesions are primarily driven by the accumulation of porphyrins in the skin, which become highly reactive upon exposure to ultraviolet (UV) light, leading to oxidative damage. This section will delve into the specific characteristics of these “rashes” as captured in porphyria images.
In Porphyria Cutanea Tarda (PCT), skin rash porphyria images predominantly feature the consequences of severe photosensitivity and skin fragility. The characteristic rash involves:
* Blisters and Bullae: These are the most striking feature. Images show tense, fluid-filled lesions varying in size, from small vesicles to large bullae, typically on the dorsal hands, fingers, forearms, face, and sometimes the scalp. They are often clear initially but can become hemorrhagic.
* Erosions and Crusting: Following the rupture of blisters, raw, weeping erosions are formed. These heal slowly and become covered with yellowish or brownish crusts, often seen in combination with intact blisters.
* Atrophic Scars: Healed lesions frequently leave behind thin, depressed, “cigarette paper-like” scars. Images may show extensive scarring from recurrent episodes.
* Milia: Small, white, firm cysts are commonly observed on the back of the hands, fingers, and around the eyes in skin rash porphyria images of PCT. They appear as tiny white dots on previously affected skin.
* Hyperpigmentation: A patchy or diffuse darkening of the skin, giving it a mottled, “dirty” appearance. This hyperpigmentation is often more pronounced in sun-exposed areas but can be widespread.
* Hypertrichosis: Images frequently show increased growth of fine, dark hair, particularly on the temples, cheeks, and forearms. This can be quite noticeable and is a key feature in many PCT patients.
* Skin Fragility: The skin is exceedingly fragile, meaning minor trauma results in easy tearing or blistering. Images might capture multiple small wounds or superficial tears alongside other lesions.
* Sclerodermoid Changes: In chronic cases, the skin can become thickened, hardened, and waxy, mimicking localized scleroderma. This is often seen on the face and neck in skin rash porphyria images, leading to a stiff or mask-like appearance.
For Congenital Erythropoietic Porphyria (CEP) / Günther’s Disease, the “skin rash” is much more severe and mutilating, reflecting profound photosensitivity from infancy. Skin rash porphyria images of CEP reveal:
* Extensive and Mutilating Blistering: Large, deep, hemorrhagic blisters and bullae appear on all sun-exposed skin from birth. These recurrent lesions lead to profound tissue destruction.
* Chronic Ulceration and Infection: The blisters often become infected, leading to chronic, non-healing ulcers and severe secondary bacterial infections. Images would show purulent lesions and significant inflammation.
* Severe Scarring and Deformities: The most striking feature. Chronic damage results in severe atrophic and hypertrophic scarring, contractures, and characteristic mutilations, particularly of the digits (acro-osteolysis, leading to loss of fingers and toes), nose, and ears. Images of hands and faces are often severely disfigured.
* Hypertrichosis: Excessive, sometimes coarse, hair growth, particularly on the face and extremities.
* Erythrodontia: While not a “rash,” the reddish-brown discoloration of teeth (due to porphyrin deposition) is a highly distinctive visible sign in CEP.
* Corneal Scars: Ocular involvement leading to scarring and potentially blindness can also be seen in specialized images.
In Erythropoietic Protoporphyria (EPP) and X-linked Protoporphyria (XLP), the “skin rash” differs significantly as it is typically non-blistering in its acute phase. Skin rash porphyria images of EPP/XLP show:
* Acute Erythema and Edema: Immediately after sun exposure, the affected skin areas (face, hands, forearms) become intensely red and swollen. These reactions are often accompanied by severe burning and itching sensations.
* Urticarial Plaques: Some individuals develop transient, hive-like raised red wheals or plaques on sun-exposed skin.
* Petechiae and Purpura: Small pinpoint red or purple spots, indicating capillary fragility and minor bleeding, can occasionally be seen.
* Chronic Skin Changes: Over time, repeated sun exposure and scratching lead to distinct changes:
* Lichenification: Thickened, leathery skin, especially on the hands and face.
* Crusting: From chronic scratching or weeping.
* Pseudo-scars: Characteristic pock-like or linear depressions, particularly on the knuckles, often described as waxy or cobblestone-like.
* Perioral and Periorbital Thickening: Induration and thickening of the skin around the mouth and eyes, which can alter facial contours.
The precise identification of these specific features in skin rash porphyria images is paramount for dermatologists and general practitioners to correctly diagnose porphyria and distinguish it from other dermatoses. The pattern of photosensitivity, the presence or absence of blistering, the type of scarring, and associated features like hypertrichosis or erythrodontia, all contribute to the diagnostic puzzle. Therefore, a comprehensive library of skin rash porphyria images is an essential educational and diagnostic resource.
Detailed list of skin rash manifestations and their specific features:
* Blistering and Bullae (Porphyria Cutanea Tarda, Congenital Erythropoietic Porphyria, Hepatoerythropoietic Porphyria, some Variegate and Hereditary Coproporphyria):
* Appearance: Tense, fluid-filled, clear or hemorrhagic vesicles/bullae.
* Size Range: From a few millimeters to several centimeters in diameter.
* Distribution: Primarily dorsal hands, fingers, forearms, face, neck, scalp; in CEP, can be very extensive on all sun-exposed skin.
* Evolution: Rupture easily, forming erosions and crusts.
* Complications: High risk of secondary bacterial infection.
* Erosions and Ulcers:
* Appearance: Raw, shallow to deep skin defects following blister rupture or trauma.
* Healing: Slow to heal, often with crusting and scabbing.
* Severity: Particularly deep and chronic in CEP, leading to significant tissue loss.
* Crusting:
* Appearance: Yellowish, brownish, or hemorrhagic crusts covering healing erosions.
* Persistence: Can persist for weeks due to slow healing.
* Atrophic Scarring:
* Appearance: Thin, depressed, sometimes shiny scars, often described as “cigarette paper” scars.
* Distribution: In areas of previous blistering and erosion.
* Severity: Can be extensive and disfiguring, especially in chronic cases and CEP.
* Hypertrophic Scarring/Keloids:
* Appearance: Raised, thickened, firm scars, less common but can occur in traumatized areas.
* Milia:
* Appearance: Small, pearly white, dome-shaped cysts, 1-2 mm in diameter.
* Location: Typically on dorsal hands, fingers, periorbital region, sites of previous blisters.
* Pathognomonic: Highly characteristic of PCT and other blistering porphyrias.
* Hyperpigmentation:
* Appearance: Patchy, diffuse, or mottled darkening of the skin.
* Color: Tan to dark brown.
* Distribution: Predominantly sun-exposed areas (face, neck, hands, forearms).
* Persistence: Can be persistent even with disease control.
* Hypertrichosis/Hirsutism:
* Appearance: Excessive growth of fine, dark vellus hair.
* Location: Forehead, temples, cheeks, forearms, dorsal hands.
* Prominence: Particularly noticeable in PCT and CEP.
* Skin Fragility:
* Appearance: Minor trauma results in skin tears, cuts, or blisters.
* Impact: Leads to chronic wounds, increased infection risk.
* Sclerodermoid Changes:
* Appearance: Skin thickening, induration, and hardening.
* Location: Face, scalp, neck, dorsal hands, mimicking systemic sclerosis.
* Impact: Reduced skin elasticity, tautness, potential for joint contractures.
* Erythema and Edema (Erythropoietic Protoporphyria, X-linked Protoporphyria):
* Appearance: Acute redness and swelling of sun-exposed skin.
* Onset: Rapidly after sun exposure.
* Accompanying Symptoms: Intense burning, stinging, itching.
* Resolution: Typically resolves within hours to days.
* Urticarial Plaques (Erythropoietic Protoporphyria, X-linked Protoporphyria):
* Appearance: Transient, raised, itchy, red welts, similar to hives.
* Onset: After sun exposure.
* Petechiae and Purpura (Erythropoietic Protoporphyria, X-linked Protoporphyria):
* Appearance: Small, pinpoint red (petechiae) or larger purple (purpura) spots.
* Cause: Capillary fragility.
* Distribution: Sun-exposed areas.
* Lichenification (Erythropoietic Protoporphyria, X-linked Protoporphyria):
* Appearance: Thickened, leathery skin with exaggerated skin markings.
* Cause: Chronic rubbing and scratching.
* Location: Hands, face, areas of chronic pruritus.
* Pseudo-scars / “Cobblestone” Appearance (Erythropoietic Protoporphyria, X-linked Protoporphyria):
* Appearance: Waxy, pock-like depressions or linear furrowing, particularly over knuckles and dorsal hands.
* Cause: Chronic light exposure and fibroblast stimulation.
* Distinguishing feature: Distinct from atrophic scars of blistering porphyrias.
* Acro-osteolysis (Congenital Erythropoietic Porphyria):
* Appearance: Resorption and shortening of terminal phalanges of fingers and toes.
* Impact: Causes severe digital deformities and loss of digits.
* Mechanism: Chronic infection, inflammation, and porphyrin-induced bone damage.
Porphyria Treatment
Porphyria treatment is highly specific to the type of porphyria, aiming to manage acute attacks, prevent chronic symptoms, and address underlying disease mechanisms. The approach to porphyria treatment involves a combination of medication, lifestyle modifications, and, in severe cases, more aggressive interventions. Effective porphyria treatment requires a precise diagnosis, as therapies for acute porphyrias differ dramatically from those for cutaneous forms. The overarching goals are to reduce porphyrin accumulation, alleviate symptoms, and prevent long-term complications, often requiring lifelong management.
Treatment for Acute Hepatic Porphyrias (Acute Intermittent Porphyria – AIP, Hereditary Coproporphyria – HCP, Variegate Porphyria – VP)
Acute attacks are medical emergencies requiring prompt and aggressive porphyria treatment to prevent irreversible neurological damage.
* Hemin therapy:
* Medication: `Panhematin` (hemin for injection) or `Normosang` (hemin arginate).
* Mechanism: Represses hepatic ALA synthase, the rate-limiting enzyme in heme synthesis, thereby reducing the production of neurotoxic porphyrin precursors (ALA and PBG).
* Administration: Intravenous infusion. Administered early in an attack, often for 4 days.
* Importance: The cornerstone of acute porphyria treatment, significantly shortening the duration and severity of attacks.
* Glucose loading / High carbohydrate intake:
* Mechanism: Glucose also helps suppress ALA synthase activity.
* Administration: Oral or intravenous dextrose solution. Typically administered as part of initial management, especially if hemin is not immediately available or for milder attacks.
* Role: Supportive measure, but less potent than hemin.
* Symptomatic treatment:
* Pain management: Opioids (e.g., morphine, fentanyl) for severe abdominal pain, as conventional analgesics may be ineffective or even harmful.
* Antiemetics: Prochlorperazine, ondansetron for nausea and vomiting.
* Anxiolytics: Benzodiazepines (e.g., lorazepam) for anxiety, agitation, and seizures. Caution is advised as some anxiolytics can be porphyrinogenic.
* Management of hypertension and tachycardia: Beta-blockers (e.g., propranolol) if necessary.
* Fluid and electrolyte balance: Aggressive rehydration and correction of hyponatremia (low sodium) if present, which can exacerbate neurological symptoms.
* Avoidance of triggers:
* Drugs: Identify and strictly avoid porphyrinogenic drugs (e.g., certain barbiturates, sulfonamides, some anticonvulsants, oral contraceptives). A comprehensive list of safe/unsafe drugs is essential.
* Alcohol: Complete abstinence.
* Fasting/Low caloric intake: Maintain a regular, high-carbohydrate diet to prevent metabolic stress.
* Stress: Physical and psychological stress can trigger attacks.
* Infections: Prompt treatment of infections.
* Givosiran (`Givlaari`):
* Mechanism: An RNA interference (RNAi) therapeutic that targets ALAS1 mRNA in the liver, leading to a reduction in hepatic ALAS1 protein levels and thereby decreasing the synthesis of neurotoxic ALA and PBG.
* Administration: Subcutaneous injection.
* Indication: Approved for adults with acute hepatic porphyria (AHP) for the reduction of the frequency of attacks. A significant advancement in chronic management.
* Benefits: Offers long-term prevention of acute attacks, reducing the need for recurrent hemin infusions.
* Liver transplantation:
* Indication: For severe, refractory cases with life-threatening, recurrent acute attacks or progressive neuropathy unresponsive to other therapies.
* Outcome: Can be curative as the liver is the primary site of the enzymatic defect.
Treatment for Porphyria Cutanea Tarda (PCT)
PCT porphyria treatment focuses on reducing porphyrin levels in the liver, which alleviates photosensitivity and skin lesions.
* Phlebotomy (therapeutic venesection):
* Mechanism: Reduces hepatic iron stores, which are thought to contribute to porphyrin accumulation and oxidative stress. Iron depletion is key to remission.
* Administration: 450-500 mL of blood removed every 1-2 weeks until serum ferritin levels are within the low-normal range (e.g., 20-50 ng/mL).
* Outcome: Leads to clinical remission, with healing of skin lesions and improved skin fragility.
* Maintenance: May require occasional phlebotomy to maintain remission.
* Low-dose chloroquine or hydroxychloroquine:
* Mechanism: Facilitates the excretion of excess porphyrins from the liver into the urine by forming water-soluble complexes. High doses can cause acute liver toxicity, so low doses are critical.
* Administration: Very low doses (e.g., 125 mg chloroquine once or twice weekly, or 200 mg hydroxychloroquine once or twice weekly).
* Caution: High doses can induce acute hepatic porphyrin release, worsening symptoms.
* Outcome: Effective for patients who cannot tolerate phlebotomy or in combination.
* Avoidance of triggers:
* Alcohol: Complete abstinence is crucial for liver health.
* Iron supplements: Avoid unless there is a genuine iron deficiency unrelated to PCT, as iron exacerbates the condition.
* Estrogens: Discontinuation of oral contraceptives or hormone replacement therapy if possible.
* Sunlight exposure: Strict sun protection measures (protective clothing, broad-spectrum sunscreens, avoidance of peak sun hours).
* Treatment of associated conditions:
* Hepatitis C virus (HCV) infection: Antiviral therapy for HCV is critical as it often coexists with PCT and improves PCT symptoms.
* Hemochromatosis: Management of iron overload.
* HIV infection: Antiretroviral therapy.
* Excessive alcohol consumption: Counseling and support for cessation.
Treatment for Congenital Erythropoietic Porphyria (CEP) / Günther’s Disease
CEP porphyria treatment is primarily supportive, aiming to reduce porphyrin production and protect against light.
* Strict sun protection:
* Measures: Opaque clothing, wide-brimmed hats, gloves, broad-spectrum sunscreens, avoidance of sun exposure, tinted windows.
* Importance: Essential from infancy to prevent blistering and mutilation.
* Blood transfusions / Hypertransfusion therapy:
* Mechanism: Suppresses erythropoiesis (red blood cell production) in the bone marrow, thereby reducing the production of porphyrins.
* Indication: For severe hemolytic anemia and highly active disease.
* Goal: To keep hemoglobin levels high enough to suppress endogenous erythropoiesis.
* Risk: Iron overload, requiring chelation therapy.
* Splenectomy:
* Indication: For severe hemolysis and splenomegaly (enlarged spleen) that consumes red blood cells.
* Outcome: Can reduce transfusion requirements but does not cure the porphyria.
* Bone marrow transplantation (BMT) / Hematopoietic Stem Cell Transplantation (HSCT):
* Indication: The only curative treatment available for CEP. Reserved for severe cases, especially in children, where a suitable donor is found.
* Risk: High risk procedure with significant morbidity and mortality.
* Symptomatic care:
* Wound care: Meticulous care of blisters and ulcers to prevent infection and promote healing.
* Infection control: Prompt treatment of bacterial infections.
* Pain management.
* Gene therapy:
* Status: Experimental, promising but not yet widely available. Aims to correct the genetic defect.
Treatment for Erythropoietic Protoporphyria (EPP) and X-linked Protoporphyria (XLP)
EPP/XLP porphyria treatment focuses on increasing light tolerance and preventing liver complications.
* Strict sun protection:
* Measures: Protective clothing, broad-spectrum sunscreens (especially physical blockers like zinc oxide and titanium dioxide), avoidance of peak sun hours.
* Importance: Prevents acute painful photosensitivity reactions.
* Afamelanotide (`Scenesse`):
* Mechanism: A synthetic analogue of alpha-melanocyte-stimulating hormone (α-MSH). It increases eumelanin production in the skin, providing natural photoprotection.
* Administration: Subcutaneous implant.
* Outcome: Significantly increases sun exposure tolerance, reduces pain and severity of phototoxic reactions, and improves quality of life.
* Indication: Approved for EPP and XLP in certain regions.
* Beta-carotene:
* Mechanism: An antioxidant that quenches reactive oxygen species, potentially offering mild photoprotection.
* Administration: Oral supplement.
* Outcome: Provides modest benefit, often resulting in yellow-orange skin discoloration. Less effective than afamelanotide.
* Liver protection and management of liver disease:
* Ursodeoxycholic acid: May be used to facilitate bile flow and prevent gallstones.
* Bile acid sequestrants (e.g., cholestyramine): Can interrupt the enterohepatic circulation of protoporphyrin, increasing fecal excretion and reducing liver load, especially in cases of emerging liver complications.
* Liver transplantation: For severe, decompensated liver failure caused by protoporphyrin accumulation (protoporphyric hepatopathy).
* Monitoring: Regular liver function tests and ultrasound to detect early signs of liver involvement.
* Iron supplementation:
* Indication: Only if genuine iron deficiency is present, as protoporphyrin levels can paradoxically be exacerbated by iron deficiency. Careful monitoring is required.
General Porphyria Treatment Considerations
* Genetic counseling: Essential for patients and families to understand the inheritance patterns and risks of porphyria.
* Psychological support: Dealing with chronic illness, pain, and visible disfigurement can significantly impact mental health. Support groups, counseling, and psychological interventions are often necessary.
* Dietary advice: Maintaining a consistent, balanced diet, avoiding fasting, and for acute porphyrias, ensuring adequate carbohydrate intake.
* Regular monitoring: Lifelong follow-up with specialists (hematologists, dermatologists, hepatologists, geneticists) to monitor disease activity, manage symptoms, and detect complications.
The field of porphyria treatment is continuously evolving, with new therapies like gene therapies and small molecule inhibitors under investigation. Personalized porphyria treatment plans are crucial, tailored to the specific type of porphyria, disease severity, and individual patient needs.