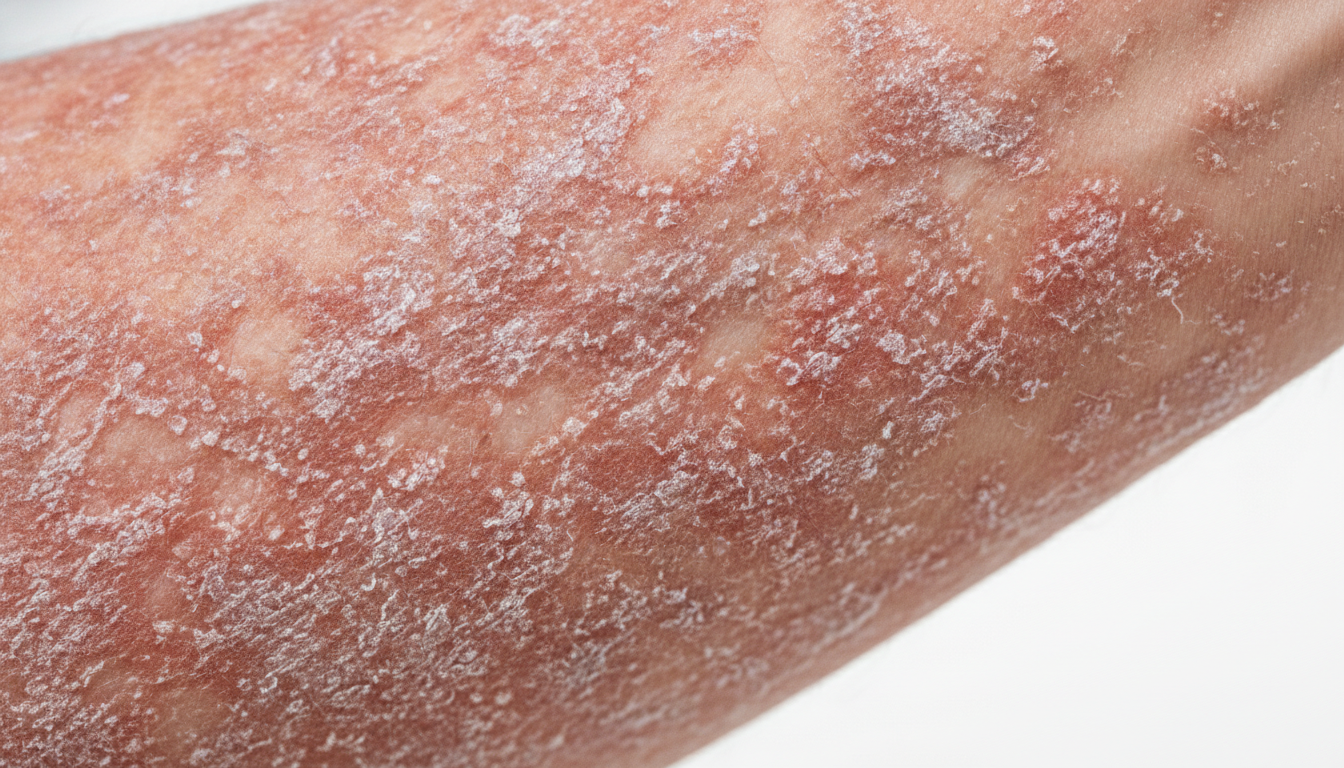
The visual manifestation of Phenylketonuria can be complex, spanning neurological, dermatological, and developmental domains, making recognition of Phenylketonuria symptoms pictures crucial for early intervention. Understanding the observable characteristics associated with this genetic disorder aids significantly in identifying potential cases and ensuring timely medical attention.
Phenylketonuria Symptoms Pictures
Individuals with untreated Phenylketonuria (PKU) present a spectrum of discernible symptoms, many of which are visually evident, particularly as the condition progresses. While direct imaging of internal metabolic processes is not possible, the
impact of uncontrolled phenylalanine levels on the central nervous system and other bodily systems leads to a range of
physical and neurological signs that can be captured in Phenylketonuria symptoms pictures. The severity of these manifestations is often directly correlated with the degree of phenylalanine accumulation in the brain and the duration of elevated levels.
Key observable symptoms that would be highlighted in visual documentation include:
Microcephaly: A smaller-than-normal head circumference, often noticeable in infants and young children, reflecting impaired brain growth and development due to neurotoxicity from high phenylalanine levels. This is a significant indicator in Phenylketonuria symptoms pictures.
Seizures: While the seizure activity itself is dynamic, the aftermath or a child’s posture during a seizure event can be depicted. Types of seizures can vary but often include tonic-clonic episodes, focal seizures, or infantile spasms, particularly in cases of severe, untreated PKU. The neurological impact is profound and contributes to the overall presentation in Phenylketonuria pictures.
Developmental Delay: Global developmental delay is a hallmark. Visually, this translates into children not meeting age-appropriate milestones. Phenylketonuria pictures might show an infant struggling to hold their head up, a toddler unable to walk independently, or an older child demonstrating difficulties with fine motor tasks such as grasping objects or drawing. These delays are critical for early identification.
Intellectual Disability: Ranging from mild to severe, this is the most devastating long-term consequence of untreated PKU. While not directly “visible” in a single image, the behavioral manifestations such as lack of engagement, repetitive movements, or difficulties with communication would be evident over time in a series of Phenylketonuria symptoms pictures.
Behavioral Problems: A wide array of behavioral disturbances can be observed. These include hyperactivity, irritability, aggression, and self-injurious behaviors (e.g., head-banging, scratching). Phenylketonuria pictures could capture instances of these challenging behaviors, which are a direct result of chronic neurological dysfunction.
Fair Skin, Hair, and Eyes (Hypopigmentation): Due to the impaired conversion of phenylalanine to tyrosine, which is a precursor to melanin (the pigment responsible for skin, hair, and eye color), individuals with PKU often have lighter pigmentation compared to their unaffected family members. This distinctive feature is frequently visible in Phenylketonuria symptoms pictures, showing unusually fair hair and light blue eyes.
Eczema-like Skin Rash: A common dermatological finding, characterized by dry, scaly, erythematous, and itchy patches. This is a very specific visual symptom and will be discussed in greater detail under “Skin rash Phenylketonuria Images.”
Postural Abnormalities: Untreated PKU can lead to spasticity and hypertonia, affecting muscle tone and control. This may result in unusual postures, such as scissoring of the legs or stiff limbs, evident in Phenylketonuria pictures.
The progression of Phenylketonuria symptoms is a dynamic process, and visual documentation plays a crucial role in understanding the impact of delayed diagnosis and inadequate management.
Signs of Phenylketonuria Pictures
Recognizing the specific signs of Phenylketonuria is paramount for prompt intervention, especially since early treatment can prevent the most severe neurological outcomes. Signs of Phenylketonuria pictures would often emphasize these observable characteristics that distinguish affected individuals from their unaffected peers. These signs are often the clinical indicators that prompt further investigation, leading to a diagnosis.
Detailed observable signs include:
Musty or Mousy Body Odor: This distinctive odor, described as musty, moldy, or mousy, is caused by the accumulation of phenylacetic acid, a byproduct of phenylalanine metabolism, in the urine, sweat, and breath. While not visually captured, its presence is a significant clinical sign that prompts immediate metabolic screening. An observant parent or clinician might note this characteristic odor.
Exaggerated Reflexes (Hyperreflexia): Neurological examinations in untreated individuals would show brisk reflexes. While not a standalone visual symptom, the clinician’s observation of this sign is critical for diagnosis. The physical manifestation of spasticity can be observed, affecting gait and movement patterns.
Tremors and Spasticity: Involuntary shaking (tremors) and increased muscle tone (spasticity) are common neurological signs. Signs of Phenylketonuria pictures might capture the involuntary movements of limbs or the rigid posture indicative of spasticity, particularly in older, untreated children.
Abnormal Gait: Affected individuals often develop an unsteady, shuffling, or broad-based gait due to neurological impairment and muscle rigidity. This characteristic walk is a significant observable sign in Phenylketonuria pictures.
Delayed Speech Development: Verbal communication delays are almost universal in untreated PKU. While not a direct visual sign, the inability to articulate words or form sentences at an appropriate age is a profound developmental delay that would be contextualized in longitudinal signs of Phenylketonuria pictures, showing limited interaction.
Postural Rigidity and Flexion: Chronic neurological damage can lead to a rigid posture, often with a tendency towards flexion, especially in the limbs. This can make movement difficult and contributes to the overall physical presentation of severe PKU.
Difficulty with Fine Motor Skills: Tasks requiring precision and coordination, such as writing, buttoning clothes, or picking up small objects, are significantly challenging. Signs of Phenylketonuria pictures might illustrate struggles with these everyday activities, highlighting the impact on daily functioning.
Photosensitivity: The hypopigmentation often associated with PKU can lead to increased sensitivity to sunlight, resulting in easier sunburns or heightened discomfort in bright light. While not a direct visual sign, an individual’s reaction to light exposure could be noted.
The constellation of these signs, particularly when observed together, provides compelling evidence for the presence of PKU, reinforcing the importance of diligent observation and timely medical investigation. Early recognition of these signs is crucial for preventing irreversible damage.
Early Phenylketonuria Photos
Early Phenylketonuria photos are particularly valuable as they capture the subtle indicators of the condition before significant, irreversible damage occurs. Newborn screening for PKU, which involves a simple heel prick blood test, has largely revolutionized the prognosis of this disorder, ensuring that most cases are identified within the first few days of life, often before any symptoms appear. However, in cases where screening is not performed or results are delayed, early symptoms may emerge.
In the absence of screening, the initial weeks and months of life might reveal subtle but crucial clues:
Apparent Normalcy at Birth: Most infants with PKU appear perfectly healthy at birth, making early Phenylketonuria photos of newborns indistinguishable from unaffected babies. This highlights the insidious nature of the disease and the critical role of newborn screening.
Subtle Feeding Difficulties: While not specific to PKU, some infants may experience mild feeding issues such as poor appetite or vomiting, which might be observed in early Phenylketonuria photos showing a less robust feeding response.
Increased Irritability: As phenylalanine levels begin to accumulate, some infants may become more irritable or fretful. This behavioral change, though non-specific, could be a subtle sign in early Phenylketonuria photos illustrating a fussy or unsettled infant.
Lack of Interest or Lethargy: Conversely, some infants may appear unusually quiet, listless, or less responsive to their environment. Early Phenylketonuria photos might depict an infant who is less engaged or interactive than expected for their age.
Delayed Milestones (Subtle): Before overt developmental delay becomes apparent, very subtle lags in milestones might be noticed. For instance, a slight delay in smiling, tracking objects, or achieving head control could be indicative, though challenging to discern definitively without specialized assessment. Early Phenylketonuria photos could attempt to capture these nuances.
Emergence of Hypopigmentation: Over the first few months, parents might notice that their baby’s skin and hair are becoming noticeably lighter than that of their siblings or parents. This is a crucial early visual cue. Early Phenylketonuria photos would distinctly show lighter hair color (e.g., blonde or light brown) and fair skin, contrasting with family traits.
First Appearance of Eczema: The characteristic dry, scaly skin rash often begins to manifest in the early months of life. Early Phenylketonuria photos could show the nascent stages of this rash on the face, scalp, or in the diaper area.
“Musty” Odor Becoming Apparent: While often subtle initially, the distinctive body odor can become more noticeable as the infant grows and phenylalanine levels remain elevated. This non-visual cue remains a significant indicator.
The collection of these early Phenylketonuria photos serves as a powerful educational tool, emphasizing that while symptoms may be subtle initially, they are progressive and warrant immediate medical attention. Early detection through newborn screening remains the gold standard for preventing severe outcomes.
Skin rash Phenylketonuria Images
The skin rash associated with Phenylketonuria is a distinct dermatological manifestation, often one of the earliest physical signs that can be observed in untreated infants and children. Visual documentation in skin rash Phenylketonuria images highlights the characteristic features of this condition. This rash is often described as an eczema-like dermatitis, and its presence, especially when combined with other PKU symptoms, can be a crucial diagnostic clue.
Detailed characteristics of the PKU skin rash typically observed in skin rash Phenylketonuria images include:
Eczematous Appearance: The rash closely resembles atopic dermatitis (eczema), making differential diagnosis important. It presents as dry, red (erythematous), inflamed patches of skin.
Scaly Patches: The affected skin often has a scaly texture, with fine, silvery, or whitish flakes indicative of skin barrier dysfunction and inflammation.
Pruritus (Itchiness): The rash is typically itchy, leading to scratching. Skin rash Phenylketonuria images might show signs of excoriation (scratch marks) or lichenification (thickening of the skin due to chronic scratching) in older cases.
Common Locations: The rash frequently appears in specific areas:
Face: Particularly on the cheeks, forehead, and around the mouth.
Scalp: Often mimicking cradle cap or seborrheic dermatitis, with greasy or dry scales.
Flexural Areas: Folds of the skin, such as the creases of the elbows (antecubital fossae) and knees (popliteal fossae).
Diaper Area: Can present as a persistent, difficult-to-treat diaper rash.
Trunk and Limbs: Less commonly, but can be seen scattered across the body.
Chronicity and Recurrence: Without proper dietary management of PKU, the rash tends to be chronic and recurrent, flaring up frequently. Skin rash Phenylketonuria images would showcase persistent or recurring dermatological issues.
Underlying Mechanism: The exact mechanism is not fully understood but is thought to be related to the metabolic imbalance in PKU. High phenylalanine levels can interfere with lipid metabolism and essential fatty acid pathways, which are critical for maintaining skin barrier integrity. This disruption can lead to a compromised skin barrier, making the skin more susceptible to irritation and inflammation.
Hypopigmentation of Affected Areas: Sometimes, the skin within the rash or after the rash has subsided may appear lighter than the surrounding skin, compounding the general hypopigmentation seen in PKU.
Secondary Infections: Due to scratching and a compromised skin barrier, the rash can become secondarily infected with bacteria (e.g.,
Staphylococcus aureus) or fungi, leading to crusting, weeping, or pustules. Skin rash Phenylketonuria images might show these complications.
Differentiating PKU-related eczema from common infantile eczema is crucial. While visually similar, the key distinction lies in the underlying metabolic cause. When a persistent or unusual eczema-like rash is observed, particularly in conjunction with other subtle signs like fair hair, delayed development, or a musty odor, Phenylketonuria should be considered in the differential diagnosis. Effective dietary treatment of PKU typically leads to a significant improvement or complete resolution of the skin rash, underscoring the metabolic origin.
Phenylketonuria Treatment
The treatment for Phenylketonuria is primarily centered on strict dietary management and, in some cases, pharmacological intervention, with the overarching goal of maintaining phenylalanine levels within a safe therapeutic range to prevent the devastating neurological and other systemic symptoms, including the visible ones detailed previously. Early initiation of treatment is critical for preventing irreversible intellectual disability and other associated problems. The aim is to normalize phenylalanine levels, thereby mitigating the progression of Phenylketonuria symptoms and improving long-term outcomes.
Key components of Phenylketonuria treatment include:
Lifelong Dietary Phenylalanine Restriction: This is the cornerstone of PKU management. The diet is extremely low in phenylalanine, which is an essential amino acid found in most protein-rich foods.
Special Formulas: Infants with PKU are given specialized, phenylalanine-free infant formulas. These provide all other essential amino acids, vitamins, minerals, and calories necessary for growth and development, without the harmful phenylalanine.
Restricted Natural Protein: Foods naturally high in protein, such as meat, fish, eggs, dairy products, nuts, seeds, and legumes, are severely restricted or eliminated. Even small amounts of these foods must be carefully measured.
Low-Protein Foods: The diet relies heavily on specially manufactured low-protein foods, including specific breads, pastas, and baked goods, to provide variety and meet caloric needs.
Phenylalanine-Free Medical Foods/Supplements: Older children and adults continue to consume medical foods and amino acid mixtures that are phenylalanine-free. These supplements ensure adequate protein and nutrient intake while adhering to phenylalanine limits.
Strict Monitoring: Regular blood tests are crucial to monitor phenylalanine levels, allowing dietitians and medical teams to adjust the diet as needed to maintain optimal levels. This monitoring is essential to prevent both high phenylalanine (leading to symptoms) and excessively low phenylalanine (which can cause other nutritional deficiencies).
Sapropterin Dihydrochloride (Kuvan): For some individuals with PKU, particularly those with milder forms or specific genetic mutations (often referred to as ‘BH4-responsive PKU’), sapropterin can be an effective adjunctive therapy.
Mechanism: Sapropterin is a synthetic form of tetrahydrobiopterin (BH4), a natural cofactor for the enzyme phenylalanine hydroxylase (PAH), which is deficient in PKU. In responsive individuals, sapropterin can enhance the residual activity of the PAH enzyme, helping to break down phenylalanine and lower blood levels.
Administration: It is an oral medication taken daily, often allowing for a more liberal dietary intake of phenylalanine, though dietary restrictions usually still apply to some extent.
Response Testing: Patients undergo a trial period to determine if they are responsive to sapropterin, as not all individuals with PKU benefit from this medication.
Pegvaliase (Palynziq): Approved for adults with PKU who have uncontrolled blood phenylalanine levels on current management.
Mechanism: Pegvaliase is an enzyme substitution therapy. It is a phenylalanine ammonia lyase (PAL) enzyme that helps break down phenylalanine directly, rather than relying on the deficient PAH enzyme.
Administration: It is administered by daily subcutaneous injections.
Side Effects: Can be associated with significant side effects, including hypersensitivity reactions, so careful monitoring and patient education are essential.
Gene Therapy and Enzyme Replacement Therapy (Investigational): Research is ongoing into more definitive treatments for PKU.
Gene Therapy: Aims to introduce a functional copy of the PAH gene into a patient’s cells, theoretically enabling the body to produce the missing enzyme.
Enzyme Replacement Therapy: Involves administering the PAH enzyme directly, potentially through infusion, to help metabolize phenylalanine.
These approaches hold promise for future PKU treatment, potentially reducing or eliminating the need for strict dietary control.
Multidisciplinary Care Team: Effective management of PKU requires a dedicated team of healthcare professionals, including:
Metabolic geneticist
Registered dietitian specialized in metabolic disorders
Neurologist
Psychologist/Neuropsychologist
Social worker
Nurse coordinator
Psychosocial Support: Living with PKU and adhering to a strict diet can be challenging for both patients and families. Access to psychological support, counseling, and patient advocacy groups is vital for long-term adherence and quality of life. Management of Phenylketonuria symptoms extends beyond just diet.
The effectiveness of Phenylketonuria treatment is overwhelmingly demonstrated by the dramatic improvement in patient outcomes since the advent of newborn screening and early dietary intervention. Children diagnosed and treated from infancy typically develop normally, with no or minimal cognitive impairment, showcasing how treatment effectively prevents the Phenylketonuria symptoms pictures previously described.