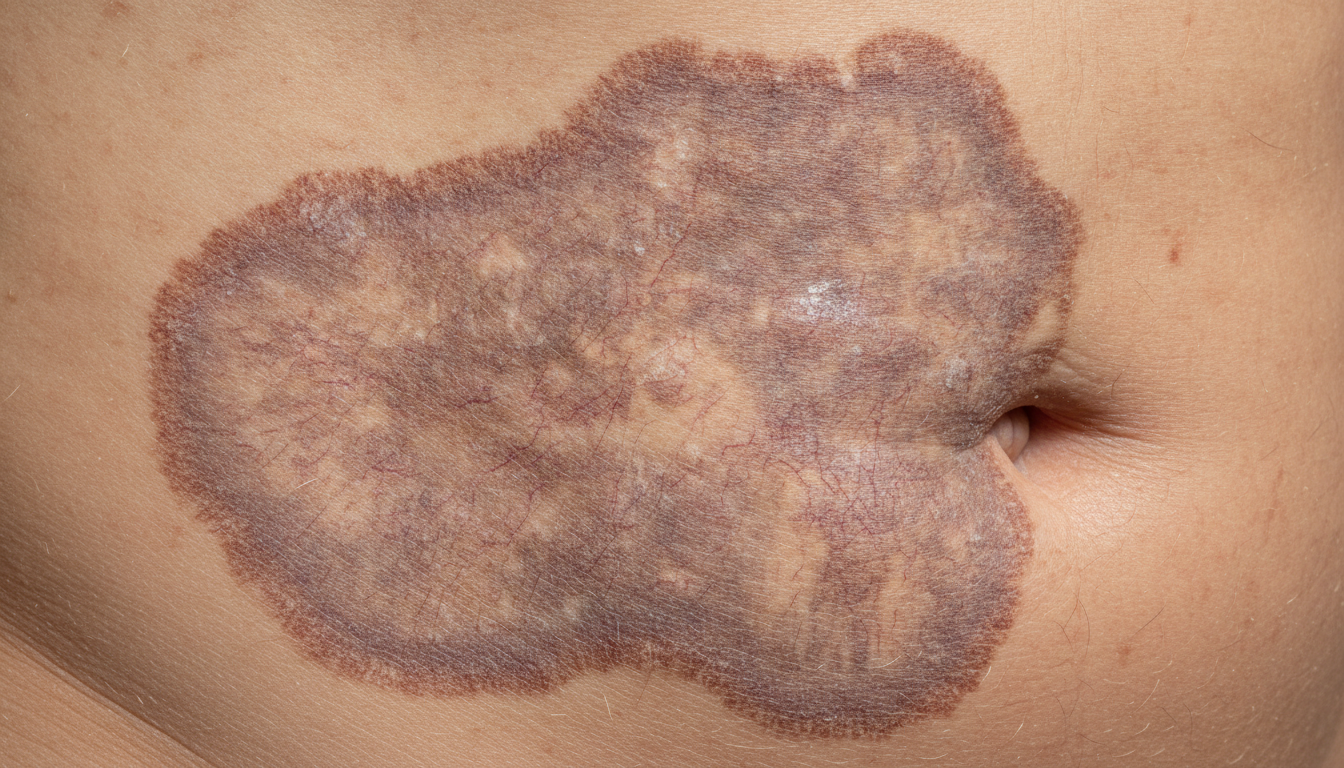
Understanding the visual characteristics of parapsoriasis is crucial for accurate identification and management. This article provides a detailed exploration of Parapsoriasis symptoms pictures, aiding in the recognition of its varied manifestations across different stages and subtypes.
Parapsoriasis Symptoms Pictures
The visual presentation of parapsoriasis is diverse, primarily categorized into small plaque parapsoriasis (SPP) and large plaque parapsoriasis (LPP). Recognizing these distinct parapsoriasis visual symptoms is key for dermatological assessment.
Small Plaque Parapsoriasis (SPP) typically presents with:
- Erythematous Macules and Patches: Often oval or finger-like (digitate) lesions, ranging from 0.5 cm to 5 cm in diameter. These are usually pink to red, sometimes with a yellowish or brownish hue, especially in individuals with darker skin tones.
- Fine, Wrinkled Scale: A characteristic feature is the presence of a delicate, often subtle, scale that can be difficult to appreciate without close inspection or scraping. This scale may give the surface a “cigarette paper” or “micaceous” appearance.
- Aymptomatic Nature: Most patients report minimal or no pruritus (itching), which can be a differentiating factor from other eczematous or pruritic dermatoses. The absence of significant itching is a common parapsoriasis symptom.
- Truncal and Proximal Limb Distribution: Lesions commonly appear on the trunk, particularly the back and abdomen, and on the proximal parts of the extremities. This distribution pattern is a significant clue in parapsoriasis photo analysis.
- Chronic Course: SPP lesions are persistent, often remaining stable for years or even decades without significant progression or regression, forming part of the chronic parapsoriasis rash pictures.
- Digitate Dermatosis Presentation: A common subtype of SPP, digitate dermatosis, manifests as elongated, finger-like plaques, often oriented along skin cleavage lines. These digitate parapsoriasis images show distinct linear patterns.
Large Plaque Parapsoriasis (LPP) exhibits more significant and often more concerning parapsoriasis skin manifestations:
- Large, Irregularly Shaped Plaques: Lesions are typically greater than 5 cm in diameter, often with irregular, geographic borders. They can coalesce to form extensive areas of affected skin.
- Poikilodermatous Changes: A hallmark of LPP is the development of poikiloderma within the plaques. This includes a triad of features:
- Reticulated Hypo- and Hyperpigmentation: Patchy areas of both lightening and darkening of the skin, creating a mottled appearance.
- Atrophy: Thinning of the epidermis, making the skin appear delicate and wrinkled, often described as “cigarette paper” atrophy. This atrophy is a critical parapsoriasis symptom picture element.
- Telangiectasias: Visible fine blood vessels (spider veins) within the plaques.
- Varied Erythema: The background color of LPP plaques can range from dull red to violaceous, sometimes with a brownish or purplish tint, contributing to the diverse parapsoriasis skin rash images.
- Mild or Absent Scaling: While scale can be present, it is often less prominent than in SPP and may be subtle or fine.
- Pruritus (Variable): Unlike SPP, LPP can sometimes be associated with mild to moderate itching, although severe pruritus is less common than in conditions like eczema.
- Potential for Transformation: LPP is considered a potential precursor to mycosis fungoides (MF), a form of cutaneous T-cell lymphoma. Therefore, close monitoring of LPP symptoms photos for evolving features is crucial.
- Common Locations: Similar to SPP, LPP often affects the trunk and proximal extremities, but can occur in more extensive or atypical locations.
Both types of parapsoriasis are chronic, and their dermatological appearance can fluctuate subtly over time. A thorough visual examination, often aided by dermoscopy, is essential for appreciating the nuances in parapsoriasis symptoms pictures.
Signs of Parapsoriasis Pictures
Delving deeper into the specific signs of parapsoriasis pictures allows for a more refined diagnostic approach. These signs often include subtle epidermal and dermal changes that, when viewed collectively, paint a clear clinical picture of the condition.
Key dermatological signs to look for in parapsoriasis images include:
- Erythema:
- Pink to Salmon-Colored Patches: Often the earliest and most consistent sign in both SPP and LPP, representing capillary dilation in the superficial dermis. The shade can vary depending on skin phototype and inflammation severity. These parapsoriasis erythema photos are fundamental.
- Dull Red to Violaceous Hues: In more chronic or advanced LPP, the color may deepen to a dull red, purplish, or violaceous tint, particularly in areas of poikiloderma or evolving MF.
- Scaling:
- Fine, Branny Scale: Typical of SPP, this scale is delicate and can be best visualized by gently scraping the lesion with a fingernail or tongue depressor. It often resembles very fine dandruff or a “cigarette paper” texture. This fine scale is a crucial parapsoriasis scaling sign.
- Pityriasiform Scale: Slightly coarser than branny scale, but still fine, appearing as small, loose flakes. Less common than in classic psoriasis.
- Absent or Scant Scale: In many LPP lesions, scaling may be minimal or entirely absent, contrasting with the more pronounced scale seen in other papulosquamous disorders. This lack of prominent scale is a diagnostic clue in LPP symptom pictures.
- Atrophy (primarily LPP):
- Epidermal Thinning: The skin within the plaque feels and appears thinner, often resembling fine crinkling or wrinkling, particularly when gently stretched. This atrophic parapsoriasis sign is highly indicative of LPP progression.
- Depressed or Sunken Appearance: In some instances, the atrophic areas may appear slightly depressed below the level of the surrounding healthy skin.
- Telangiectasias (primarily LPP):
- Visible Capillary Dilation: Fine, thread-like red lines representing dilated superficial blood vessels, often crisscrossing within the erythematous and atrophic areas. These telangiectatic parapsoriasis images are characteristic.
- Reticular Pattern: Telangiectasias may form a fine net-like pattern, contributing to the overall poikilodermatous appearance.
- Pigmentary Alterations (primarily LPP):
- Hypopigmentation: Areas of skin lightening, often irregularly shaped, within the plaques.
- Hyperpigmentation: Concomitant areas of increased pigmentation, appearing brownish or grayish. The combination of both is what creates the characteristic mottled poikilodermatous parapsoriasis skin signs.
- Livedo-like Changes: Sometimes, a faint, reticulated vascular pattern similar to livedo reticularis can be observed, although this is less common.
- Induration and Infiltration (suggests progression):
- Palpable Thickening: While parapsoriasis lesions are typically flat or only mildly infiltrated, the presence of significant thickening or induration (firmness to touch) within an LPP plaque is a red flag and suggests possible progression to MF. This requires urgent re-evaluation and biopsy. Infiltrated parapsoriasis pictures are serious.
- Lichenification: While not typical of parapsoriasis itself, chronic scratching (if pruritus is present) can lead to lichenification (skin thickening with exaggerated skin markings). However, primary parapsoriasis is usually not intensely pruritic.
- Distribution Patterns:
- Symmetry vs. Asymmetry: SPP lesions are often bilateral and symmetrical, whereas LPP can be more asymmetrical or localized.
- Truncal Predominance: Both types commonly affect the trunk (back, chest, abdomen) and proximal extremities, with facial, palmar, and plantar involvement being rare. Truncal parapsoriasis pictures are most common.
Careful examination of these detailed parapsoriasis signs in photos, combined with clinical history, is fundamental for accurate diagnosis and differentiation from other dermatological conditions.
Early Parapsoriasis Photos
Recognizing early parapsoriasis photos is vital for timely diagnosis and management, especially given the chronic nature and potential for transformation of large plaque variants. Initial lesions often present subtly, making early detection a clinical challenge that relies on keen observation of dermatological nuances.
In the earliest stages, parapsoriasis lesions may be mistaken for other common skin conditions, but distinct features emerge upon closer inspection:
- Faint Macules or Patches:
- Initial Erythema: The earliest manifestation is often a faint, ill-defined patch of erythema (redness). This can be a subtle pink or light red discoloration that is barely perceptible against the surrounding skin. These initial early parapsoriasis skin changes are often overlooked.
- Minimal Infiltration: At this stage, the lesion is typically non-palpable or only very faintly palpable, feeling almost flat.
- Absence of Significant Scale: Unlike many other papulosquamous conditions, significant scaling is usually absent in the very early phases. Any scale present is exceedingly fine and adherent.
- Developing Morphology (Small Plaque Parapsoriasis – SPP):
- Oval or Digitate Shapes: As SPP lesions mature slightly, they begin to assume their characteristic oval or finger-like (digitate) configurations. The early digitate parapsoriasis images show these elongated patterns.
- Sharper Delineation: The borders become somewhat more defined, though they often remain slightly indistinct rather than sharply demarcated.
- Subtle Wrinkling/Fine Scale Appears: A characteristic fine, cigarette paper-like wrinkling or very delicate scale may become apparent on the surface, requiring good lighting and close inspection. This is a crucial early sign in parapsoriasis lesion development.
- Asymptomatic Nature Persists: Early SPP is typically asymptomatic, with patients reporting no itching or discomfort, making it easy to miss unless specifically looking for skin changes.
- Nascent Plaques (Large Plaque Parapsoriasis – LPP):
- Larger, Irregular Erythematous Patches: LPP often begins as larger, more irregularly shaped erythematous patches compared to SPP. These can be several centimeters across from the outset. Early LPP photos show this expansive growth.
- Early Poikilodermatous Hints: Even in early LPP, there might be very subtle hints of poikiloderma, such as faint mottling of pigmentation or minute telangiectasias visible under dermoscopy, though pronounced atrophy is usually not present initially.
- Variable Pruritus: While not severe, some patients with early LPP may experience mild itching.
- Persistent and Non-Resolving: A key characteristic of both types, even in early stages, is the persistence of the lesions. They do not spontaneously resolve or respond quickly to mild topical treatments unless they are true inflammatory conditions. The unremitting nature is a key early parapsoriasis indicator.
- Common Initial Locations:
- Trunk Predominance: Both SPP and LPP often begin on the trunk (back, chest, abdomen), areas frequently covered by clothing, which can delay detection.
- Proximal Extremities: The upper arms and thighs are also common initial sites.
When examining early parapsoriasis photos, it’s important to consider the patient’s history, the duration of the lesions, and their response to previous treatments (or lack thereof). Biopsy is often necessary to confirm the diagnosis, especially for LPP, to rule out mycosis fungoides or other mimickers. The subtle nature of early parapsoriasis symptoms underscores the importance of a high index of suspicion.
Skin rash Parapsoriasis Images
The term “skin rash” for parapsoriasis refers to the characteristic eruption of patches and plaques that define the condition. Analyzing skin rash parapsoriasis images involves looking at the overall pattern, distribution, and individual lesion characteristics across the affected body surface. This section details the visual aspects of the parapsoriasis rash.
Key features of the parapsoriasis skin rash include:
- Distribution Patterns:
- Truncal Dominance: The rash overwhelmingly favors the trunk (back, chest, abdomen) and proximal extremities. This is a highly characteristic feature across both SPP and LPP, making truncal parapsoriasis rash photos the most common.
- Symmetry (SPP): Small plaque parapsoriasis often presents with a bilaterally symmetrical distribution of lesions, especially in digitate dermatosis, where finger-like lesions may be seen mirrored on both sides of the trunk.
- Asymmetry (LPP): Large plaque parapsoriasis can be more asymmetrical or localized to one large area, though it can also be widespread.
- Spared Areas: The rash typically spares the face, palms, soles, and flexural areas (skin folds), which helps differentiate it from conditions like atopic dermatitis or contact dermatitis. These parapsoriasis distribution patterns are diagnostically helpful.
- Individual Lesion Characteristics within the Rash:
- Erythematous Patches/Plaques: The fundamental units of the rash are often erythematous (red) patches or slightly elevated plaques. The color can vary from light pink to dull red or violaceous, impacting the overall parapsoriasis rash appearance.
- Variable Scaling:
- Fine, Branny Scale (SPP): As noted, SPP lesions often have a very fine, subtle scale that gives a wrinkled or “cigarette paper” texture. This fine scaling contributes to the unique look of SPP rash pictures.
- Scant or Absent Scale (LPP): LPP lesions within the rash often have minimal to no visible scale, which can sometimes lead to misdiagnosis as a simple erythematous patch.
- Poikilodermatous Features (LPP): In the context of an LPP rash, individual plaques will exhibit the characteristic triad of atrophy, telangiectasias, and dyspigmentation (hypo- and hyperpigmentation). These features create a mottled, thin-skinned appearance crucial for identifying LPP rash images.
- Well-Defined vs. Ill-Defined Borders: SPP lesions tend to have fairly distinct, though not always sharp, borders. LPP lesions often have more irregular, geographic, or serpiginous (wavy) borders that can merge with surrounding skin.
- Lack of Significant Induration: Generally, the rash of parapsoriasis is not significantly thickened or indurated. Any substantial infiltration within a plaque, particularly in LPP, warrants concern for progression to MF.
- Chronic and Persistent Nature:
- Long-Standing Eruption: A defining characteristic is the chronicity of the rash. It persists for months, years, or even decades without spontaneous resolution. Patients often report having the parapsoriasis skin eruption for a very long time.
- Resistant to Conventional Treatments: The rash typically does not respond well to simple topical anti-inflammatory creams like emollients or mild corticosteroids, further differentiating it from eczematous rashes. This resistance is a diagnostic clue in chronic parapsoriasis rash cases.
- Asymptomatic or Mildly Pruritic:
- Lack of Severe Itching: For the most part, the parapsoriasis rash is asymptomatic or only mildly itchy. This contrasts sharply with intensely pruritic conditions such as eczema, urticaria, or scabies.
- Secondary Changes from Scratching are Rare: Due to the lack of severe pruritus, secondary excoriations, lichenification, or impetiginization are uncommon unless there’s a co-existing condition or very sensitive skin. This preserves the primary parapsoriasis lesion morphology.
- Digitate Dermatosis Specifics:
- Finger-like Lesions: As a distinct form of SPP, digitate dermatosis presents with elongated, often parallel, finger-like patches oriented along skin cleavage lines, especially on the flanks. These digitate parapsoriasis rash images are unmistakable.
- Yellowish-Brown Hue: These lesions can sometimes have a slightly yellowish or brownish tint in addition to erythema.
When reviewing skin rash parapsoriasis images, it’s crucial to look beyond individual lesions and appreciate the entire clinical presentation, including the number of lesions, their size range, and their overall arrangement on the body. This holistic view enhances diagnostic accuracy of parapsoriasis skin conditions.
Parapsoriasis Treatment
While the focus of this article is on parapsoriasis symptoms pictures, understanding treatment approaches is essential as they aim to manage or clear these visible lesions. The choice of parapsoriasis treatment depends heavily on the type (small plaque vs. large plaque), disease extent, patient symptoms, and the risk of progression, particularly for LPP. The primary goal is to improve the appearance of parapsoriasis skin and alleviate any associated discomfort.
Treatment for Small Plaque Parapsoriasis (SPP):
Given its benign nature and typically asymptomatic course, SPP often requires less aggressive intervention. Treatment strategies for SPP lesions focus on reducing redness and subtle scaling.
- Observation: For entirely asymptomatic and stable SPP, especially digitate dermatosis, a “watch and wait” approach with regular follow-ups may be sufficient. This is often the first step in managing mild parapsoriasis.
- Topical Corticosteroids:
- Medium to High Potency: Applied once or twice daily for a limited duration (e.g., 2-4 weeks) can help reduce erythema and fine scale. Examples include triamcinolone acetonide or clobetasol propionate. This helps to improve the visual symptoms of parapsoriasis.
- Maintenance Therapy: Intermittent application or use of lower potency steroids for longer periods may be needed for persistent areas.
- Topical Calcineurin Inhibitors (TCIs):
- Pimecrolimus or Tacrolimus: These can be effective for reducing inflammation and are steroid-sparing, useful for long-term management, especially in sensitive areas, though not typically the main sites of SPP. They can help clear parapsoriasis plaques.
- Phototherapy:
- Narrow-band UVB (nbUVB): Considered a first-line therapy for more widespread or persistent SPP that doesn’t respond to topicals. Treatments are typically administered 2-3 times per week over several weeks to months. nbUVB is highly effective in clearing the parapsoriasis rash and improving skin texture.
- Broad-band UVB (bbUVB): Less commonly used than nbUVB due to a higher risk of side effects.
- PUVA (Psoralen plus UVA): Oral psoralen followed by UVA light exposure. Can be effective but is associated with more side effects (nausea, photosensitivity, increased skin cancer risk) and is usually reserved for recalcitrant cases. The goal is complete resolution of visible parapsoriasis lesions.
Treatment for Large Plaque Parapsoriasis (LPP):
LPP treatment is more proactive due to the potential risk of progression to mycosis fungoides (MF). The goal is to clear the lesions, prevent progression, and monitor for changes in the parapsoriasis skin appearance.
- Phototherapy (First-Line):
- Narrow-band UVB (nbUVB): Often the first choice for widespread LPP. It is very effective in clearing plaques and improving associated poikiloderma. Regular treatments (2-3 times/week) are usually required until clearance, followed by maintenance. Monitoring for LPP lesion resolution is key.
- PUVA: Also highly effective for LPP, especially thicker plaques or those resistant to nbUVB. Given the risks, careful patient selection and monitoring are paramount. Both nbUVB and PUVA aim to halt the progression of the parapsoriasis rash.
- Topical Corticosteroids:
- High to Super High Potency: Can be used for localized LPP, especially for symptom control or in conjunction with phototherapy. Long-term use requires careful monitoring for side effects like skin atrophy, which could worsen the inherent atrophy of LPP. These help reduce the inflammation visible in LPP photos.
- Topical Nitrogen Mustard (Mechlorethamine) or Carmustine (BCNU):
- Chemotherapeutic Agents: These agents are used for their direct effect on T-cells in the skin. They are particularly relevant when LPP shows histological features suggestive of early MF or when phototherapy is insufficient. They can induce remission in pre-mycotic parapsoriasis lesions.
- Application: Applied daily to affected areas. Side effects include irritation, contact dermatitis, and pigmentation changes.
- Topical Retinoids (e.g., Tazarotene):
- Anti-proliferative Effects: Can be used off-label for LPP, particularly for plaques with some epidermal thickening, often in combination with corticosteroids. They help normalize epidermal cell growth and improve parapsoriasis skin texture.
- Systemic Treatments (Rarely for pure LPP, but considered if evolving to MF):
- Methotrexate: Low-dose methotrexate may be considered for widespread, recalcitrant LPP or if there is concern for very early MF.
- Oral Retinoids (e.g., Acitretin, Bexarotene): Can be effective, especially for more advanced or refractory cases of LPP with MF features.
- Interferon-alpha: Another option for difficult-to-treat cases or as adjunctive therapy in early MF.
- Regular Monitoring and Biopsies:
- Lifelong Follow-up: Patients with LPP require lifelong dermatological surveillance due to the risk of transformation into MF. This includes regular skin exams, clinical photography (for progression of parapsoriasis symptoms pictures), and repeat biopsies of any changing or suspicious lesions (e.g., new nodules, increased induration, ulceration, or severe pruritus). This vigilant approach is critical for LPP management.
For both types of parapsoriasis, patient education about the chronic nature of the condition and the importance of adherence to treatment and follow-up is paramount. Sun protection is also crucial, especially for those undergoing phototherapy or with poikilodermatous changes in LPP, to prevent exacerbation and reduce skin cancer risk. The goal of all parapsoriasis treatment modalities is to achieve and maintain clearance of the visible symptoms, ensuring the best possible parapsoriasis patient outcome.