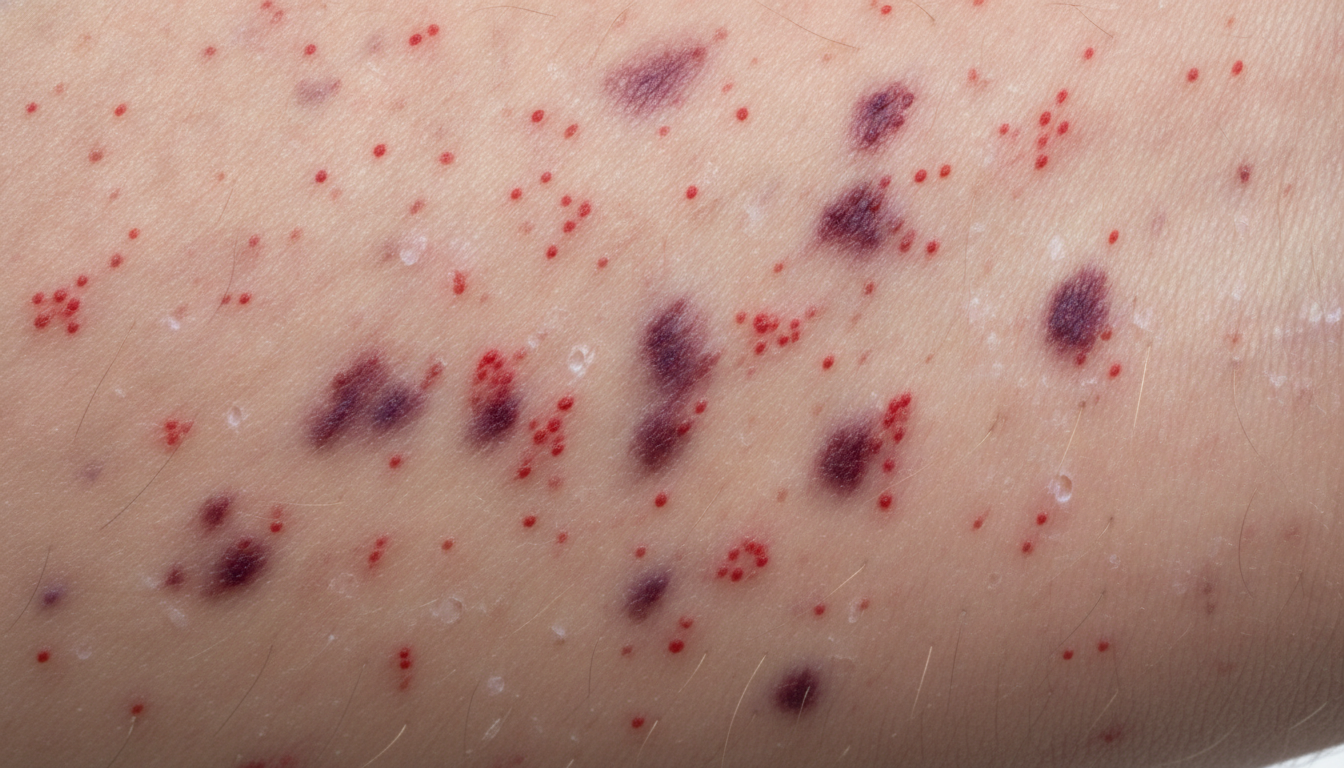
When confronted with potential neurological infections, recognizing visual cues is paramount. This article aims to provide a comprehensive guide to understanding `Meningitis symptoms pictures`, focusing on the observable physical manifestations that can signal this life-threatening condition, urging immediate medical intervention. Early identification through visual assessment is critical for prompt diagnosis and effective treatment.
Meningitis Symptoms Pictures
Identifying the visual indicators of meningitis is a critical first step towards securing timely medical intervention. While many symptoms are internal or subjective, certain presentations can be captured in `Meningitis symptoms pictures`, providing crucial clues for healthcare professionals and raising awareness for the public. The overall appearance of a person with meningitis can reflect severe illness, ranging from subtle discomfort to profound neurological distress. Understanding these visual signs can significantly impact outcomes, especially in cases of rapidly progressing bacterial meningitis.
Key observable symptoms and their visual implications often include:
- Altered Mental Status: Patients may appear confused, disoriented, or lethargic. Their gaze might be unfocused, or they might respond slowly to stimuli. In severe cases, they could be unresponsive or comatose, observable through their posture and lack of interaction.
- Photophobia (Sensitivity to Light): A person experiencing photophobia will often squint, turn away from light sources, or prefer to be in dim lighting. Their facial expression might show discomfort or pain when exposed to bright lights.
- Headache: While a headache itself isn’t directly ‘pictured’, the patient’s demeanor can reflect severe pain. They might be clutching their head, grimacing, or appearing restless and unable to find a comfortable position. In infants, incessant crying and irritability, often accompanied by arching of the back, can be visual indicators of severe head pain.
- Neck Stiffness (Nuchal Rigidity): This is a classic sign of meningitis. Visually, a patient may struggle to touch their chin to their chest. Attempts to flex the neck passively might cause pain, leading to resistance, an arching of the back, or an inability to move the head freely, which can be captured in a series of `meningitis symptom photos`.
- Vomiting: Projectile vomiting, though transient, can be a dramatic visual symptom. The presence of vomit, especially without nausea, can be a concerning sign, indicating increased intracranial pressure. Dehydration signs like sunken eyes or dry mucous membranes might also be visually apparent following repeated vomiting episodes.
- Fever: While a fever isn’t strictly visual, its accompanying signs are. A flushed face, sweating, shivering, or a generally unwell, hot appearance can suggest a high body temperature. In children, a fever often makes them appear lethargic or unusually quiet.
- Seizures: Convulsive seizures are clear, dramatic visual events. These involve uncontrolled jerking movements of the limbs, body stiffening, loss of consciousness, and sometimes frothing at the mouth or incontinence. Even non-convulsive seizures can manifest as subtle staring spells or minor twitching, which can be seen in `meningitis attack pictures`.
- Irritability (especially in infants and young children): Visually, an irritable infant might cry inconsolably, be difficult to comfort, refuse feeding, or show unusual fussiness. They might arch their back or have a high-pitched cry.
- Bulging Fontanelle (in infants): The soft spot on an infant’s head may appear visibly swollen or tense due to increased intracranial pressure. This is a critical visual sign in very young children, signifying serious underlying pathology.
These `meningitis symptoms pictures` represent a spectrum of visual cues that, when observed, should prompt immediate medical evaluation. The absence of a rash does not rule out meningitis, as not all forms of the disease present with skin lesions, particularly viral meningitis or early stages of bacterial forms. However, the presence of any of these visual indicators, especially in combination, necessitates urgent medical attention.
The severity and combination of these visual symptoms can vary based on the type of meningitis (bacterial, viral, fungal), the patient’s age, and their overall health status. For instance, bacterial meningitis often presents with a more acute and severe onset of symptoms compared to viral meningitis, which might mimic a flu-like illness initially.
Other general signs of severe illness that might be visually apparent in `meningitis emergency pictures` include:
- Pale or mottled skin: A grayish or patchy discoloration of the skin, indicating poor circulation.
- Cold hands and feet: Even with a high fever, extremities might feel cold to the touch.
- Rapid breathing or difficulty breathing: Observable as shallow, quick breaths, or visible effort during respiration.
- Limpness or floppiness (in infants): An infant might appear unusually listless, with poor muscle tone.
- Unusual skin color changes: Beyond rashes, this could include cyanosis (bluish discoloration) of the lips or nail beds, indicating oxygen deprivation.
Each of these visual cues underscores the critical importance of being able to recognize the potential presence of meningitis and to seek professional medical help without delay. Early `meningitis detection pictures` can guide immediate diagnostic efforts and treatment plans.
Signs of Meningitis Pictures
Beyond general symptoms, there are specific clinical `signs of meningitis pictures` that healthcare providers look for, many of which have visual or observable components. These signs are often elicited during a physical examination but can sometimes be inferred from a patient’s spontaneous posture or reactions. Recognizing these particular signs, even through observational cues, is vital for a comprehensive assessment of potential meningeal irritation.
Key observable signs that may appear in `meningitis clinical pictures` include:
- Nuchal Rigidity: As mentioned, this is a cardinal sign. In `meningitis diagnosis pictures`, a patient might be seen lying stiffly, unable to flex their head forward without extreme pain, or even resisting the movement entirely. This rigidity results from inflammation of the meninges surrounding the spinal cord and brain.
- Kernig’s Sign: This sign is assessed by having the patient lie supine, then flexing the hip to 90 degrees and extending the knee. In meningitis, this maneuver causes resistance and pain in the hamstring, which the patient visually manifests through grimacing, guarding, or refusing to allow the leg to be straightened. The inability to fully extend the leg beyond a certain angle (e.g., 135 degrees) due to spasm of the hamstring muscles is the visual indicator.
- Brudzinski’s Sign: This sign is assessed by passively flexing the patient’s neck towards their chest. If meningitis is present, this action will cause an involuntary flexion of the hips and knees. This reflex movement is a clear visual indicator of meningeal irritation, where the patient’s legs automatically draw up in response to the neck flexion. `Brudzinski’s sign images` would show this characteristic leg movement.
- Photophobia (Exaggerated Light Aversion): While a symptom, it’s also a sign elicited upon exposure to light. The patient’s intense squinting, turning away, or shielding of eyes demonstrates the severity of light sensitivity, often more pronounced than typical discomfort.
- Altered Level of Consciousness: This can range from drowsiness and lethargy (slow responses, drooping eyelids) to stupor (requiring vigorous stimulation to respond) or coma (no response to stimuli). These states are visibly apparent through the patient’s lack of interaction, eye movements, and general responsiveness, critical elements in `meningitis patient pictures`.
- Cranial Nerve Palsies: Inflammation and pressure can affect cranial nerves, leading to observable impairments. These might include:
- Ocular palsies: Visible deviation of the eyes (strabismus), inability to move eyes in certain directions, or drooping eyelids (ptosis).
- Facial nerve palsy: One side of the face may appear droopy, or the patient might be unable to smile symmetrically.
- Pupillary abnormalities: Pupils might be unequal in size (anisocoria) or react sluggishly to light, visually detectable.
- Hydrocephalus (in severe cases): In infants, the head circumference may increase rapidly, and the fontanelles may bulge significantly due to cerebrospinal fluid accumulation. This visible enlargement of the head is a late but critical sign.
- Posturing: In severe neurological compromise, patients may exhibit decorticate (arms flexed to chest, legs extended) or decerebrate (arms and legs extended, wrists rotated outward) posturing. These are distinct and alarming visual signs of severe brainstem dysfunction.
- Opisthotonos: A severe hyperextension and spasticity in which the head, neck, and spinal column are thrown backward. This extreme arching of the back is a dramatic visual sign, often associated with severe meningitis, particularly in infants.
These specific `signs of meningitis pictures` provide more definitive indicators of meningeal irritation and neurological involvement compared to general symptoms. Their presence, especially in conjunction with other symptoms, strongly suggests a diagnosis of meningitis and warrants immediate advanced medical evaluation, including diagnostic procedures like a lumbar puncture. Medical professionals are trained to elicit these signs systematically, but understanding what they look like can help families and caregivers recognize urgent situations. The visual recognition of these signs can expedite the diagnostic process, which is crucial for conditions like bacterial meningitis where every hour counts for effective treatment and improved prognosis.
The progression of these signs is also important. What might begin as subtle neck stiffness can rapidly evolve into pronounced nuchal rigidity or the appearance of Kernig’s and Brudzinski’s signs. Documenting these changes, potentially through serial `meningitis progression photos`, can provide invaluable information to the medical team. In a clinical setting, nurses and doctors will continuously monitor for these evolving visual clues, understanding their implications for the patient’s neurological status and the urgency of the situation.
Early Meningitis Photos
Recognizing `Early Meningitis Photos` can be exceptionally challenging, as initial symptoms are often non-specific and mimic common viral infections like the flu. However, understanding these subtle early visual cues is crucial for prompt diagnosis, particularly since meningitis can progress rapidly and lead to severe complications or death if not treated quickly. The distinction between a common illness and early meningitis often lies in the severity and progression of symptoms, as well as the presence of certain red flags.
Visual manifestations in the early stages might include:
- General Malaise and Lethargy: The individual may appear unusually tired, lacking energy, and generally unwell. Their movements might be slow, and they might seem disinterested in their surroundings. In infants, this could manifest as increased sleepiness, difficulty waking, or a noticeable decrease in activity.
- Irritability and Fussiness: Especially in children, a noticeable increase in irritability, inconsolable crying, or persistent fussiness without an obvious cause can be an early red flag. This can be visually evident in their facial expressions and restless movements.
- Poor Feeding/Appetite: Infants might refuse to feed, or older children and adults may lose their appetite. This can be visually suggested by a general disinterest in food or drink, or by a visible decrease in intake.
- Mild Photophobia: An early aversion to bright lights might be subtle, with the individual turning away or seeking dimmer environments without explicitly stating pain or discomfort. Their eyes might appear strained or watery in bright conditions.
- Subtle Neck Stiffness: Initially, neck stiffness might not be pronounced enough to elicit Kernig’s or Brudzinski’s signs. However, the individual might complain of a stiff neck or move their head cautiously. This subtle discomfort, often mistaken for a muscle strain, can be observed in their limited range of motion or guarded movements.
- Flushed Appearance/Sweating: Early fever can cause the face to appear flushed, and the individual might be noticeably sweating, even in a cool environment. These are visual indications of the body’s febrile response.
- Pale or Dull Complexion: Conversely, some individuals, especially in early stages of severe infection, might develop an unusual paleness or a grayish, dull complexion, indicating systemic illness.
- Vomiting without Diarrhea: Early vomiting, especially projectile vomiting, without accompanying diarrhea or other gastrointestinal symptoms, can be a warning sign. The visual evidence of vomiting can be a critical prompt for concern.
- Non-Specific Rash: While the characteristic non-blanching rash is a later and more serious sign, some individuals might develop a faint, non-specific rash in the early stages. This could be a viral rash that is blanching, but any new rash in conjunction with other symptoms should be noted and monitored.
- Increased Sensitivity: Patients might appear unusually sensitive to touch or noise, flinching or reacting strongly to stimuli that would normally be tolerated. This heightened sensitivity can be visually observed in their reactions.
The challenge with `early meningitis photos` is that these symptoms are common to many less serious conditions. However, the key differentiator is often the rapid progression or the unusual severity of these symptoms. For example, a headache that becomes progressively worse and is unresponsive to common pain relievers, or lethargy that deepens over a few hours, should raise alarms. The sudden onset of these symptoms, especially in an otherwise healthy individual, should prompt immediate medical evaluation.
In infants and young children, early `meningitis symptom photos` are particularly difficult to interpret due to their limited ability to communicate. Parents and caregivers should look for changes in behavior, feeding patterns, and general responsiveness. A usually active child becoming unusually quiet and still, or an infant whose cries are unusually high-pitched and persistent, are visual cues that require urgent attention.
It is important to emphasize that early recognition, even based on subtle visual cues, can be life-saving. If there is any suspicion of meningitis, especially if symptoms are worsening rapidly, medical advice should be sought immediately. Do not wait for the more severe or characteristic symptoms like the full-blown rash or profound neck stiffness to develop. Timeliness in seeking care based on `initial meningitis signs` can dramatically improve prognosis and reduce the risk of long-term complications.
Detailed monitoring of these `early meningitis warning signs` and their progression is crucial. Keeping a log of when symptoms started, their severity, and any changes can be invaluable information for healthcare providers. For instance, observing a child’s increasing difficulty in maintaining eye contact or a gradual decrease in their playful interactions can be critical visual indicators that warrant concern.
- Changes in Body Temperature: Fluctuations in body temperature, sometimes alternating between high fever and chills, can make an individual appear distressed, with visible shivering or flushed skin.
- Unusual Crying Patterns: In infants, a moaning cry, a high-pitched cry, or a cry that is continuous and unconsolable should be considered a serious visual and auditory warning.
- Lack of Engagement: A child who normally interacts and plays, but becomes withdrawn, stares blankly, or shows little interest in their surroundings, presents a strong visual signal of potential neurological distress.
The aim is to catch meningitis before it becomes overtly severe, by carefully observing and interpreting these early, sometimes ambiguous, `early meningitis photos` and symptoms. Public health campaigns often highlight these early signs to empower individuals and families to seek help promptly.
Skin rash Meningitis Images
The presence of a distinctive skin rash is one of the most serious and visually striking `Meningitis Images`, particularly associated with `bacterial meningitis`, specifically `meningococcal meningitis` (caused by Neisseria meningitidis). This rash is a critical warning sign and requires immediate emergency medical attention. The characteristic rash is non-blanching, meaning it does not fade or disappear when pressure is applied to it. This is due to bleeding under the skin. Visualizing and understanding the progression of this rash through `skin rash meningitis images` is crucial for rapid identification.
The progression and appearance of the meningitis rash:
- Petechiae: These are the earliest and smallest form of the characteristic rash.
- Appearance: Tiny, pinprick-sized spots (1-2 mm in diameter), usually red or purple. They can resemble flea bites initially.
- Location: Often first appear on the trunk, lower limbs, or mucous membranes (e.g., inside the mouth, on the conjunctiva of the eyes). They can be easily missed if not specifically looked for.
- Non-blanching: This is the key distinguishing feature. To test, press a clear glass or tumbler firmly against the rash. If the spots remain visible and do not fade under pressure, it is a non-blanching rash, indicating bleeding into the skin. This is the `glass test for meningitis rash`.
- Significance: Petechiae indicate capillary damage and leakage of blood, a sign of severe systemic infection (septicemia or meningococcemia).
- Purpura: As the illness progresses, petechiae can coalesce and enlarge into larger patches.
- Appearance: Larger, bruise-like purple or reddish-brown lesions (3 mm to several centimeters in diameter). They can have irregular shapes and borders.
- Progression: Purpura are essentially larger areas of subcutaneous hemorrhage. They often signify worsening coagulopathy and more extensive bleeding under the skin.
- Non-blanching: Like petechiae, purpuric lesions are also non-blanching when the `tumbler test` is applied.
- Significance: Widespread purpura is a sign of severe meningococcal septicemia, often indicating disseminated intravascular coagulation (DIC), a life-threatening complication.
- Ecchymoses: In the most severe cases, the skin lesions can develop into very large, irregular bruising-like patches.
- Appearance: Large areas of purple or black discoloration, resembling deep bruises. These lesions can sometimes be raised.
- Progression: Ecchymoses represent extensive bleeding under the skin and are often associated with tissue necrosis and severe organ damage.
- Significance: Indicates profound septic shock and is a critical `meningitis rash warning sign`.
The `skin rash meningitis images` are crucial for public awareness. It is important to note that:
- Not all meningitis cases have a rash: Viral meningitis rarely causes a rash, and even bacterial meningitis may not present with a rash in all cases (especially non-meningococcal bacterial meningitis or early stages). The absence of a rash does not rule out meningitis.
- Rapid Progression: The rash can appear and spread very quickly, sometimes within hours. What starts as a few faint petechiae can rapidly become widespread purpura. This rapid progression is a critical visual alarm.
- Location of Rash: While common on the trunk and limbs, the rash can appear anywhere on the body, including the face, palms of the hands, and soles of the feet. Examining the entire body, especially in areas not typically exposed, is important.
- Color Variation: The rash can vary in color from bright red to deep purple or almost black, depending on the amount of bleeding and its duration.
Performing the `Glass Test (Tumbler Test)` for `meningitis rash identification` is a simple yet crucial visual assessment:
- Find a clear glass or tumbler.
- Press the side of the glass firmly against one of the spots or rashes on the skin.
- Observe if the spot fades or disappears when pressed.
- If the spot remains clearly visible and does not fade under the pressure of the glass, it is a non-blanching rash and is indicative of bleeding under the skin.
- This result, especially in conjunction with other meningitis symptoms, warrants immediate emergency medical attention.
Other potential skin manifestations that might be seen in `meningitis images` but are less specific to the characteristic rash:
- Pallor: Extreme paleness of the skin due to reduced blood flow or anemia, often associated with shock.
- Mottling: A patchy, marble-like discoloration of the skin, typically seen in severe shock or hypothermia, indicating poor perfusion.
- Cyanosis: A bluish discoloration of the skin and mucous membranes (especially lips, fingers, toes) due to low oxygen levels in the blood, indicating severe respiratory or circulatory compromise.
The development of any non-blanching rash, particularly if accompanied by other symptoms like fever, headache, neck stiffness, or altered mental status, should be considered a medical emergency. Do not delay seeking help. `Meningitis rash photos` serve as a stark reminder of the urgency required.
Meningitis Treatment
While `Meningitis Treatment` does not involve pictures, understanding the immediate and comprehensive medical interventions is crucial, as it underscores the life-threatening nature of the disease and the critical importance of early visual symptom recognition. Prompt and aggressive treatment significantly improves outcomes and reduces mortality and long-term complications. The approach to treatment varies depending on the cause of meningitis (bacterial, viral, fungal), but the initial management often involves supportive care and empiric therapy until a definitive diagnosis is made.
Immediate Medical Emergency
Meningitis, especially bacterial meningitis, is a medical emergency. Any suspicion based on `Meningitis symptoms pictures` or other clinical signs warrants an immediate trip to the emergency room. Delaying treatment by even a few hours can lead to severe consequences, including brain damage, hearing loss, learning disabilities, limb amputation, or death.
Diagnosis and Initial Steps
Upon arrival at the hospital, rapid diagnosis is prioritized. This typically involves:
- Medical History and Physical Examination: Assessing symptoms, looking for visual signs like rashes, neck stiffness, and neurological deficits.
- Blood Tests: To check for signs of infection (e.g., elevated white blood cell count), inflammation, and other abnormalities. Blood cultures are taken to identify the causative bacteria.
- Lumbar Puncture (Spinal Tap): This is the definitive diagnostic test. A sample of cerebrospinal fluid (CSF) is collected from the spinal canal and analyzed for:
- White blood cell count and differential (high count, predominant neutrophils suggest bacterial).
- Protein levels (elevated in bacterial and fungal).
- Glucose levels (low in bacterial and fungal).
- Presence of bacteria (Gram stain, culture).
- Viral PCR (Polymerase Chain Reaction) for viral meningitis.
- CT Scan or MRI: May be performed before a lumbar puncture if there are signs of increased intracranial pressure or focal neurological deficits, to rule out brain swelling or other space-occupying lesions.
Treatment Based on Type of Meningitis
1. Bacterial Meningitis Treatment
This is the most severe form and requires immediate, aggressive treatment. The cornerstone of `bacterial meningitis treatment` is antibiotics.
- Intravenous Antibiotics:
- Empiric Therapy: Broad-spectrum antibiotics are started immediately, even before the specific bacteria are identified from cultures. Common choices include ceftriaxone, vancomycin, and ampicillin (especially for neonates or the elderly).
- Targeted Therapy: Once the causative bacteria are identified, antibiotics may be adjusted to a more specific and effective agent. Treatment duration typically ranges from 7 to 21 days, depending on the bacteria.
- Corticosteroids (Dexamethasone): Often administered with the first dose of antibiotics, especially in cases of suspected pneumococcal meningitis. Dexamethasone helps reduce inflammation and swelling around the brain, thereby minimizing complications like hearing loss and neurological damage.
- Supportive Care:
- Fluid Management: To maintain hydration and blood pressure, but carefully monitored to avoid exacerbating cerebral edema.
- Management of Intracranial Pressure: Measures to reduce brain swelling, such as head elevation, osmotic agents (e.g., mannitol), or in severe cases, ventriculostomy to drain CSF.
- Seizure Control: Anticonvulsant medications (e.g., lorazepam, phenytoin) if seizures occur.
- Respiratory Support: Oxygen therapy or mechanical ventilation if respiratory distress or coma develops.
- Pain and Fever Management: Analgesics and antipyretics to improve comfort.
2. Viral Meningitis Treatment
Often milder than bacterial meningitis, `viral meningitis management` typically involves supportive care as there is no specific cure for most viral causes (e.g., enteroviruses).
- Rest: Plenty of rest helps the body fight off the infection.
- Pain Relievers: Over-the-counter medications like ibuprofen or acetaminophen for headache and fever.
- Fluids: To prevent dehydration.
- Antiviral Medications: In specific cases, if the viral cause is identifiable and treatable (e.g., herpes simplex virus, for which acyclovir can be used). These are less commonly needed.
- Hospitalization: May be required for close monitoring, especially in infants or immunocompromised individuals, or if symptoms are severe.
3. Fungal Meningitis Treatment
This is rare and occurs predominantly in individuals with compromised immune systems. `Fungal meningitis treatment` involves long courses of high-dose antifungal medications.
- Antifungal Medications: Intravenous antifungals like amphotericin B, often combined with flucytosine or fluconazole. Treatment can last for several weeks to months, or even longer, depending on the specific fungus and the patient’s immune status.
- Surgical Intervention: In some cases, surgical removal of fungal lesions or shunting to relieve hydrocephalus may be necessary.
4. Other Types of Meningitis Treatment
- Parasitic Meningitis: Specific anti-parasitic drugs are used, depending on the identified parasite.
- Non-Infectious Meningitis: Treatment focuses on the underlying cause (e.g., autoimmune disease, cancer) and may involve corticosteroids or immunosuppressants.
Prevention and Prophylaxis
`Prevention of meningitis` is a crucial aspect of public health. This includes:
- Vaccinations:
- Hib vaccine: Protects against Haemophilus influenzae type b.
- Pneumococcal vaccines: Protect against Streptococcus pneumoniae.
- Meningococcal vaccines: Protect against Neisseria meningitidis (various serogroups).
- Hygiene Practices: Regular hand washing, especially during cold and flu season, helps prevent the spread of viral meningitis.
- Prophylaxis (Post-exposure Treatment): For close contacts of individuals diagnosed with bacterial meningitis, especially meningococcal or Hib meningitis, antibiotics (e.g., rifampin, ciprofloxacin) may be prescribed to prevent them from developing the disease. This is a critical public health measure.
The severity of meningitis demands that symptoms, particularly those visible through `Meningitis symptoms pictures`, are not underestimated. Quick recognition and immediate medical consultation are the most critical steps in ensuring effective `meningitis treatment` and improving patient outcomes. No article can substitute professional medical advice, and any suspicion of meningitis requires immediate medical attention.