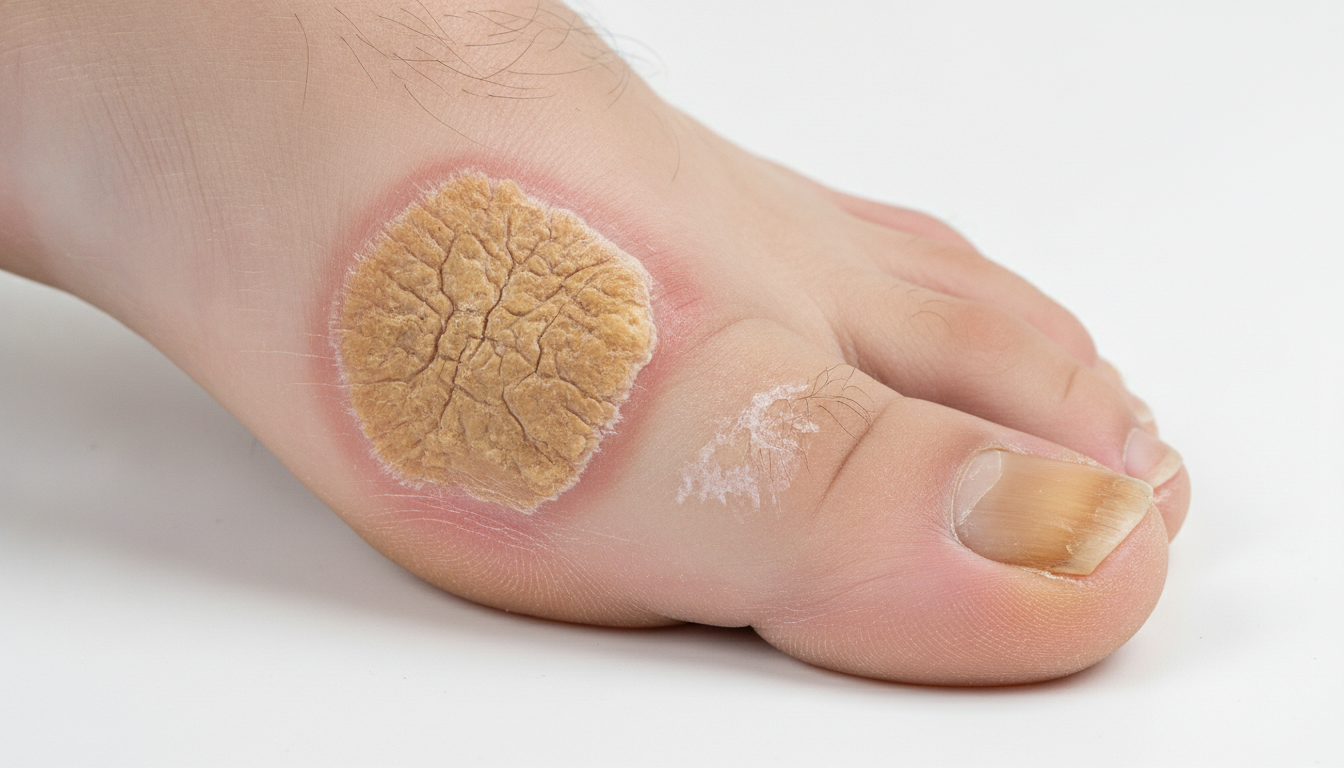
Understanding the visible manifestations of Grade 2 flat feet is crucial for timely recognition and management. This comprehensive guide delves into Grade 2 flat feet symptoms pictures, providing detailed insights into the various dermatological and musculoskeletal signs that can present on the feet and lower limbs. Observing these visual cues can aid in identifying the progression and impact of this condition.
Grade 2 flat feet Symptoms Pictures
When examining Grade 2 flat feet symptoms pictures, a range of visual indicators become apparent, reflecting the altered biomechanics and increased stress on the foot and ankle structures. These visual symptoms are critical for assessing the severity and impact of the condition. The characteristic features often involve significant changes in foot shape and alignment, particularly noticeable when the individual is standing or walking. The collapse of the medial longitudinal arch is a primary visual sign, transforming the foot’s contour from a supportive curve to a flattened profile. This flattening is typically flexible in Grade 1, but in Grade 2 flat feet, while still partially flexible, it presents with more prominent and persistent deformity and associated symptoms.
Key visible symptoms in Grade 2 flat feet pictures include:
- Pronounced Medial Arch Collapse: The most defining visual symptom is the noticeable flattening or complete disappearance of the medial longitudinal arch when weight-bearing. Unlike mild flat feet, in Grade 2 flat feet, this collapse is significant, causing the inner border of the foot to touch or come very close to the ground. This visual flattening is a hallmark of the condition and is often associated with the foot appearing elongated and wider than normal.
- Hindfoot Valgus (Heel Eversion): The heel bone (calcaneus) is visibly everted, meaning it angles outwards away from the midline of the body. When viewed from behind, the Achilles tendon often appears curved or “bowed” outwards rather than running straight up the back of the leg. This abnormal angulation of the heel is a direct consequence of the foot’s pronation and is a prominent feature in Grade 2 flat feet pictures.
- Forefoot Abduction (“Too Many Toes” Sign): When looking at the foot from behind, more of the lateral toes (typically the fourth and fifth) are visible on the outside of the foot than would be expected in a normal foot. This phenomenon is known as the “too many toes” sign and indicates the forefoot has abducted (turned outwards) in relation to the hindfoot. It is a clear visual marker of structural deformity in Grade 2 flat feet.
- Medial Ankle Bulge: Due to the collapsed arch and pronation, the talonavicular joint area, specifically the navicular bone and talar head, becomes prominent on the inner side of the ankle, creating a noticeable bulge. This bony protrusion can be felt and often seen, sometimes leading to localized skin irritation or pressure points from footwear.
- Altered Gait Pattern: While not a static “picture,” observing an individual with Grade 2 flat feet walking reveals compensatory gait patterns. These can include an excessive inward roll of the foot during stance phase, a lack of a distinct heel-to-toe pattern, and a general appearance of instability or a “swaying” motion. The foot may appear to “slap” the ground due to muscle weakness or poor control.
- Skin Changes from Pressure and Friction: Visible skin alterations are common.
- Calluses and Corns: Hardened areas of skin (hyperkeratosis) frequently develop on the plantar surface of the foot. These are often found in atypical locations due to altered pressure distribution, such as:
- Under the medial aspect of the collapsed arch, where the skin now contacts the ground.
- Under the metatarsal heads, particularly the second and third, due to excessive loading.
- On the medial side of the great toe, from rubbing against footwear.
- On the posterior aspect of the heel, if friction occurs with shoe counters.
- Blisters and Chafing: Reddened, irritated skin or fluid-filled blisters can appear in areas of constant friction, such as along the inner arch, the medial aspect of the heel, or between the toes. These indicate significant rubbing against socks or shoes due to the foot’s abnormal motion.
- Skin Redness and Inflammation: Chronic irritation from pressure and friction can lead to localized erythema (redness) and inflammation, particularly along the medial border of the foot or around prominent bony structures.
- Calluses and Corns: Hardened areas of skin (hyperkeratosis) frequently develop on the plantar surface of the foot. These are often found in atypical locations due to altered pressure distribution, such as:
- Swelling (Edema): Mild to moderate swelling can be observed around the ankle and foot, especially after prolonged standing or activity. This edema can be visually subtle, manifesting as a slight puffiness, or more pronounced, causing the skin to appear taut and shiny. Chronic inflammation and compromised circulation can contribute to this symptom.
- Footwear Deformity: Inspection of the individual’s shoes will often show excessive wear patterns on the medial side of the sole and heel, corresponding to the pronated foot position. The shoe upper may also bulge inwards where the medial arch has collapsed. This visual cue provides valuable indirect evidence of Grade 2 flat feet.
- Tightness of Achilles Tendon (Equinus): While not always directly visible as a skin symptom, a tight Achilles tendon often accompanies Grade 2 flat feet. Visually, this can manifest as limited dorsiflexion of the ankle, forcing compensatory pronation of the foot during gait. The calf muscles may also appear hypertrophied from overuse.
These Grade 2 flat feet symptoms pictures highlight the multi-faceted presentation of the condition, emphasizing both structural deformities and the secondary dermatological consequences arising from mechanical stress and abnormal weight distribution. Careful observation of these signs is key for diagnosis and management.
Signs of Grade 2 flat feet Pictures
Delving deeper into the specific signs of Grade 2 flat feet pictures reveals a more detailed array of visual cues that contribute to a comprehensive understanding of the condition. These signs encompass a spectrum from overt structural deformities to subtle dermatological changes, all indicative of the foot’s compromised integrity and function. The examination of these signs provides crucial information for identifying the characteristic features of this intermediate stage of flatfoot deformity.
Detailed visual signs observable in Grade 2 flat feet pictures include:
- Navicular Prominence and Talar Head Sag: A hallmark visual sign is the distinct prominence of the navicular bone and the sagging of the talar head on the medial side of the foot. This bulge is a direct result of the arch collapse, where these bones shift downwards and medially. It can be easily palpated and is often visibly distinct, especially when the foot is weight-bearing. In some cases, prolonged pressure can lead to localized skin irritation or even a small bursitis over this bony prominence.
- Achilles Tendon Deviation: When observed from behind, the Achilles tendon in an individual with Grade 2 flat feet will typically show a lateral curve. Instead of a straight line from the calf to the heel, it will deviate outwards towards the lateral malleolus before inserting into the calcaneus. This “S” shape or curved appearance is a direct visual manifestation of the hindfoot valgus and pronation.
- Ankle Mortise Widening (Apparent): Due to the hindfoot valgus and external rotation of the lower leg bones, the ankle joint may appear wider than normal. This is not a true widening of the joint space but an apparent widening caused by the altered alignment of the talus and calcaneus within the mortise, making the medial malleolus less prominent and the lateral malleolus more pronounced.
- Medial Longitudinal Arch Creases: In some cases of long-standing Grade 2 flat feet, chronic compression and collapse of the arch can lead to the formation of abnormal skin creases or folds along the inner aspect of the foot, especially if there is associated swelling or excess soft tissue. These creases may not be present in early stages but become apparent as the deformity progresses.
- Toenail Deformities and Discoloration: The altered biomechanics can affect the toes.
- Bunions (Hallux Valgus): The great toe often drifts laterally (towards the other toes) and develops a bony prominence at its base (bunion). This is a common secondary deformity in Grade 2 flat feet due to the forefoot abduction and altered pressure during push-off. The skin over the bunion can be reddened, inflamed, or even develop calluses.
- Hammertoes or Claw Toes: The lesser toes may develop contractures, where the joints become bent, causing the toes to appear “hammered” or “clawed.” These deformities are often compensatory for an unstable forefoot or an attempt to grip the ground. The skin over the bent joints can develop calluses or corns due to friction with footwear.
- Onychomycosis (Fungal Nail Infection): The warmer, moister environment created by a pronated foot and compromised airflow, especially within tight footwear, increases the risk of fungal nail infections. Visually, affected nails may appear thickened, discolored (yellow, brown, or white), brittle, or crumbly. This is a common dermatological finding associated with the altered foot environment.
- Plantar Fascia Tension Signs: While the plantar fascia itself is not directly visible, increased tension or inflammation of this band can lead to visible swelling or tenderness along the sole of the foot, particularly near the heel. In some Grade 2 flat feet pictures, subtle soft tissue swelling in this area might be observed.
- Muscle Atrophy/Hypertrophy Patterns: Prolonged Grade 2 flat feet can lead to muscle imbalances.
- Medial Calf Muscle Atrophy: Muscles responsible for maintaining the arch, such as the tibialis posterior, may show signs of weakness or atrophy over time, although this is difficult to discern visually.
- Lateral Calf Muscle Hypertrophy: Conversely, muscles on the lateral side of the leg might appear overdeveloped as they compensate for the instability, leading to a more pronounced lateral calf contour.
- Skin Blisters and Erosions: In addition to calluses, chronic friction can cause skin breakdown. Visually, areas of raw, denuded skin (erosions) or fluid-filled blisters can be present, particularly on the medial aspect of the arch, the inner heel, or under prominent bony areas. These are acute signs of mechanical stress and potential for infection.
- Varicose Veins/Venous Insufficiency Signs: While not a direct cause, the altered biomechanics and potential for chronic swelling in Grade 2 flat feet can sometimes exacerbate or contribute to the development of venous insufficiency in the lower legs. Visually, this can manifest as visible varicose veins, spider veins, skin discoloration (hemosiderin staining, making skin appear brownish), and sometimes stasis dermatitis in more severe, chronic cases.
- Asymmetry in Foot Size/Shape: If Grade 2 flat feet affects only one foot or is more severe on one side, a noticeable asymmetry in foot size, width, or overall shape between the two feet can be observed, particularly when weight-bearing.
These specific signs of Grade 2 flat feet pictures offer a granular view of the condition’s progression, emphasizing both the skeletal malalignment and the consequent dermatological and soft tissue responses. Recognizing these signs is paramount for accurate assessment and the formulation of targeted intervention strategies for Grade 2 flat feet symptoms.
Early Grade 2 flat feet Photos
Examining early Grade 2 flat feet photos requires a keen eye for subtle yet significant changes that distinguish it from mild pronation or Grade 1 flat feet. At this stage, while the deformity is still largely flexible, its impact on foot structure and function is becoming more pronounced, leading to visible alterations that can signal the progression of the condition. These early visual cues are crucial for proactive intervention and preventing further deterioration. The focus here is on emerging signs that might not yet be severe but indicate a clear shift towards a more involved flatfoot deformity and associated symptoms.
Key indicators in early Grade 2 flat feet photos include:
- Subtle Medial Arch Flattening (Dynamic): The arch may still appear somewhat present when non-weight-bearing (e.g., sitting), but it visibly flattens significantly upon standing. This dynamic collapse, where the arch loses its integrity under load, is a hallmark of early Grade 2 flat feet. The impression on a wet footprint test might show a nearly full impression of the sole, but with a slight indentation where the arch should be.
- Emerging Heel Valgus: While not yet extreme, a slight outward tilt of the heel (eversion) becomes discernible when standing. The Achilles tendon, when viewed from behind, may show a nascent curve rather than a perfectly straight line. This subtle angulation indicates early compromise of the hindfoot’s alignment.
- Faint “Too Many Toes” Sign: A few extra toes (perhaps just the fourth toe) may become barely visible on the lateral side when viewing the foot from behind. This is less pronounced than in advanced stages but signals the early abduction of the forefoot.
- Intermittent Medial Ankle Fullness: The area around the talonavicular joint on the inner ankle might show a slight fullness or bulge that becomes more evident after prolonged standing or activity. This is an early manifestation of the talar head dropping and the navicular becoming more prominent.
- Early Callus Formation: Small, localized areas of thickened skin (calluses) may begin to form in atypical pressure zones. These are often not yet painful or extensive but indicate areas of increased friction or weight bearing that wouldn’t be present in a normally arched foot. Common early locations include:
- Under the second metatarsal head.
- Along the medial border of the great toe.
- On the skin that now contacts the ground under the midfoot arch.
- Mild Skin Irritation and Redness: Localized patches of redness (erythema) or mild irritation might appear on the medial aspect of the foot or heel, especially after wearing certain footwear or engaging in prolonged physical activity. This suggests increased friction and pressure that is beginning to affect skin integrity. This could be an early sign of what might develop into a skin rash Grade 2 flat feet manifestation.
- Subtle Gait Alterations: A slight inward rolling of the foot during walking, or a less efficient push-off, may be observed. The overall gait might appear slightly less fluid or more “clumsy” compared to someone with normal arches, particularly at the end of the day or after significant walking.
- Foot Fatigue and Mild Swelling: While swelling might not be consistently present in early Grade 2 flat feet photos, individuals often report and display mild, transient edema around the ankles and midfoot, particularly after extended periods of weight-bearing. Visually, this manifests as a slight puffiness that resolves with rest.
- Footwear Wear Patterns (Initial): Early stages might show slightly accelerated or uneven wear on the medial edge of shoe soles and heels. This early wear pattern is an important visual clue, indicating abnormal biomechanical forces at play.
- Increased Foot Sweating (Hyperhidrosis): The altered foot mechanics and potentially enclosed environment within footwear can lead to increased perspiration. While not directly “visible” in a photo, the effects might be (e.g., dampness in socks, slight maceration between toes). This excessive moisture contributes to the risk of various skin rash Grade 2 flat feet issues.
- Early Signs of Compensatory Deformities: The great toe may show an initial tendency to drift laterally, or the base of the great toe might start to appear slightly more prominent (early bunion formation). Similarly, a subtle flexion contracture in one of the lesser toes might be noticed.
- Loss of Flexible Arch Recoil: A key diagnostic for Grade 2 flat feet is that the arch, while flexible, doesn’t fully recoil to a normal position even when non-weight bearing, or it requires manual correction. This means that while you can manipulate the arch, it doesn’t naturally spring back into a healthy curve, differentiating it from completely flexible flat feet.
These observations in early Grade 2 flat feet photos provide critical insights into the onset and progression of the condition, allowing for earlier identification and implementation of interventions. Recognizing these subtle signs is vital for preventing the development of more severe pain, deformity, and associated skin complications.
Skin rash Grade 2 flat feet Images
The presence of a skin rash Grade 2 flat feet images is a significant indicator of the dermatological complications arising from the altered biomechanics, increased pressure, friction, and moisture associated with this condition. While flat feet are an orthopedic issue, the skin is highly susceptible to secondary problems due to the constant stress and changed environment. These skin manifestations can range from simple irritation to complex infections, and their recognition is vital for comprehensive patient care. The unique contours and pressure points of Grade 2 flat feet create specific vulnerabilities for various dermatoses.
Common skin rashes and dermatological issues seen in Grade 2 flat feet images include:
- Intertrigo:
- Appearance: Red, inflamed skin often with maceration (whitening and softening of skin due to moisture), itching, burning, and sometimes a foul odor. May appear shiny or eroded.
- Location: Primarily in skin folds where skin rubs against skin and moisture accumulates. In Grade 2 flat feet, this often occurs:
- Between the toes, especially the fourth and fifth.
- Underneath the collapsed medial arch, particularly if there is significant swelling or adipose tissue creating a skin fold.
- Around the medial ankle bulge where shoe pressure may create a fold.
- Cause: Friction, heat, and moisture retention in skin folds, exacerbated by the pronated foot structure and potential hyperhidrosis (excessive sweating). This moist environment provides an ideal breeding ground for bacteria and fungi.
- Tinea Pedis (Athlete’s Foot):
- Appearance: Can present in various forms:
- Interdigital: Scaling, redness, maceration, and fissures between the toes, often starting in the web spaces.
- Mocassin-type: Chronic scaling and thickening of the skin on the sole and sides of the foot, often with mild redness.
- Vesiculobullous: Blisters (vesicles or bullae), often itchy, containing clear fluid, usually on the sole or instep.
- Location: Commonly between the toes, on the soles, and sides of the foot. The pronated foot can trap more moisture within shoes, promoting fungal growth.
- Cause: Fungal infection (dermatophytes) thrives in warm, moist, dark environments, which are characteristic of feet with Grade 2 flat feet confined within footwear.
- Appearance: Can present in various forms:
- Contact Dermatitis:
- Appearance: Red, itchy rash, often with vesicles, papules, scaling, or crusting. The pattern of the rash often corresponds to the area of contact with the irritant or allergen.
- Location: Anywhere the skin comes into contact with an offending substance. Common areas for Grade 2 flat feet include:
- Dorsum of the foot or around the ankle from shoe materials (e.g., glues, dyes, rubber, leather treatments).
- Around the toes or on the sole from sock materials (e.g., synthetic fibers, detergents).
- In areas where topical creams or medications have been applied.
- Cause: Allergic reaction to specific materials in footwear, socks, or topical treatments (allergic contact dermatitis) or irritation from prolonged exposure to irritating substances (irritant contact dermatitis). The friction and pressure points of Grade 2 flat feet can make the skin more susceptible to penetration by allergens/irritants.
- Irritant Dermatitis (Chafing/Excoriations):
- Appearance: Areas of redness, mild swelling, raw or abraded skin (excoriations), often with a burning sensation.
- Location: Along areas of high friction, such as the medial aspect of the arch, the inner heel, the sides of the toes, or where shoe uppers rub against bony prominences like the navicular or medial malleolus.
- Cause: Continuous rubbing or shearing forces against the skin due to the abnormal foot motion and contact patterns characteristic of Grade 2 flat feet, particularly when combined with ill-fitting footwear.
- Bacterial Infections (Cellulitis, Folliculitis, Impetigo):
- Appearance:
- Cellulitis: Spreading redness, warmth, swelling, and tenderness, often with ill-defined borders. May be accompanied by fever.
- Folliculitis: Small, red bumps or pustules centered around hair follicles.
- Impetigo: Red sores that quickly rupture, ooze, and form a honey-colored crust.
- Location: Can occur anywhere on the foot or lower leg. Break in the skin barrier (e.g., from blisters, fissures, excoriations) associated with Grade 2 flat feet provides entry points.
- Cause: Bacterial invasion (commonly Staphylococcus aureus or Streptococcus pyogenes) through compromised skin. The moist, warm environment and skin damage from Grade 2 flat feet increase susceptibility.
- Appearance:
- Psoriasis (Koebner Phenomenon):
- Appearance: Well-demarcated, red patches covered with silvery scales. Can sometimes affect nails.
- Location: While psoriasis is systemic, chronic irritation and trauma to the skin, such as that experienced in areas of high pressure/friction with Grade 2 flat feet, can trigger new psoriatic lesions in susceptible individuals (Koebner phenomenon).
- Cause: Autoimmune condition, but physical trauma can localize flares.
- Stasis Dermatitis (Less Direct but Possible):
- Appearance: Reddish-brown discoloration (hyperpigmentation), scaling, itching, and sometimes ulcers, often with associated edema.
- Location: Typically on the lower legs and ankles.
- Cause: While Grade 2 flat feet do not directly cause venous insufficiency, chronic swelling and inflammation associated with severe flatfoot deformity can exacerbate existing venous issues or contribute to the development of stasis dermatitis over time, particularly in individuals with predisposing factors.
Each of these skin rash Grade 2 flat feet images represents a potential complication that adds to the discomfort and functional limitations experienced by individuals with the condition. Addressing these dermatological symptoms often requires a multi-pronged approach, integrating dermatological treatments with management strategies for the underlying orthopedic deformity.
Grade 2 flat feet Treatment
Effective Grade 2 flat feet treatment focuses on alleviating symptoms, improving foot biomechanics, preventing further progression of the deformity, and managing associated complications, particularly the various skin issues that can arise. For Grade 2 flat feet, treatment is typically non-surgical initially, emphasizing supportive measures and physical therapy. The goal is to reduce pain, enhance function, and minimize the dermatological problems frequently observed in Grade 2 flat feet symptoms pictures.
Comprehensive Grade 2 flat feet treatment strategies include:
- Orthotics and Arch Supports:
- Custom Orthotics: These are highly recommended for Grade 2 flat feet. They are specifically molded to the individual’s foot, providing superior arch support, correcting hindfoot valgus, and controlling pronation. They redistribute pressure, reducing stress on affected joints and soft tissues. This directly helps in preventing and managing calluses, blisters, and localized skin irritation by normalizing weight distribution and reducing friction.
- Over-the-Counter (OTC) Arch Supports: While less customized, well-chosen OTC arch supports can offer some relief for milder cases or as a temporary measure. Look for rigid or semi-rigid supports that provide adequate arch elevation and heel stability to counteract the pronation seen in Grade 2 flat feet symptoms pictures.
- Benefits for Skin: By restoring proper foot alignment, orthotics reduce abnormal pressure points and friction, thereby decreasing the likelihood of developing new calluses, corns, blisters, and areas prone to chafing and skin breakdown. They also create a more stable environment within the shoe, indirectly reducing moisture accumulation in certain areas, which can mitigate the risk of intertrigo and fungal infections.
- Appropriate Footwear:
- Supportive Shoes: Footwear should have a firm heel counter, good arch support (to complement orthotics), a wide toe box, and a rigid sole that doesn’t twist easily. Shoes should be well-fitting to prevent excessive foot movement inside the shoe.
- Avoidance: High heels, completely flat shoes (like ballet flats), and flimsy sandals often lack the necessary support and can exacerbate Grade 2 flat feet symptoms and associated skin issues.
- Benefits for Skin: Proper shoes minimize friction against bony prominences and areas of altered skin contact, reducing the risk of blisters, calluses, and irritant dermatitis. A wide toe box prevents compression and rubbing on toes, mitigating bunion and hammertoe-related skin problems. Breathable materials can help manage moisture, which is key for preventing fungal and bacterial skin conditions observed in skin rash Grade 2 flat feet images.
- Physical Therapy and Exercises:
- Strengthening Exercises: Focus on strengthening the muscles that support the arch, particularly the tibialis posterior, as well as intrinsic foot muscles. Examples include toe curls, marble pickups, and short-foot exercises.
- Stretching Exercises: Address any tightness in the Achilles tendon and calf muscles (gastroc-soleus complex), which often contributes to flatfoot deformity. Regular calf stretches are crucial.
- Balance and Proprioception: Exercises to improve balance and foot control (e.g., standing on one leg, wobble board exercises) can enhance overall foot stability.
- Benefits for Skin: Improved muscle strength and flexibility can lead to better foot mechanics, reducing abnormal pressure and friction on the skin during gait. This indirectly contributes to healthier skin by reducing mechanical stress.
- Pain Management:
- RICE Protocol: Rest, Ice, Compression, and Elevation can help reduce acute pain and swelling associated with inflammation from Grade 2 flat feet.
- NSAIDs: Over-the-counter non-steroidal anti-inflammatory drugs (NSAIDs) like ibuprofen or naproxen can help manage pain and inflammation.
- Benefits for Skin: Reducing inflammation and swelling can decrease skin tautness and discomfort, and lessen the propensity for certain types of dermatitis if edema is a contributing factor.
- Weight Management:
- Impact: Excess body weight significantly increases the load on the feet, exacerbating arch collapse and increasing stress on joints and soft tissues.
- Benefits: Losing even a modest amount of weight can substantially reduce the mechanical stress on the feet, which in turn can alleviate pain, slow progression of deformity, and reduce pressure-related skin issues.
- Dermatological Management for Skin Rashes:
- Antifungal Medications: For tinea pedis, topical antifungal creams (e.g., clotrimazole, miconazole, terbinafine) are often prescribed. Severe or persistent cases might require oral antifungals.
- Antibiotics: Bacterial infections like cellulitis or impetigo require topical or oral antibiotics, depending on severity.
- Corticosteroids: Topical corticosteroids can reduce inflammation and itching associated with contact dermatitis, intertrigo, or other eczematous rashes.
- Moisture Management: Use of moisture-wicking socks, foot powders, and ensuring feet are thoroughly dried, especially between toes, are vital to prevent intertrigo and fungal growth.
- Blister and Callus Care:
- Blisters: Clean the area, drain large blisters carefully (if necessary, by a professional), and apply protective dressings. Avoid popping small, intact blisters.
- Calluses and Corns: Regular exfoliation with a pumice stone or file, combined with daily application of emollient creams containing urea or salicylic acid, can help soften and reduce thickened skin. Professional debridement by a podiatrist is recommended for severe or painful calluses/corns.
- Barrier Creams: For areas prone to intertrigo or chafing, zinc oxide-based creams or petroleum jelly can provide a protective barrier against moisture and friction.
- Activity Modification:
- Temporary Reduction: Initially, reducing activities that exacerbate pain or cause significant skin irritation can provide relief and allow tissues to heal.
- Gradual Return: Slowly reintroduce activities, ensuring proper footwear and orthotic use.
- Surgical Intervention (Advanced Cases):
- When Considered: Surgery for Grade 2 flat feet is typically reserved for cases where non-surgical treatments have failed, pain is severe and debilitating, and there is progressive deformity that significantly impacts quality of life.
- Types of Surgery: Procedures can range from soft tissue reconstructions (e.g., tibialis posterior tendon repair/transfer, gastrocnemius recession) to bony procedures (e.g., osteotomies of the calcaneus or midfoot, fusions).
- Benefits: Surgical correction aims to realign the foot structure, restore the arch, and improve overall biomechanics. This, in turn, resolves the underlying mechanical issues that contribute to chronic pain and many of the dermatological complications seen in Grade 2 flat feet symptoms pictures.
A multi-disciplinary approach involving podiatrists, orthopedic surgeons, physical therapists, and dermatologists is often most effective for comprehensive Grade 2 flat feet treatment, particularly when complex dermatological issues are present alongside the orthopedic deformity. Early and consistent management is key to preventing long-term complications and improving patient quality of life.