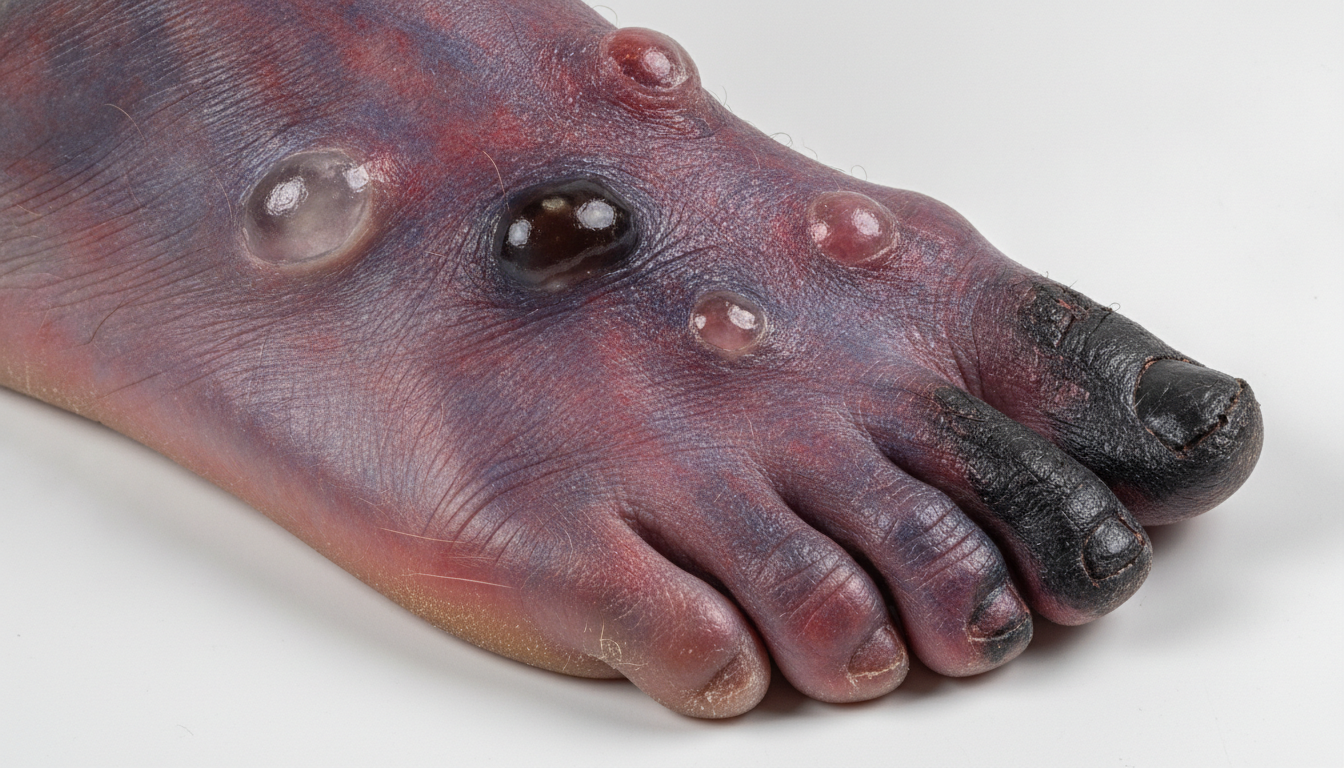
Our comprehensive guide provides crucial insights into identifying frostbite of the feet symptoms pictures, offering detailed descriptions to aid in early recognition and appropriate action. Understanding these visual and sensory indicators is paramount for anyone exposed to freezing temperatures, as timely intervention can significantly impact outcomes related to foot frostbite. This resource focuses directly on the manifestations of cold injury to the feet, presenting a clear picture of what to look for.
Frostbite of the feet Symptoms Pictures
Recognizing frostbite of the feet symptoms pictures is critical for prompt management and preventing long-term damage. The symptoms of foot frostbite can vary widely depending on the severity and duration of exposure to freezing temperatures, but typically involve a progression of sensory and visual changes. Initial indications often include a loss of sensation, followed by characteristic alterations in skin appearance and texture. These visible signs provide invaluable clues about the extent of cold injury to the feet.
The earliest foot frostbite symptoms are primarily sensory, often preceding noticeable visual changes. Individuals may experience a profound numbness that masks the underlying damage, making it challenging to assess the severity initially. As the condition progresses, the superficial layers of the skin, and potentially deeper tissues, undergo various transformations. Key visual identifiers include changes in skin color, the presence of swelling, and the development of blisters, which are crucial for assessing the degree of frostbite injury. Understanding these indicators is vital for appropriate medical intervention.
Detailed list of frostbite of the feet symptoms:
- Numbness and Loss of Sensation: One of the most common and earliest symptoms. The affected foot or toes feel numb, often described as a “wooden” or “dead” feeling. This can make walking or performing fine motor tasks with the toes extremely difficult or impossible. The profound lack of sensation can sometimes lead individuals to underestimate the severity of their injury, as pain may not be present initially.
- Stinging, Burning, or Aching Sensation: After rewarming, or in some superficial cases, individuals may experience intense pain, throbbing, stinging, or burning sensations. This pain can be severe and persistent, often requiring strong analgesics. The nature of the pain can shift from dull aching to sharp, shooting sensations as nerves begin to recover or are further damaged.
- Skin Discoloration:
- Pale or Waxy Appearance: Initially, the skin on the affected foot or toes may appear abnormally white, pale, or grayish-yellow. This is due to vasoconstriction, where blood vessels narrow, reducing blood flow to the affected area. The skin may look waxy, dull, or strangely lifeless.
- Bluish or Purplish Hue: As frostbite progresses, especially in deeper injuries, the skin can take on a bluish or purplish discoloration. This indicates a lack of oxygenated blood flow and can be a sign of tissue damage. The color may appear mottled or patchy.
- Redness (Erythema) After Rewarming: Upon rewarming, the skin may become intensely red, inflamed, and painful. This reactive hyperemia is a normal response to re-establishing blood flow but can also indicate an inflammatory response that requires careful monitoring.
- Blackened or Mummified Skin: In severe, deep frostbite (third or fourth degree), the tissue can become necrotic and turn black, hard, and leathery, resembling mummified tissue. This indicates irreversible tissue death and is a critical sign of advanced frostbite.
- Skin Texture Changes:
- Firm or Hard to the Touch: The affected area, particularly the toes or sole of the foot, may feel unusually firm, rigid, or hard, sometimes described as feeling “wooden” or “frozen solid.” This indicates that the deeper tissues are affected by the ice crystal formation.
- Swelling (Edema): Significant swelling of the foot and toes is common after rewarming, due to fluid leakage from damaged capillaries. This edema can be substantial and contribute to pain and pressure.
- Blister Formation: Blisters are a hallmark symptom of more advanced frostbite and are critical for assessing severity.
- Clear or Milky Blisters: Typically develop within 12-24 hours after rewarming in superficial (second-degree) frostbite. These blisters are filled with clear or milky fluid and indicate damage to the epidermal and superficial dermal layers. They are often associated with pain and tenderness.
- Hemorrhagic Blisters: Blisters filled with blood or dark fluid usually appear 24-48 hours after rewarming in deep (third-degree) frostbite. These indicate more significant damage, including to the deeper dermal layers and blood vessels. Hemorrhagic blisters are a sign of more severe tissue injury and carry a poorer prognosis for tissue survival.
- Clumsiness or Stiffness: The affected foot or toes may feel clumsy, stiff, or difficult to move due to muscle and nerve involvement. This can impair gait and balance, leading to an increased risk of falls.
- Lack of Blood Flow (Ischemia): In severe cases, there may be a complete absence of blood flow to the affected area, leading to pallor and eventual tissue necrosis. Peripheral pulses may be diminished or absent.
- Later Stages – Gangrene and Tissue Loss: If the tissue is irreversibly damaged, it will eventually turn black, shrivel, and become gangrenous. This can lead to spontaneous autoamputation of toes or require surgical amputation. This stage represents the most severe outcome of deep foot frostbite.
- Pain upon Rewarming: As circulation returns, the affected area can become intensely painful, throbbing, and burning. This rewarming pain is a common and often severe symptom, indicative of reperfusion injury and nerve sensitization.
Observing these frostbite signs on feet and understanding their implications is crucial for differentiating between superficial and deep injuries, which dictates the urgency and type of medical intervention required. Early recognition and immediate medical consultation are paramount for minimizing irreversible tissue damage and optimizing recovery outcomes for frostbite of the lower extremities.
Signs of Frostbite of the feet Pictures
The signs of frostbite of the feet pictures reveal a spectrum of changes that correlate directly with the depth and extent of cellular damage. These visual cues are essential for healthcare providers to accurately diagnose and stage the injury, guiding treatment strategies for foot cold injury. The presentation varies significantly from the mildest form, known as frostnip, to severe, full-thickness tissue destruction. Each stage presents distinct morphological features that are important for prognosis and management.
Visual assessment of the foot is a primary diagnostic tool for diagnosing foot frostbite. Observing the color, presence of blisters, and skin texture allows for a rapid preliminary evaluation. For instance, the transition from pale, waxy skin to the formation of clear or hemorrhagic blisters is a clear indicator of progressing severity. Understanding these visual signs helps in distinguishing between reversible injuries and those with significant tissue loss potential, directly impacting the long-term health of the affected limb. Timely identification of these signs is critical for preventing irreversible damage.
Detailed list of signs of frostbite of the feet based on severity:
- First-Degree Frostbite (Frostnip): This is the mildest form of cold injury to the feet, affecting only the superficial layers of the skin without permanent tissue damage.
- Skin Appearance: Typically appears pale, waxy, or grayish-yellow. Upon rewarming, the skin often becomes red (erythema) and may be slightly swollen. There is no blistering at this stage.
- Sensation: The affected area feels numb or prickly. Patients may experience a stinging, burning, or aching sensation during rewarming. Sensation returns completely with no lasting effects.
- Texture: The skin remains soft and pliable to the touch, distinguishing it from more severe forms where the tissue becomes firm.
- Prognosis: Excellent, with full recovery expected. Long-term sensitivity to cold may occur.
- Keywords: mild foot frostbite, frostnip on toes, superficial cold injury feet.
- Second-Degree Frostbite (Superficial Frostbite): Involves the epidermis and superficial dermis. This stage is characterized by blister formation, indicating more significant cellular injury.
- Skin Appearance: Initially pale or white, but after rewarming, the skin becomes significantly red and swollen. The hallmark sign is the appearance of clear or milky fluid-filled blisters within 12-24 hours. These blisters often form over a hyperemic (reddened) base.
- Sensation: Numbness persists, but as the skin warms, intense pain, throbbing, and burning sensations are common. The area may feel sensitive to touch.
- Texture: The skin may feel firm or doughy to the touch. The swelling can be considerable.
- Prognosis: Generally good if managed properly, though healing can take several weeks. There may be residual cold sensitivity, hyperhidrosis, or numbness.
- Keywords: blisters on feet from cold, superficial frostbite symptoms, painful foot frostbite.
- Third-Degree Frostbite (Deep Frostbite): Involves full-thickness dermal and subdermal tissue damage. This is a severe injury with a higher risk of permanent tissue loss.
- Skin Appearance: The affected foot or toes initially appear pale, waxy, or mottled blue-gray. After rewarming, characteristic large, dark hemorrhagic (blood-filled) blisters develop within 24-48 hours, often extending to the tips of the toes. The skin eventually becomes blackened, hard, and leathery (eschar formation).
- Sensation: Numbness is profound and often persists even after rewarming due to nerve damage. There may be a sensation of “wooden” rigidity. Pain, if present, can be severe but may also be absent due to extensive nerve destruction.
- Texture: The entire thickness of the skin and subcutaneous tissue feels firm, hard, and non-pliable, like “frozen wood.”
- Prognosis: Poor for complete recovery of the affected tissue. Significant tissue loss, scarring, and functional impairment are common. Amputation may be necessary.
- Keywords: deep frostbite foot, hemorrhagic blisters frostbite, severe foot cold injury.
- Fourth-Degree Frostbite (Full-Thickness Frostbite): The most severe form, involving muscle, tendon, and bone. This leads to complete tissue necrosis.
- Skin Appearance: The skin immediately appears mottled, deep purple, or black. After rewarming, there is little or no edema or blister formation, as the blood vessels are completely thrombosed. The tissue rapidly progresses to a hard, dry, black, mummified state.
- Sensation: Complete and permanent loss of sensation due to irreversible nerve damage. The foot feels completely “dead” and insensate.
- Texture: The entire limb section is hard, cold, and appears shrunken, similar to a mummified specimen.
- Prognosis: Extremely poor. Amputation of the affected toes or part of the foot is almost always required due to irreversible tissue death and gangrene.
- Keywords: gangrene foot frostbite, irreversible frostbite damage, bone frostbite feet, amputation frostbite.
Accurate identification of these signs of foot frostbite is critical for initiating the correct treatment protocol. The presence and type of blistering, along with the depth of tissue firmness, are key discriminators. Early and appropriate management, guided by these visual and tactile signs, can significantly impact the final outcome and reduce the severity of long-term complications associated with severe frostbite of the feet.
Early Frostbite of the feet Photos
Understanding the manifestations depicted in early frostbite of the feet photos is paramount for swift intervention. These initial visual cues, often subtle, can easily be overlooked or mistaken for benign cold exposure. However, recognizing the very first signs of cold injury to the feet is crucial for preventing progression to more severe stages. At this juncture, tissue damage is often reversible, making early detection a primary goal for individuals at risk and first responders. The appearance of the skin in these early phases provides immediate actionable information.
The earliest visual symptoms of foot cold injury initial signs are characterized by a blanching of the skin, accompanied by a loss of tactile sensation. The skin may appear unnaturally pale or waxy, indicating reduced blood flow. Unlike later stages, blistering is absent, and the skin often remains soft to the touch. These subtle changes, if ignored, can rapidly give way to more pronounced and damaging effects as exposure to freezing temperatures continues. Prompt removal from the cold environment and initial rewarming are vital steps based on these early observations.
Detailed list of early frostbite on feet characteristics:
- Initial Pallor and Skin Whitening:
- Appearance: The affected toes or parts of the foot turn abnormally white, pale, or a grayish-yellow. This is due to profound vasoconstriction, where blood vessels constrict to conserve heat in the core, reducing blood flow to the extremities.
- Texture: The skin may appear waxy or unusually dull. It often loses its normal pinkish tone.
- Significance: This is often the very first visible sign of true frostbite, distinguishing it from simple chilling.
- Keywords: initial foot frostbite, pale toes frostbite, waxy skin cold injury.
- Numbness and Tingling:
- Sensation: A strong feeling of numbness in the affected foot or toes is typically present. This can be accompanied by tingling, prickling, or a dull ache. The sensory loss can be so complete that the individual is unaware of the damage occurring.
- Implication: This indicates nerve dysfunction due to cold exposure and ice crystal formation within the tissues. It’s a critical early warning.
- Keywords: numb feet cold, tingling toes frostbite, loss of sensation in cold.
- Skin Softness (in Frostnip):
- Texture: Unlike deeper frostbite, in frostnip (first-degree frostbite), the skin remains soft and pliable when gently pressed. This is a key differentiating factor.
- Significance: This indicates that the damage is superficial and has not yet affected deeper tissues, which would feel firm or hard.
- Keywords: soft skin frostbite, reversable cold injury.
- Absence of Blisters:
- Visual Cue: In the earliest stages, particularly frostnip, there are no blisters. Blister formation is a sign of more advanced superficial (second-degree) or deep (third-degree) frostbite, appearing later, typically after rewarming.
- Importance: This absence helps categorize the injury as mild if other severe signs are also absent.
- Keywords: no blisters frostbite, early foot cold damage.
- Clumsiness and Stiffness:
- Motor Function: The affected foot and toes may feel stiff, awkward, or clumsy, making walking difficult. This can be due to reduced nerve conduction and muscle stiffness from the cold.
- Impact: Impaired motor function increases the risk of falls or further injury in a cold environment.
- Keywords: stiff toes cold, clumsy feet frostbite.
- Burning or Stinging upon Rewarming (Initial Response):
- Sensation: As the foot begins to warm up, a painful stinging, burning, or throbbing sensation may emerge. This indicates blood flow returning to the area and the initial inflammatory response.
- Caution: While a sign of rewarming, intense pain can also signal underlying tissue damage, requiring careful monitoring.
- Keywords: rewarming pain feet, burning toes cold.
These features, seen in early frostbite of the feet photos, are critical for timely recognition. Any individual experiencing these symptoms after exposure to freezing temperatures should seek medical attention promptly. Early intervention, focusing on careful rewarming and supportive care, can significantly reduce the risk of permanent tissue damage and long-term complications associated with mild frostbite feet.
Skin rash Frostbite of the feet Images
The term “skin rash frostbite of the feet images” encompasses a range of post-exposure skin changes that can resemble a rash, particularly after rewarming. While not a typical dermatological rash in the infectious sense, the skin’s reaction to cold injury often presents with distinct patterns of discoloration, blistering, and inflammation that can be visually interpreted as a form of rash. These post-rewarming phenomena are critical diagnostic indicators, revealing the extent of vascular and cellular damage from cold injury to the foot skin.
Following rewarming, the immediate response of the skin on the feet can include intense redness and swelling, which might superficially resemble an allergic reaction or an inflammatory rash. However, the progression to characteristic blisters—either clear or blood-filled—or the eventual darkening and hardening of the skin differentiates these patterns from other dermatological conditions. Understanding these specific manifestations is vital for accurately diagnosing and managing the sequelae of foot skin discoloration frostbite. Each stage of this “rash-like” presentation tells a story about the underlying tissue viability.
Detailed list of frostbite skin changes on feet that may appear rash-like:
- Post-Rewarming Erythema and Edema:
- Appearance: After rewarming, the affected foot or toes typically become intensely red, inflamed, and significantly swollen (edematous). This redness is due to reactive hyperemia (increased blood flow) as circulation is restored.
- Sensation: The area is often painful, throbbing, and tender to touch.
- Distinction: This redness can resemble a severe sunburn or cellulitis, but its context of cold exposure is key for diagnosis.
- Keywords: red feet frostbite, swollen toes cold injury, inflammatory response frostbite.
- Blister Formation (Clear or Milky):
- Appearance: Within 12-24 hours post-rewarming, especially in second-degree frostbite, numerous clear or milky fluid-filled blisters develop. These appear as raised lesions over the reddened and swollen skin.
- Pattern: The blisters can be scattered or confluent, covering significant portions of the toes or foot, giving a distinct “rash-like” appearance. They indicate damage to the epidermis and superficial dermis.
- Keywords: clear blisters frostbite, fluid-filled cold sores feet, superficial skin damage cold.
- Hemorrhagic Blisters (Blood-filled):
- Appearance: In third-degree frostbite, dark, blood-filled blisters emerge 24-48 hours after rewarming. These are larger and darker than clear blisters, reflecting deeper vascular damage.
- Pattern: These blisters often occur over areas of deeper tissue injury, and their presence is a grave sign, indicating a high risk of tissue loss. They present a different, more ominous “rash” pattern.
- Keywords: blood blisters frostbite, dark spots cold injury, deep dermal damage feet.
- Mottling and Discoloration:
- Appearance: Patchy areas of bluish-red or purplish discoloration (mottling) can appear on the skin of the feet. This reflects impaired circulation and venous stasis, where blood pools in damaged capillaries.
- Pattern: The mottled appearance can look like a diffuse, irregular rash, particularly if patchy blood flow is still present.
- Keywords: mottled skin frostbite, purple toes cold, ischemic skin changes feet.
- Desquamation (Peeling) and Cracking:
- Appearance: In milder cases (first and second degree), after the initial inflammation subsides, the skin may begin to peel and desquamate, similar to a severe sunburn. The skin may also crack, especially if dry.
- Pattern: This peeling can create a widespread, flaky “rash” as the damaged superficial layers of skin shed.
- Keywords: peeling skin frostbite, flaky feet cold injury, skin cracking cold.
- Later Pigmentary Changes:
- Appearance: Over weeks to months, areas affected by frostbite may develop persistent hyperpigmentation (darkening of the skin) or hypopigmentation (lightening of the skin).
- Pattern: These patchy changes can create an enduring “rash-like” appearance, indicating long-term scarring and melanocyte damage.
- Keywords: hyperpigmentation frostbite, skin scarring cold injury, uneven skin tone feet.
- Necrosis and Eschar Formation:
- Appearance: In severe cases (third and fourth degree), the skin turns black, hard, and leathery, forming an eschar. This is the ultimate “rash” of severe tissue death.
- Pattern: This is a clear sign of irreversible damage and forms a stark contrast to viable tissue.
- Keywords: black skin frostbite, necrotic toes, eschar formation feet.
These specific descriptions, often observed in skin rash frostbite of the feet images, underscore the diverse and often severe dermatological manifestations of cold injury. Careful assessment of these patterns helps distinguish the severity and guides appropriate wound care and medical management for frostbite affected skin. Early recognition of these distinct patterns is vital for improved patient outcomes.
Frostbite of the feet Treatment
Effective frostbite of the feet treatment hinges on rapid, appropriate intervention to minimize tissue damage and prevent long-term complications. The management strategy for foot cold injury management is multifaceted, beginning immediately in the field and continuing through specialized medical care, often involving a multidisciplinary team. The primary goals are to rapidly restore blood flow, protect viable tissue, manage pain, prevent infection, and facilitate healing. Understanding the different phases of treatment is crucial for anyone involved in the care of frostbite patients.
The immediate priorities upon identifying foot frostbite symptoms are to remove the patient from the cold environment and initiate careful rewarming. However, rewarming must be done cautiously to avoid further damage. Subsequent medical management focuses on wound care, pain control, prevention of secondary injuries, and, in severe cases, surgical interventions to preserve function and prevent systemic complications. Long-term care often involves physical therapy and ongoing management of sequelae such as cold sensitivity and neuropathy. Each step of the treatment process is critical for maximizing recovery and functional outcomes.
Detailed list of how to treat foot frostbite:
- Pre-Hospital and Field Management (Initial Frostbite First Aid Feet):
- Move to a Warm Environment: Immediately remove the affected individual from the cold source.
- Remove Constrictive Clothing/Jewelry: Take off wet or constrictive clothing, shoes, and socks from the feet and toes to avoid further compression and improve circulation.
- Protect the Area: Gently wrap the affected feet in dry, sterile dressings or clean cloths. Avoid rubbing or massaging the frostbitten area, as this can cause further tissue damage.
- Elevate: If possible, gently elevate the feet to reduce swelling once in a protected environment.
- Do NOT Re-Warm if Re-Freezing Risk: This is a critical point. If there is any chance of re-freezing after initial rewarming, it is better to keep the foot frozen until a definitive, stable rewarming environment can be ensured. Repeated freezing and thawing causes more damage.
- Warm Drinks and Food: Provide warm, non-alcoholic, non-caffeinated beverages to aid core rewarming.
- Transport: Seek immediate medical attention. Transport the patient to a medical facility as quickly and safely as possible.
- Keywords: frostbite emergency care, cold exposure first aid, pre-hospital frostbite management.
- Hospital Management and Rapid Rewarming:
- Systemic Rewarming: Address hypothermia first if present, gradually warming the core body temperature.
- Rapid Immersion Rewarming: The cornerstone of frostbite treatment. The affected feet are rapidly immersed in a circulating water bath maintained at a temperature of 37-39°C (98.6-102.2°F). This process is continued until the tissues are pliable and red/purple, and sensation has returned, which typically takes 15-30 minutes but can be longer. This is often described as excruciatingly painful.
- Pain Management: Due to severe rewarming pain, strong analgesics (e.g., opioids, NSAIDs) are almost always required during and after rewarming. Regional nerve blocks may also be considered.
- Keywords: rapid rewarming frostbite, pain control frostbite, hospital frostbite care.
- Wound Care and Infection Prevention:
- Blister Management:
- Clear Blisters: Typically debrided (removed) to allow for topical wound care, reduce inflammatory mediators, and prevent infection.
- Hemorrhagic Blisters: Often left intact initially, as they contain protective factors, but some protocols suggest aspiration to remove fluid pressure. This decision is made by the treating physician.
- Topical Antibiotics: Application of topical antibiotic creams (e.g., silver sulfadiazine, bacitracin) to debrided or open wounds to prevent infection.
- Dressings: Apply sterile, non-adherent dressings, changing them regularly to keep the wound clean and moist.
- Elevation: Continue to elevate the affected feet to minimize swelling and improve venous drainage.
- Tetanus Prophylaxis: Administer tetanus toxoid if the patient’s vaccination status is uncertain or outdated.
- Keywords: frostbite wound care, blister debridement frostbite, infection prevention cold injury.
- Blister Management:
- Pharmacological Interventions:
- Vasodilators (e.g., Iloprost): Prostacyclin analogues like iloprost are often used in severe frostbite to improve microcirculation, prevent thrombosis, and reduce the need for amputation. They are potent vasodilators and anti-platelet agents.
- Thrombolytics (e.g., tPA): Tissue plasminogen activator (tPA) may be considered in very early, severe frostbite to break down clots in small vessels, but its use is controversial and high-risk, limited to specialized centers.
- NSAIDs: Non-steroidal anti-inflammatory drugs (e.g., ibuprofen) are used for pain and to reduce inflammation.
- Anticoagulants: Heparin may be used to prevent further thrombosis in severely affected vessels, although its routine use is debated.
- Keywords: iloprost frostbite treatment, tPA for frostbite, medication for cold injury.
- Surgical Management:
- Debridement of Necrotic Tissue: Surgical removal of dead tissue (eschar) is performed once the demarcation between viable and non-viable tissue is clear, which can take weeks to months.
- Fasciotomy: Rarely, if severe swelling leads to compartment syndrome (pressure build-up within muscle compartments), fasciotomy may be required to relieve pressure and save muscle.
- Amputation: If tissue necrosis is complete and irreversible, amputation of the affected toes or part of the foot may be necessary. This is typically delayed until complete demarcation has occurred to preserve as much healthy tissue as possible.
- Keywords: amputation frostbite feet, surgical debridement cold injury, compartment syndrome frostbite.
- Long-Term Care and Rehabilitation:
- Physical Therapy: Essential for restoring range of motion, strength, and function to the foot and toes.
- Occupational Therapy: To help patients adapt to any residual deficits and maintain independence.
- Chronic Pain Management: Many patients experience long-term sequelae such as neuropathic pain, paresthesias, hyperhidrosis (excessive sweating), and extreme sensitivity to cold. Chronic pain clinics and specialized therapies may be required.
- Psychological Support: Dealing with a severe injury, potential disfigurement, and loss of function can take a significant psychological toll, requiring counseling or support groups.
- Keywords: frostbite rehabilitation, chronic pain cold injury, cold sensitivity feet after frostbite.
The comprehensive nature of frostbite of the feet treatment underscores the severity of this condition and the meticulous care required for optimal patient outcomes. Early and appropriate intervention, guided by the specific presentation of foot frostbite symptoms pictures, significantly impacts recovery and reduces the risk of long-term disability.