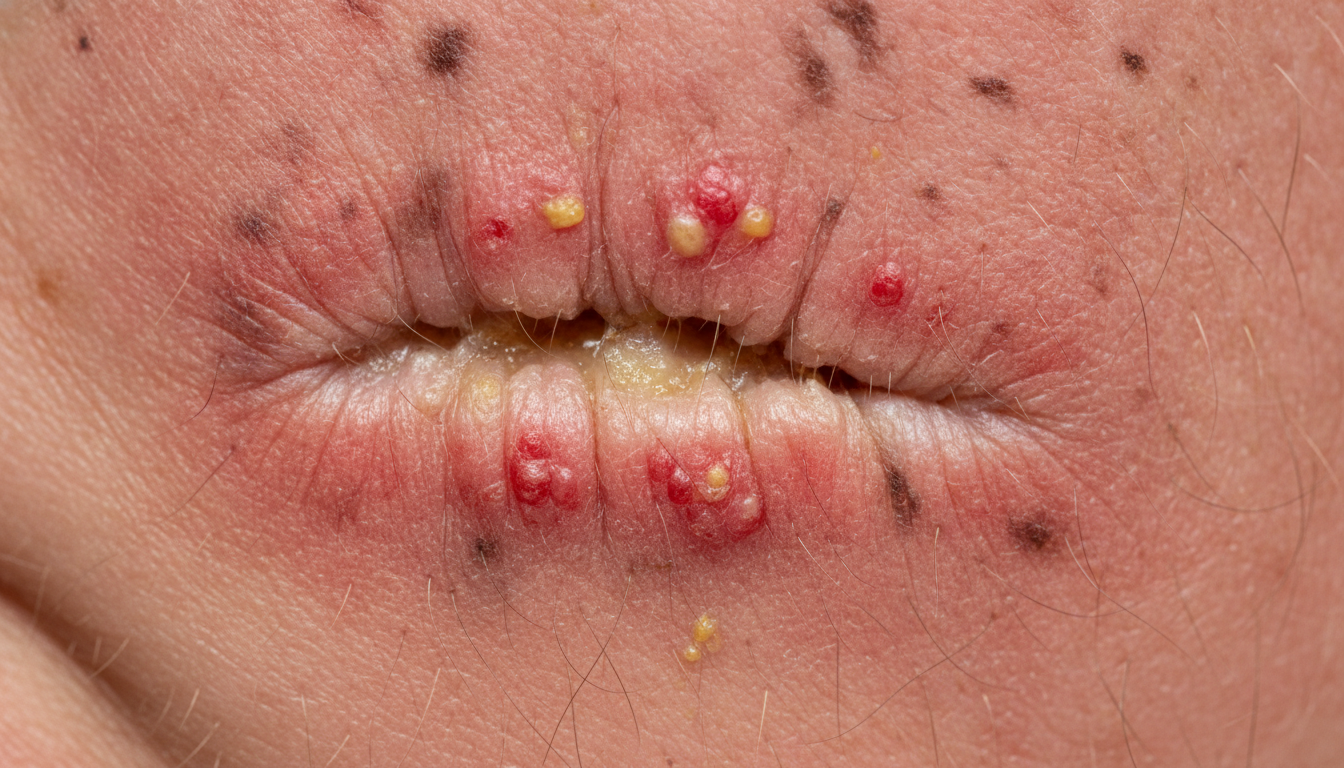
When examining Deep bite on the face symptoms pictures, it’s critical to understand the diverse dermatological presentations that can manifest as significant indentations or severe lesions. These visual cues are essential for early recognition and understanding the potential progression of the condition, guiding subsequent diagnostic and therapeutic steps.
Deep bite on the face Symptoms Pictures
The visual characteristics captured in Deep bite on the face symptoms pictures can vary widely, reflecting the underlying dermatological processes. Patients often present with a complex array of facial skin symptoms that can range from subtle discolorations to pronounced tissue loss. Understanding these varied manifestations is paramount for accurate assessment. Key symptoms include:
- Significant Indentations and Depressions: These are often the hallmark feature, appearing as distinct grooves, pits, or sunken areas on the facial skin. Their depth and width can vary, from shallow, broad depressions to deep, narrow furrows. The edges might be sharp, irregular, or sloping, providing clues about the etiology.
- Erythema and Inflammation: Affected areas frequently exhibit redness, ranging from a faint pink blush to an intense, fiery red. This erythema often signifies underlying inflammation, which may be accompanied by warmth to the touch and localized tenderness. The inflammation can extend beyond the immediate indentation, creating a surrounding halo.
- Edema and Swelling: Swelling of the surrounding facial tissues is a common symptom. This edema can obscure the true depth of the indentation and contribute to a puffy or distorted facial appearance. It may be diffuse or localized, sometimes creating tension in the skin.
- Pain and Tenderness: Patients frequently report localized pain or tenderness upon palpation of the affected areas. The pain can range from a dull ache to sharp, throbbing sensations, often exacerbated by touch, movement, or pressure.
- Discoloration Beyond Erythema:
- Hyperpigmentation: Darkening of the skin (brown, black, or grayish) can occur, particularly in chronic cases or post-inflammatory changes. This can be patchy or diffuse.
- Hypopigmentation: Lightening or complete loss of skin color can also be observed, indicating damage to melanocytes, especially in healing or chronic lesions.
- Lividity/Purpura: A bluish-red or purplish discoloration may suggest vascular compromise, extravasated blood, or deeper tissue damage.
- Texture Changes: The skin texture within and around the affected areas can be markedly altered. This includes:
- Induration: Hardening or thickening of the skin, making it less pliable.
- Atrophy: Thinning of the epidermis and/or dermis, leading to fragile, translucent skin.
- Sclerosis: Scar-like hardening and immobility of the skin.
- Roughness or Scaling: Surface irregularities and flaking of the skin.
- Associated Lesions:
- Papules and Plaques: Raised, solid lesions that may be small (papules) or larger, flattened (plaques).
- Nodules: Deeper, palpable solid lesions beneath the skin surface.
- Pustules: Small, pus-filled lesions, indicating infection or inflammatory processes.
- Vesicles/Bullae: Fluid-filled blisters, which can rupture and lead to erosions.
- Ulcerations: Open sores with loss of epidermis and dermis, often with a visible base and margins.
- Crusting: Dried exudate (serum, pus, blood) forming on the surface of weeping or eroded lesions.
- Fissures: Linear cracks in the skin, especially in areas of dryness or tension.
- Pruritus (Itching): While not always present, itching can be a significant and distressing symptom, potentially leading to excoriations and secondary infection.
- Numbness or altered sensation: Nerve involvement can lead to areas of decreased sensation or paresthesia.
- Scarring: As the condition resolves, various forms of scarring can develop, including atrophic (depressed), hypertrophic (raised), or keloidal scars. These scars can further alter facial contours and skin texture.
Each of these facial deep bite symptoms provides a piece of the puzzle, and their combination, distribution, and evolution over time are crucial for diagnosis. Detailed visual analysis of these skin lesions face photos is key for practitioners and patients alike.
Signs of Deep bite on the face Pictures
Observable Signs of Deep bite on the face Pictures offer objective evidence of the condition, allowing for consistent assessment and monitoring. These signs are what a clinician would actively seek during a physical examination and are critical for distinguishing various dermatological conditions presenting as deep facial marks. These signs include:
- Morphology of Indentations:
- Shape: Can be linear, punctate, stellate, irregular, or geographic.
- Size: Measured in millimeters or centimeters, providing an indication of severity.
- Depth: Crucial for diagnosis; can range from superficial epidermal depressions to deep dermal or subcutaneous tissue loss.
- Margins: Sharp, well-demarcated, rolled, undermined, or sloping, offering clues about the lesion’s nature.
- Base: Granular, necrotic, fibrinous, or purulent base in ulcers.
- Perilesional Skin Changes:
- Erythema: Redness extending from the primary lesion, indicating inflammation.
- Edema: Swelling of the surrounding tissues, contributing to skin tension.
- Lichenification: Thickening of the skin with exaggerated skin markings, often due to chronic scratching or rubbing.
- Excoriations: Linear abrasions caused by scratching, indicating pruritus.
- Dermatographism: An exaggerated whealing response to stroking the skin, observed in certain inflammatory conditions.
- Distribution Pattern:
- Localized: Confined to a specific area of the face (e.g., perioral, periorbital, malar).
- Diffuse: Spread across a broader facial area.
- Symmetrical vs. Asymmetrical: Bilateral involvement often points to systemic causes or widespread inflammation, while unilateral involvement may suggest localized trauma, infection, or specific dermatomal patterns.
- Linear: Suggests external cause (e.g., scratching, contactant) or follow a nerve/lymphatic distribution (e.g., Blaschko lines).
- Grouped/Clustered: Multiple lesions appearing in close proximity.
- Associated Dermatological Findings:
- Comedones: Blackheads or whiteheads, often indicating a follicular origin.
- Telangiectasias: Dilated small blood vessels visible on the skin surface, often associated with chronic inflammation or certain systemic diseases.
- Atrophy: Visible thinning of the epidermis or dermis, making underlying blood vessels more prominent.
- Sclerosis: Palpable hardening of the skin, indicative of fibrous tissue deposition.
- Pigmentary Alterations: Patches of hyperpigmentation or hypopigmentation, which can be post-inflammatory or indicative of specific conditions.
- Regional Lymphadenopathy: Swollen and tender lymph nodes in the neck or submandibular area can indicate an active infection or inflammatory process draining from the facial lesions. This is a crucial systemic sign.
- Systemic Signs (if present): While focusing on the skin, accompanying systemic signs such as fever, malaise, chills, or weight loss can point to a more widespread disease process contributing to the skin pathology face. However, the primary focus for Deep bite on the face pictures remains the cutaneous manifestations.
- Discharge or Exudate:
- Serous: Clear, watery fluid, often from ruptured vesicles or erosions.
- Purulent: Thick, yellowish or greenish pus, indicative of bacterial infection.
- Sanguineous: Bloody discharge, suggesting deeper tissue damage or vascular involvement.
- Fibrinous: Whitish-yellow, sticky exudate, often seen in chronic ulcers.
- Hair Involvement: Areas of alopecia (hair loss) within or around the lesions, or changes in hair texture (e.g., fragile, brittle hairs).
Each of these objective observable deep bite signs is meticulously documented to build a comprehensive clinical picture. The consistent documentation of these signs across various facial skin examination images supports effective diagnosis and management strategies for conditions manifesting as deep indentations skin.
Early Deep bite on the face Photos
Identifying Early Deep bite on the face Photos is paramount for prompt intervention and improved outcomes. The initial stages of conditions leading to significant facial indentations or severe lesions can be subtle, making early recognition a diagnostic challenge. These nascent changes often precede the more pronounced symptoms and signs. Key early indicators that might appear in initial presentations of deep bite on the face photos include:
- Subtle Erythema or Discoloration: The very first sign might be a faint, localized redness or a slight change in the skin’s natural tone. This could be a pale pink or a slightly darker patch compared to the surrounding healthy skin. It often indicates the onset of inflammation or vascular changes at a superficial level.
- Minor Induration or Firmness: A barely perceptible hardening or thickening of a small patch of skin, felt more than seen. This suggests early cellular infiltration or collagen deposition. The area might feel slightly firmer or less pliable to the touch.
- Localized Tenderness or Sensitivity: Patients may report a new, unexplained tenderness or increased sensitivity in a specific facial area, even before any visible lesion develops. This indicates early nerve involvement or inflammatory mediators activating pain receptors.
- Formation of Pinpoint Lesions:
- Macules: Small, flat, discolored spots (e.g., reddish or brownish) that are not raised or depressed.
- Papules: Tiny, raised, solid bumps, often just a few millimeters in diameter. These could be inflammatory papules or early follicular lesions.
- Vesicles: Small, clear fluid-filled blisters that can precede larger bullae or erosions. These suggest epidermal damage.
- Slight Texture Changes: The skin might feel subtly rougher, drier, or perhaps unusually smooth in a localized area. These changes can be indicative of epidermal dysfunction or early signs of atrophy.
- Focal Pitting or Dimpling: In some cases, a very fine, localized pitting or dimpling, almost like an exaggerated pore, can be an early indicator of collagen loss or early subcutaneous atrophy. These are often best observed under magnification.
- Transient Swelling: Episodes of mild, localized puffiness that may come and go, potentially related to early lymphatic dysfunction or intermittent inflammatory flares. This swelling might not be consistently present in all early deep bite symptoms photos but can be a key patient-reported symptom.
- Altered Skin Sheen: The affected area might exhibit a slightly different reflectivity or sheen compared to the adjacent normal skin, possibly appearing duller or shinier, indicating changes in skin hydration or surface topography.
- Minimal Purpura or Ecchymosis: Tiny areas of bleeding under the skin, appearing as small red or purple spots, suggesting early vascular fragility or micro-trauma.
- Asymptomatic Period: Crucially, some of these early changes might be entirely asymptomatic, making identification challenging without careful self-examination or clinical scrutiny. The patient might not experience pain or itching initially, and the visual change is the only indicator.
Recognizing these initial facial lesions requires careful observation and often a comparison with healthy surrounding skin. These onset facial skin changes are the critical window for intervention, where potential progression to more severe nascent deep bite marks can potentially be averted or significantly mitigated. Photographic documentation of these early stages is invaluable for tracking the natural history and response to initial therapies targeting deep bite on the face symptoms pictures.
Skin rash Deep bite on the face Images
When reviewing Skin rash Deep bite on the face Images, it’s essential to analyze the characteristics of any accompanying rash, as this can provide crucial diagnostic information. A rash associated with facial indentations can indicate a wide range of underlying dermatological conditions, from inflammatory to infectious or autoimmune processes. The morphology, distribution, and evolution of the rash are key. Types of rashes and their features include:
- Erythematous Rashes: Characterized predominantly by redness.
- Diffuse Erythema: Widespread, uniform redness across the affected facial area.
- Patchy Erythema: Areas of redness interspersed with normal or differently affected skin.
- Confluent Erythema: Patches of redness merging to form larger areas.
- Macular Erythema: Flat, red spots that are not palpable.
- Maculopapular Rashes: A combination of flat red spots (macules) and small, raised red bumps (papules).
- These can be widespread or localized around the areas of deeper indentation.
- Often seen in viral exanthems, drug reactions, or some forms of contact dermatitis.
- Papules may be skin-colored, erythematous, or slightly hyperpigmented.
- Vesicular and Bullous Rashes: Characterized by fluid-filled lesions.
- Vesicles: Small blisters (<0.5 cm) filled with clear fluid.
- Bullae: Larger blisters (>0.5 cm) filled with clear fluid.
- These rashes often indicate significant epidermal damage and can rupture, leading to erosions and crusting. Common in herpes simplex, varicella zoster, or some autoimmune blistering diseases.
- The fluid can be serous, hemorrhagic, or even purulent.
- Pustular Rashes: Characterized by pus-filled lesions.
- Pustules: Small, elevated lesions containing pus (whitish-yellow or greenish fluid).
- Often indicative of bacterial infection (e.g., folliculitis, impetigo) or inflammatory conditions like acne vulgaris or pustular psoriasis.
- May be associated with surrounding erythema and tenderness.
- Urticarial Rashes (Hives): Characterized by transient, intensely itchy, raised erythematous plaques (wheals).
- Individual lesions are often migratory, appearing and disappearing within hours.
- Suggests an allergic or hypersensitivity reaction, or mast cell degranulation.
- Can occur alongside deeper swelling (angioedema), which could contribute to a “deep bite” appearance.
- Purpuric and Petechial Rashes: Due to bleeding into the skin.
- Petechiae: Small, pinpoint, non-blanching red or purple spots.
- Purpura: Larger (>0.5 cm), non-blanching red or purple patches.
- Ecchymoses: Even larger bruise-like discolorations.
- Indicate vascular fragility, coagulopathy, vasculitis, or trauma. These discolorations can persist and deepen the appearance of an indentation.
- Reticular Rashes (Livedo Reticularis): A net-like or lace-like pattern of reddish-blue discoloration.
- Often indicates compromised blood flow in the superficial vasculature.
- Can be localized or widespread, and may be exacerbated by cold.
- Eczematous Rashes: Characterized by erythema, scaling, crusting, and often intense pruritus.
- May involve weeping (exudation of fluid) and lichenification in chronic stages.
- Often seen in contact dermatitis, atopic dermatitis, or seborrheic dermatitis.
- The chronic scratching associated with eczema can lead to excoriations and secondary indentations or scars.
- Annular or Polycyclic Rashes: Lesions forming rings or coalescing rings.
- The borders are often erythematous and raised, with central clearing.
- Seen in conditions like tinea corporis, erythema annulare centrifugum, or granuloma annulare.
- Distribution of Rash:
- Perioral: Around the mouth.
- Periorbital: Around the eyes.
- Malar: On the cheeks (e.g., “butterfly rash” in lupus).
- Diffuse: Covering the entire face or large facial segments.
- Follicular: Centered around hair follicles.
Each type of facial rash deep bite contributes unique information to the diagnostic process. The presence of a specific skin eruption face deep bite pattern, its relationship to the indentations, and its evolution over time are critical elements for understanding the underlying pathology. Carefully analyzing these details in deep bite associated rash images aids in differentiating conditions that may present similarly, such as inflammatory dermatoses, autoimmune disorders, or infections that can lead to significant facial skin changes, necessitating specific dermatitis deep bite face treatment approaches.
Deep bite on the face Treatment
Effective Deep bite on the face treatment strategies are multifaceted, aiming to address the underlying cause of the lesions and associated symptoms, promote healing, prevent complications, and minimize long-term scarring. Given the broad range of conditions that can present as significant facial indentations or severe lesions, treatment must be tailored to the specific diagnosis. It is crucial to consult with a dermatologist or healthcare professional for an accurate diagnosis and personalized treatment plan for managing deep bite symptoms. General categories of treatment include:
I. Topical Treatments:
These are applied directly to the skin and are often the first line of therapy for localized conditions.
- Topical Corticosteroids:
- Mechanism: Reduce inflammation, itching, and redness.
- Formulations: Creams, ointments, lotions, gels of varying strengths (e.g., hydrocortisone, triamcinolone, clobetasol).
- Use: For inflammatory conditions, eczema, contact dermatitis, or localized immune responses. Used cautiously on the face due to risk of skin thinning (atrophy), telangiectasias, and perioral dermatitis.
- Topical Antibiotics:
- Mechanism: Kill bacteria or inhibit their growth.
- Formulations: Creams, ointments (e.g., clindamycin, erythromycin, metronidazole, mupirocin, fusidic acid).
- Use: For bacterial infections (impetigo, folliculitis) or inflammatory conditions with a bacterial component (e.g., inflammatory acne).
- Topical Antifungals:
- Mechanism: Target fungal organisms.
- Formulations: Creams, powders (e.g., ketoconazole, clotrimazole, terbinafine).
- Use: For fungal infections (tinea faciei).
- Topical Antivirals:
- Mechanism: Inhibit viral replication.
- Formulations: Creams (e.g., acyclovir, penciclovir).
- Use: For localized viral infections like herpes simplex.
- Calcineurin Inhibitors (Non-steroidal Immunomodulators):
- Mechanism: Suppress the local immune response without steroid side effects.
- Formulations: Creams, ointments (e.g., tacrolimus, pimecrolimus).
- Use: For inflammatory conditions like atopic dermatitis or facial eczema, particularly where long-term steroid use is undesirable.
- Emollients and Moisturizers:
- Mechanism: Hydrate and protect the skin barrier, reducing dryness and irritation.
- Formulations: Lotions, creams, ointments (petrolatum-based, ceramide-rich).
- Use: Essential supportive care for most skin conditions, especially those with barrier dysfunction or dryness.
- Wound Care Dressings:
- Mechanism: Protect open wounds, maintain a moist healing environment, absorb exudate.
- Types: Hydrocolloids, hydrogels, alginates, foam dressings.
- Use: For ulcerated or severely eroded lesions to promote granulation and epithelization.
II. Systemic Treatments:
These medications are taken orally or by injection, acting throughout the body for more widespread or severe conditions.
- Oral Antibiotics:
- Mechanism: Eradicate systemic bacterial infections.
- Examples: Doxycycline, minocycline, cephalexin, clindamycin.
- Use: For severe bacterial infections (cellulitis, erysipelas), extensive acne, or inflammatory conditions with a significant bacterial component.
- Oral Antivirals:
- Mechanism: Systemically inhibit viral replication.
- Examples: Acyclovir, valacyclovir, famciclovir.
- Use: For widespread or severe viral infections (herpes zoster, extensive herpes simplex).
- Oral Antifungals:
- Mechanism: Systemically treat fungal infections.
- Examples: Fluconazole, itraconazole, terbinafine.
- Use: For extensive or recalcitrant fungal infections (tinea faciei).
- Oral Corticosteroids:
- Mechanism: Potent anti-inflammatory and immunosuppressive effects.
- Examples: Prednisone.
- Use: For severe inflammatory conditions (e.g., severe eczema, autoimmune flares), often for short courses to gain control before transitioning to topical or other systemic agents.
- Immunosuppressants/Immunomodulators:
- Mechanism: Modulate the immune system to reduce inflammation or prevent autoimmune attacks.
- Examples: Methotrexate, cyclosporine, azathioprine, biologics (e.g., TNF-alpha inhibitors).
- Use: For severe autoimmune diseases (e.g., lupus, bullous pemphigoid, vasculitis) or chronic inflammatory conditions not responsive to other therapies.
- Retinoids (Oral):
- Mechanism: Affect cell growth and differentiation, reduce sebum production, anti-inflammatory.
- Example: Isotretinoin.
- Use: For severe recalcitrant acne that may cause deep scarring or indentations.
III. Procedural and Device-Based Treatments:
These interventions are performed by healthcare professionals.
- Incision and Drainage (I&D):
- Use: For abscesses, cysts, or severe pustules to release pus and reduce pressure.
- Benefits: Provides immediate relief, promotes healing, and allows for culture to guide antibiotic choice.
- Cryotherapy:
- Mechanism: Freezing with liquid nitrogen to destroy abnormal tissue.
- Use: For benign lesions, warts, or some precancerous lesions that may contribute to textural changes.
- Laser Therapy:
- Types: Ablative (CO2, Er:YAG), non-ablative, pulsed dye lasers.
- Use:
- Resurfacing: To improve texture, appearance of scars (atrophic, hypertrophic) and deep indentations.
- Vascular Lesions: To target redness or telangiectasias.
- Pigmentary Lesions: To address hyperpigmentation.
- Chemical Peels:
- Mechanism: Application of chemical solutions to exfoliate outer skin layers, promoting regeneration.
- Use: To improve skin texture, mild scarring, and pigmentary issues.
- Dermal Fillers:
- Mechanism: Injectable substances (e.g., hyaluronic acid, collagen stimulators) to fill depressed scars or indentations.
- Use: For cosmetic improvement of deep atrophic scars or volume loss.
- Subcision:
- Mechanism: A needle is inserted under the skin to break fibrotic strands tethering a scar to deeper tissue, allowing the skin to rise.
- Use: For depressed, rolling scars to release tension and allow for more even contour.
- Excisional Biopsy/Surgical Excision:
- Use: For diagnosis of suspicious lesions, removal of persistent or problematic lesions (cysts, deep nodules, some scars).
IV. Supportive Care and Lifestyle Modifications:
- Gentle Skin Care: Using mild cleansers, avoiding harsh scrubs or irritants.
- Sun Protection: Crucial for preventing post-inflammatory hyperpigmentation and protecting healing skin. Use broad-spectrum sunscreens (SPF 30+).
- Avoidance of Triggers: Identifying and avoiding allergens, irritants, or exacerbating factors.
- Nutrition and Hydration: A balanced diet and adequate fluid intake support overall skin health and healing.
- Stress Management: Stress can exacerbate many dermatological conditions.
- Scar Management: Silicone sheets/gels, massage, and early intervention to minimize hypertrophic or keloidal scarring after wound healing.
The management of conditions causing deep bite facial treatment issues often requires a multidisciplinary approach, involving dermatologists, plastic surgeons, and potentially other specialists depending on the underlying cause. Continuous monitoring and adjustment of the treatment plan are essential for optimizing outcomes and addressing evolving symptoms for managing deep bite symptoms effectively. Patients should follow medical advice diligently to achieve the best possible results in dealing with skin lesion treatment face.