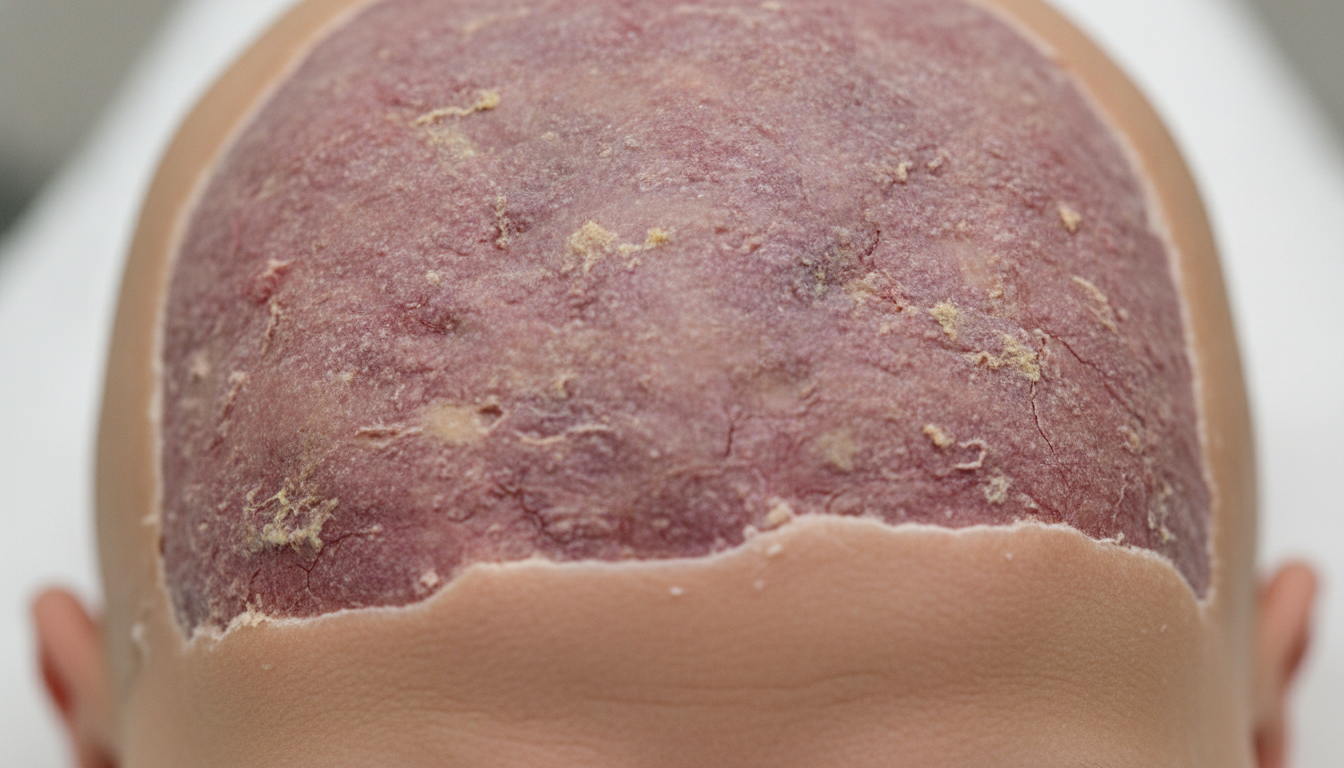
This detailed guide provides an essential visual understanding through Anencephaly symptoms pictures, aiding in the recognition of this severe neural tube defect. We present comprehensive descriptions of the unique physical characteristics associated with anencephaly, highlighting critical features for identification and offering insights into the observable manifestations of this condition.
Anencephaly Symptoms Pictures
The visual presentation of anencephaly is characterized by profound cranial anomalies, offering distinct Anencephaly symptoms pictures that are critical for diagnosis and understanding. These images typically showcase the absence of significant portions of the skull and brain, particularly the cerebrum and cerebellum. The most striking symptom visible in anencephaly pictures is the severe malformation of the head, which is often described as lacking the typical rounded cranial vault. Instead, the exposed neural tissue is visible, often appearing as a reddish, irregular mass. The absence of the forebrain and a substantial part of the skull is the defining feature, leading to a characteristic appearance that is immediately recognizable in diagnostic images and photographs of affected infants.
When examining Anencephaly symptoms pictures, several key visual cues stand out, providing a comprehensive understanding of the condition’s impact on fetal development. The affected infant’s head shape is dramatically altered, often appearing flattened or truncated above the orbits. The eyes may seem unusually prominent or bulging due to the lack of cranial coverage above them. Facial features can also be affected, sometimes displaying dysmorphic characteristics, though the primary anomaly remains the cranial defect. Neck abnormalities, such as a very short or absent neck, are also commonly observed, contributing to the overall unusual profile of the infant. The exposure of the brainstem and other rudimentary neural tissue makes the condition visually distinct and underscores its severity.
Detailed analysis of Anencephaly symptoms pictures reveals a consistent pattern of severe cranial malformation. The exposed brain tissue is often covered by a vascular membrane, sometimes appearing macerated or ulcerated, particularly if exposed to amniotic fluid for extended periods in utero. This unprotected tissue is highly fragile and prone to damage, contributing to the distinct visual characteristics. The absence of the frontal bone and parietal bones is typical, leaving the underlying neural structures directly exposed. These visual markers are crucial for prenatal screening and postnatal confirmation, offering irrefutable evidence of the neural tube defect.
Commonly observed visual symptoms in Anencephaly symptoms pictures include:
- Absence of the Cranial Vault: The most significant and universally present symptom. The top of the skull is not formed, leaving the brain exposed. This is clearly depicted in any anencephaly visual signs.
- Exposed Neural Tissue: Brain tissue, often rudimentary and malformed, is directly visible. It may appear reddish, gelatinous, or covered by a vascular membrane, distinguishing it from normal scalp tissue. This is a hallmark of open neural tube defect imaging.
- Prominent, Bulging Eyes (Exophthalmia): Due to the lack of a forehead and cranial bones above the orbits, the eyes often appear unusually large and protruding. This contributes to the “frog-like” facial appearance often mentioned in descriptions of anencephaly facial features.
- Absence of Forehead: The forehead bone is typically missing, leading to a very short or non-existent forehead. This severe cranial malformation alters the entire upper facial structure.
- Short or Absent Neck: The neck region can be severely underdeveloped or seem to merge directly with the torso, giving the appearance of a very short or no neck. This can be seen in lateral views of anencephaly pictures at birth.
- Low-Set Ears: Ears may be positioned lower than normal on the head, another indicator of widespread facial and cranial dysmorphism. This is a common finding in congenital anomaly imaging.
- Macroglossia or Micrognathia (less common but possible): While not primary, other facial anomalies like an unusually large tongue or a very small jaw can sometimes be present as associated findings, influencing the overall facial presentation in anencephaly birth defects photos.
- Facial Clefts (rare but observed): Cleft lip or palate can occasionally occur concurrently with anencephaly, further complicating the visual manifestation. These are considered associated findings in severe fetal malformation images.
- Polyhydramnios (indirect symptom): While not directly visible on the infant, severe polyhydramnios (excess amniotic fluid) in the mother is a common indirect symptom visible in prenatal ultrasound images, as the fetus with anencephaly cannot properly swallow amniotic fluid. This is important for understanding the context of anencephaly prenatal diagnosis.
Signs of Anencephaly Pictures
The Signs of Anencephaly Pictures offer a profound visual narrative of this devastating neural tube defect. These images consistently reveal a specific constellation of physical characteristics that are diagnostic markers. A central sign is the complete or partial absence of the cerebrum and cerebellum, coupled with the lack of the overlying skull bones (acrania). The remaining brainstem and vascular tissue are typically exposed, giving the cephalic region a distinct, often raw or reddish appearance. This exposed tissue, bereft of protective bone and skin, is highly vulnerable and defines the core visual pathology. The “frog-like” appearance of the head, characterized by prominent eyes and a truncated cranial vault, is a consistent visual sign that aids in immediate recognition.
Detailed examination of Signs of Anencephaly Pictures often highlights additional facial dysmorphism directly attributable to the severe cranial defect. The orbits can appear shallow or displaced, contributing to the exophthalmia (bulging eyes). The ears may be rotated or low-set. The overall facial structure appears compressed or altered due to the severe absence of the upper skull. The lack of a neck or a very short neck, combined with low-set shoulders, contributes to a compact appearance of the head and upper torso. These visual signs are not merely symptoms but definitive diagnostic indicators that confirm the presence of anencephaly. The stark contrast between the exposed neural tissue and the intact facial structures below the orbits is a signature element visible in these critical images.
Furthermore, Signs of Anencephaly Pictures may sometimes reveal associated anomalies, though anencephaly itself is the predominant and most severe. These could include minor spinal defects (like spina bifida occulta, which is often not externally visible but can be associated), or less commonly, limb abnormalities. The critical aspect of observing these signs is their consistent presence across various photographs, confirming a predictable pattern of severe malformation. The absence of the bony skull, along with the exposed, undeveloped brain tissue, creates an image that leaves no doubt regarding the diagnosis of this severe congenital condition. The vascular nature of the exposed brain tissue often gives it a distinct coloration, ranging from bright red to dark purplish hues, further emphasizing the raw and unprotected state of the neural structures.
Key observable signs in Signs of Anencephaly Pictures include:
- Acrania and Anencephaly: The simultaneous absence of the skull vault (acrania) and the cerebrum/cerebellum (anencephaly) is the primary sign. This structural defect is central to understanding anencephaly diagnosis imaging.
- Exposed Brainstem and Neural Tissue: The presence of an exposed brainstem and other rudimentary neural tissues, often appearing discolored or covered by a fragile membrane, is a definitive sign. This is a critical visual aspect in anencephaly severe birth defects.
- Orbital Prominence (Exophthalmos): The eyes are strikingly prominent, often appearing to bulge outwards, largely due to the absence of the frontal bone and surrounding cranial structures. This creates the characteristic anencephaly “frog-like” appearance.
- Absence of Forehead and Top of Head: The skull defect extends from the orbital ridges upwards, resulting in no identifiable forehead or upper head structure. This is a distinguishing feature in anencephaly external features.
- Abnormal Ear Position: Ears may be unusually low-set or rotated, indicating a broader pattern of cephalic malformation. This is a subtle but consistent sign in congenital brain malformation photos.
- Micrognathia (small jaw) or Retrognathia (recessed jaw): While not universal, these jaw anomalies can occur and contribute to the overall facial dysmorphism seen in some anencephaly cases pictures.
- Short or Absent Neck: The lack of a distinct neck, where the head appears to sit directly on the shoulders, is a common and easily identifiable sign. This affects the overall profile in anencephaly profile views.
- Rudimentary Cranial Structures: In some instances, very small, underdeveloped remnants of cranial bones may be present, typically around the base of the skull, but never forming a complete vault. This demonstrates the spectrum of anencephaly cranial defects.
- Vascularized Membrane Covering Defect: The exposed brain tissue is frequently covered by a thin, reddish, highly vascularized membrane rather than skin, which is clearly visible in close-up anencephaly lesion images.
- Neurological Impairment (implied by visuals): Although not directly a visual sign, the visible absence of the cerebrum inherently signals profound neurological impairment, indicating the non-viability of life. This understanding underlies the interpretation of anencephaly life expectancy discussions.
Early Anencephaly Photos
Early Anencephaly Photos, typically captured immediately after birth or through advanced prenatal imaging, vividly illustrate the severe developmental anomalies associated with this condition. These initial images are crucial for parental understanding and clinical documentation. At birth, the profound cranial defect is immediately apparent, showcasing the absence of the major portion of the skull vault and the exposed, malformed brain tissue. The infant’s appearance is often shocking to unprepared observers due to the dramatic alteration of the head and face. The exposed neural structures, which comprise rudimentary brainstem and vascularized membranes, typically appear reddish, dark, or hemorrhagic, often lacking a protective layer of skin or bone. The overall impression in these early photos is one of profound and undeniable malformation, emphasizing the severity of the neural tube closure failure.
In Early Anencephaly Photos, the characteristic “frog-like” facies is frequently prominent. This appearance stems from the absence of the frontal bone and a portion of the parietal bones, causing the orbits to appear shallow and the eyes to protrude significantly (exophthalmia). The absence of a forehead contributes to a very short or nonexistent cranial profile above the eyes. The exposed neural tissue can vary in size and texture but consistently lacks the organized structure of a developed brain. It might appear as a raw, irregular mass of tissue, often covered by a fragile, vascular membrane. These early images are vital for conveying the full extent of the anatomical defects and for initiating appropriate comfort care protocols.
The immediacy and starkness of Early Anencephaly Photos help to quickly establish the diagnosis and prepare families for the grim prognosis. The defect is clearly visible, usually extending from the orbital ridges upwards, with the spinal cord often exposed at the base of the skull. The coloring of the exposed tissue can vary depending on its vascularity and any postnatal environmental exposure, but it consistently differs from normal skin. These early visual documentations are not just clinical records but also profoundly impactful images for families, often serving as their first and only visual encounter with their child’s condition. They underscore the critical need for compassionate care and support for families facing this diagnosis, emphasizing the importance of respecting the dignity of the infant regardless of the severity of the malformation.
Key features observed in Early Anencephaly Photos include:
- Immediate Visual Recognition: The condition is instantly recognizable at birth due to the severe cranial malformation. These images are foundational for neonatal anencephaly appearance.
- Exposed Neural Plate/Tissue: The neural plate, which failed to close and differentiate into the cerebrum, is exposed and often appears as a reddish-brown, irregular mass. This is a primary visual feature in early birth defects photos.
- Absence of Cranial Bones: Most of the skull bones, particularly the frontal, parietal, and parts of the occipital bones, are absent, leaving the brain unprotected. This is clearly visible in anencephaly structural anomaly images.
- Prominent Eyes: Due to the lack of cranial development above the orbits, the eyes appear strikingly large and protruding from their sockets. This contributes to the distinctive anencephaly infant facial features.
- Absence of Forehead: There is no discernible forehead, and the cranial defect begins abruptly above the eye sockets. This starkly alters the anencephaly head shape at birth.
- Vascularized Membrane: The exposed neural tissue is often covered by a thin, delicate, highly vascularized membrane rather than skin. This membrane may appear raw or hemorrhagic. This is evident in close-up anencephaly exposed tissue pictures.
- Short or Absent Neck: The lack of a fully developed neck means the head appears to rest directly on the shoulders, creating a compressed upper torso appearance. This can be seen in full-body anencephaly early photos.
- Macerated Appearance: In some cases, prolonged exposure to amniotic fluid in utero can lead to a macerated or somewhat degraded appearance of the exposed neural tissue. This is a common finding in anencephaly fetal images.
- Rudimentary Brainstem: While the cerebrum is largely absent, the brainstem is often partially present and visible, which is crucial for the very limited reflexes and survival instincts exhibited. This informs the understanding of anencephaly neurological manifestations.
- Associated Anomalies (less common visually): While not always externally obvious, other developmental issues might be present (e.g., congenital heart defects, though less frequently visible in external early photos). These are considered in a broader context of anencephaly congenital anomalies.
Skin rash Anencephaly Images
When discussing Skin rash Anencephaly Images, it is critical to clarify that anencephaly does not present with a typical “skin rash” in the dermatological sense. Instead, the term likely refers to the profound absence of skin and scalp over the major cranial defect, exposing underlying neural and meningeal tissues. What might be perceived as a “rash” is actually the raw, unprotected, and often discolored surface of the exposed brainstem, rudimentary brain tissue, and associated vascular membranes. These tissues are not covered by epidermis or dermis, making them appear distinctively different from healthy skin. The absence of normal integumentary coverage is the defining characteristic in this context, revealing fragile, vascular, and sometimes ulcerated tissue that is exposed to the external environment. This specific visual presentation is a core aspect of anencephaly visual assessment.
The appearance in Skin rash Anencephaly Images is often one of a raw, reddish, or dark purplish area where the scalp and skull should be. This exposed region is highly vulnerable to drying, infection, and mechanical trauma. The tissue can appear gelatinous, granular, or even necrotic in some areas, depending on the duration of exposure and environmental factors. It is essential to distinguish this from inflammatory skin conditions; in anencephaly, there is a fundamental absence of the skin barrier, leading to direct visualization of the underlying neural structures. This visual manifestation highlights the severe anatomical deficit and the complete lack of protective layers over the crucial neural components. Any secondary changes, such as infection or desiccation, might alter the appearance further, potentially leading to visual cues that an uninformed observer might misinterpret as a type of lesion or compromised skin condition.
In certain Skin rash Anencephaly Images, the exposed tissue might show signs of maceration, particularly if there was prolonged exposure to amniotic fluid in utero. Postnatally, without meticulous care, the exposed surfaces can quickly become dry, cracked, or infected, leading to further discoloration and textural changes. A pseudomembrane might form over the exposed area as a result of tissue exudation and drying. This compromised integumentary integrity is not a “rash” but a direct consequence of the neural tube defect where normal epidermal and dermal layers failed to develop or close over the malformed brain. Understanding this distinction is vital for accurate clinical description and for interpreting photographs of affected infants, ensuring that the visual findings are correctly attributed to the primary congenital anomaly rather than a secondary skin disease.
Characteristics of the exposed tissue in Skin rash Anencephaly Images (or rather, images depicting exposed cranial tissue) include:
- Absence of Scalp and Skin: The fundamental characteristic is the complete lack of normal epidermis and dermis over the affected cranial area, leaving underlying structures exposed. This is the primary feature of anencephaly scalp defects.
- Exposed Neural Tissue Appearance: The visible tissue is typically rudimentary brainstem, vascular structures, and meninges, appearing reddish, purple, or dark. It can be raw, irregular, and granular. This defines anencephaly exposed brain images.
- Vascular and Fragile: The exposed surface is often highly vascularized and extremely fragile, prone to bleeding or damage upon contact. This fragility is a key aspect of anencephaly tissue vulnerability.
- Maceration or Desiccation: Depending on prenatal and postnatal exposure, the tissue might appear macerated (softened and degraded by fluid) or desiccated (dried and cracked). These appearances can be seen in fetal tissue exposure photos.
- Ulceration and Necrosis: Due to lack of protection and potential infection, areas of the exposed tissue may develop ulcers or show signs of necrosis (tissue death). These are secondary changes visible in anencephaly lesion photography.
- Pseudomembrane Formation: A grayish or yellowish pseudomembrane can form over the exposed neural tissue due to exudation and drying, which might superficially resemble a “crust” on a rash. This contributes to the complex visual in anencephaly compromised skin images.
- Absence of Hair Follicles: Normal scalp hair is absent over the exposed area, further distinguishing it from typical skin. This contributes to the distinct visual in anencephaly hair pattern anomalies.
- Susceptibility to Infection: The unprotected neural tissue is highly susceptible to bacterial or fungal infections, which can lead to purulent discharge and further discoloration. Signs of infection are visible in anencephaly infection visual cues.
- Differentiation from True Rashes: It is crucial to understand that this is a structural absence and exposure, not an inflammatory dermatological condition like eczema or dermatitis. This is key for correctly interpreting anencephaly clinical presentation.
- Variability in Appearance: The exact visual presentation can vary depending on the extent of the defect, gestational age at birth, and immediate postnatal care, ranging from a moist, raw surface to a dry, crusted area. This impacts how anencephaly visual symptoms are perceived.
Anencephaly Treatment
The term Anencephaly Treatment primarily refers to comprehensive palliative and comfort care, as anencephaly is a universally fatal condition. There is no medical or surgical intervention that can repair the severe neurological damage or allow long-term survival. Therefore, the focus of care shifts entirely to providing dignity, comfort, and support to the infant and their family from diagnosis through the precious, albeit short, time they may have together. This approach is centered on ensuring the infant experiences no pain, is kept warm, and is handled gently, while simultaneously offering profound emotional and psychological support to the parents and family members. It is a holistic approach aimed at facilitating a peaceful transition for the infant and aiding the family through immense grief. The objective is to maximize comfort and minimize distress for the infant, while supporting the family in creating meaningful memories.
Palliative care for an infant with anencephaly encompasses a range of gentle interventions designed to maintain comfort. This includes ensuring proper warmth, providing gentle hydration (often through gavage feeding or small sips if able to swallow, but avoiding aggressive nutritional support), and maintaining hygiene of the exposed neural tissue to prevent infection and discomfort. Respiratory support is usually minimal, as the brainstem often functions enough to allow some rudimentary breathing, but aggressive ventilation is typically avoided as it is not beneficial for long-term survival and may prolong suffering. The primary goal is to manage any discomfort, such as agitation or potential pain, using appropriate medications if necessary, focusing on the infant’s quality of life during their limited time. This gentle approach is central to all aspects of anencephaly comfort measures.
Beyond direct infant care, Anencephaly Treatment extends significantly to bereavement support for the family. This includes counseling, psychological support, and facilitating opportunities for parents to bond with their child, create memories (e.g., photos, handprints, footprints), and say goodbye in a supportive environment. Spiritual care, social work services, and connections to support groups are also crucial components. Furthermore, genetic counseling and discussions about future pregnancy planning, including the importance of folic acid supplementation, are integral parts of the post-diagnosis and post-delivery care. The emphasis is on honoring the infant’s life, supporting the family’s grief process, and providing them with resources for healing and moving forward, including detailed information on anencephaly prevention strategies for subsequent pregnancies. The comprehensive care model recognizes the profound impact of this diagnosis on the entire family unit.
Key components of Anencephaly Treatment include:
- Palliative and Comfort Care: The cornerstone of management, focusing on ensuring the infant’s comfort, warmth, and dignity. This is the primary form of anencephaly medical care.
- Warmth Maintenance: Ensuring the infant is kept warm through appropriate swaddling, blankets, or incubators to prevent hypothermia. This is a basic anencephaly nursing care practice.
- Gentle Hydration: Providing small amounts of fluid, either orally (if the infant has a swallow reflex) or via gavage, to prevent severe dehydration without aggressive feeding. This supports anencephaly supportive care.
- Hygiene of Exposed Tissue: Gentle cleaning and protection of the exposed neural tissue to minimize discomfort, prevent infection, and maintain integrity as much as possible. This involves delicate anencephaly wound care, though it’s an open defect.
- Pain and Discomfort Management: Administering appropriate medications (e.g., opioids for pain, benzodiazepines for agitation) to ensure the infant is free from distress, if needed. This is critical for anencephaly end-of-life care.
- Avoidance of Aggressive Interventions: Refraining from heroic or invasive medical procedures (e.g., ventilators, feeding tubes, surgeries) that would not change the prognosis and could prolong suffering. This aligns with anencephaly ethical considerations.
- Family Bonding and Memory Making: Facilitating opportunities for parents to hold, touch, and spend time with their infant, and to create tangible memories (photos, handprints, footprints). This is vital for anencephaly bereavement support.
- Emotional and Psychological Support: Providing counseling, psychological services, and support groups for parents and family members to cope with grief and loss. This is a critical aspect of anencephaly family support.
- Spiritual and Cultural Support: Respecting and supporting the family’s spiritual, religious, and cultural practices surrounding birth, death, and remembrance. This ensures holistic anencephaly holistic care.
- Genetic Counseling: Offering counseling to parents about the recurrence risk of neural tube defects in future pregnancies and the importance of folic acid supplementation. This is key for anencephaly prevention discussions.
- Folic Acid Supplementation: Recommending preconception and early pregnancy folic acid supplementation (typically 400-800 mcg daily for low risk, up to 4 mg for high risk) to reduce the risk of future neural tube defects. This is a primary anencephaly preventive measure.
- Post-mortem Options: Discussing options such as autopsy for diagnostic confirmation or research, and organ donation (though rarely feasible due to the nature of the defect and short survival). These are part of comprehensive anencephaly post-delivery options.