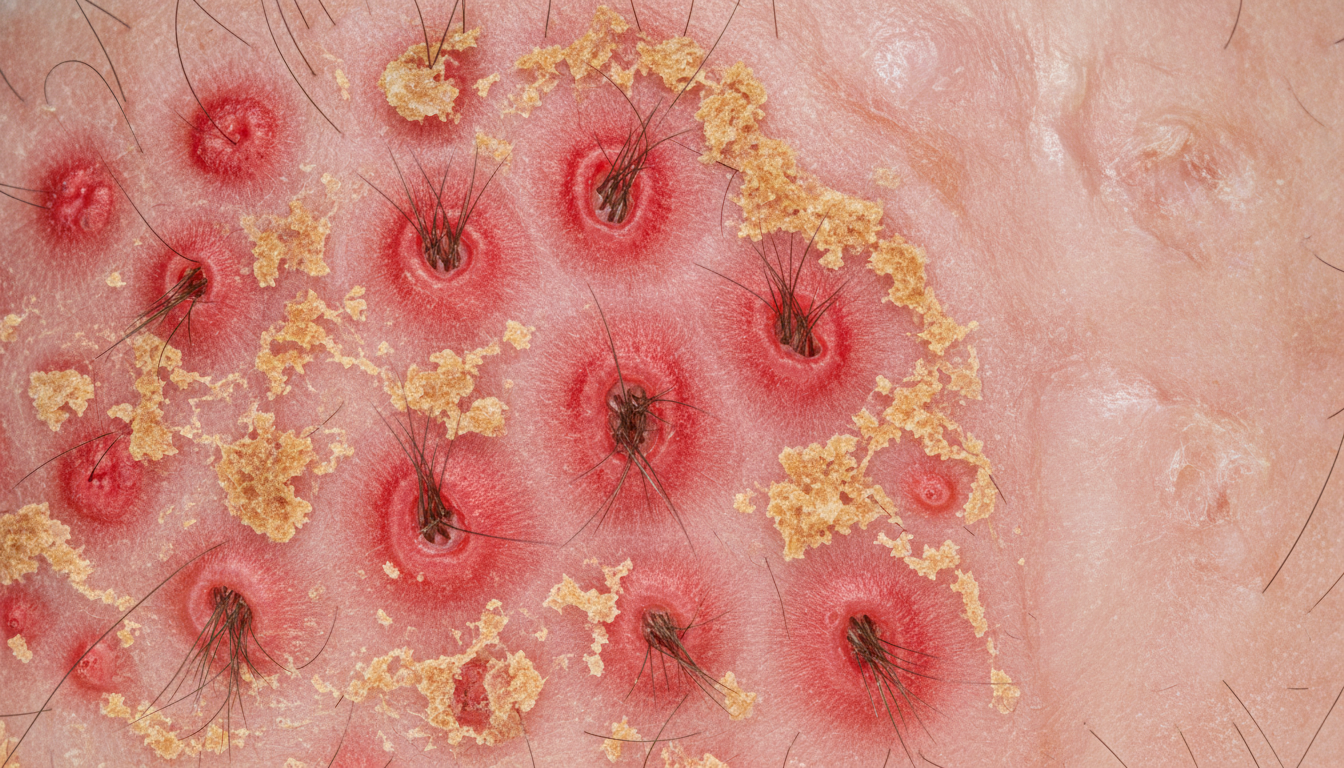
Understanding the visual presentation of various hair loss conditions is crucial for early detection and appropriate management. This comprehensive guide details common alopecia symptoms pictures, providing insights into the diverse appearances of hair loss and associated scalp changes. Explore distinct patterns, early indicators, and accompanying skin manifestations to better identify different forms of alopecia.
Alopecia Symptoms Pictures
Delving into alopecia symptoms pictures reveals a wide spectrum of visual manifestations, each indicative of specific underlying conditions. The appearance of hair loss can vary dramatically, from well-defined circular patches to diffuse thinning across the entire scalp. Observing the characteristics of hair loss and the accompanying scalp features is paramount for a preliminary understanding of the type of alopecia present. These visual cues serve as critical diagnostic markers, guiding individuals and healthcare professionals in distinguishing between non-scarring and scarring alopecias, temporary versus permanent hair loss, and inflammatory versus non-inflammatory conditions.
Specific visual patterns of hair loss often correspond to different alopecia types:
- Alopecia Areata (AA) Patterns:
- Patchy Hair Loss: Commonly observed as one or more discrete, coin-sized to larger, completely smooth, non-scarring patches on the scalp. The skin within these patches appears normal, without redness, scaling, or inflammation. The edges of the patches are often sharp and well-demarcated.
- Ophiasis Pattern: Characterized by hair loss in the shape of a band, typically affecting the temporal and occipital regions of the scalp, forming a wave-like pattern around the periphery.
- Sisaipho Pattern: The reverse of ophiasis, showing diffuse hair loss over the entire scalp but sparing the temporal and occipital regions.
- Alopecia Totalis (AT): Complete loss of hair on the entire scalp, leading to a completely bald head with no regrowth in sight. The scalp remains smooth and appears healthy.
- Alopecia Universalis (AU): The most severe form, involving complete loss of all body hair, including scalp hair, eyebrows, eyelashes, facial hair, and body hair. The skin everywhere appears normal.
- Diffuse Alopecia Areata (DAA): A less common variant presenting as diffuse thinning across the scalp, mimicking androgenetic alopecia or telogen effluvium, but often with underlying features of AA visible upon close inspection, such as exclamation mark hairs.
- Androgenetic Alopecia (AGA) / Pattern Hair Loss Patterns:
- Male Pattern Baldness: Typically starts with a receding hairline, forming an M-shape, followed by thinning on the crown (vertex). Over time, these areas may expand and merge, leading to extensive baldness. The remaining hair often forms a horseshoe pattern around the sides and back of the head.
- Female Pattern Hair Loss (FPHL): Manifests as diffuse thinning, primarily affecting the crown and frontal scalp, often with preservation of the frontal hairline (Christmas tree pattern or widening of the central part). The density of hair decreases progressively, making the scalp more visible through the hair.
- Telogen Effluvium (TE) Patterns:
- Diffuse Thinning: Characterized by widespread, generalized thinning across the entire scalp. There are no specific bald patches; instead, the overall hair density is reduced, and the scalp becomes more visible. The hair loss is often sudden and noticeable, especially during brushing or washing. The scalp appears normal, without inflammation or scarring.
- Acute Telogen Effluvium: Presents as a sudden, marked increase in daily hair shedding, often occurring 2-4 months after a trigger event.
- Chronic Telogen Effluvium: Involves prolonged or recurrent diffuse hair shedding lasting more than 6 months.
- Traction Alopecia Patterns:
- Hairline Recession: Primarily affects the frontal and temporal hairlines, presenting as thinning or baldness along the areas subjected to constant pulling forces. This is commonly seen in individuals who wear tight hairstyles like braids, ponytails, or dreadlocks.
- Broken Hairs and Follicular Inflammation: Early stages may show redness, small bumps (folliculitis), and broken hairs along the affected hairline. Chronic traction can lead to permanent hair loss due to follicular destruction and scarring.
- Scarring Alopecias (Cicatricial Alopecias) Patterns:
- Irregular Patches of Hair Loss: Characterized by patches of hair loss where the scalp skin appears smooth, shiny, and often lacking follicular openings. There may be associated redness, scaling, or pustules at the margins of active lesions.
- Folliculitis Decalvans (FD): Presents with pustules, crusting, and matted hair in affected areas, often with multiple hair shafts emerging from a single follicular opening (tufted folliculitis). The central areas show scarring and permanent hair loss.
- Lichen Planopilaris (LPP): Manifests as perifollicular erythema (redness around hair follicles) and fine scale, often with a subtle violaceous hue. This progresses to irreversible hair loss with noticeable scarring and loss of follicular ostia.
- Discoid Lupus Erythematosus (DLE): Hair loss patches are often erythematous, scaly, hyperpigmented or hypopigmented, with follicular plugging and eventual atrophic scarring. Hair follicles are permanently destroyed.
- Central Centrifugal Cicatricial Alopecia (CCCA): Typically begins on the crown or vertex of the scalp and expands outwards in a centrifugal pattern. Initially, there might be subtle inflammation, itching, and tenderness, progressing to permanent hair loss with smooth, shiny, atrophic scarring and loss of follicular openings.
- Trichotillomania (TTM) Patterns:
- Irregularly Shaped Patches: Hair loss patches are typically irregular in shape, with varying lengths of broken hairs and often some regrowth. The distribution is usually asymmetric, corresponding to areas reachable by the individual’s hands.
- Associated Features: May include excoriations (scratch marks), erythema, or crusting due to self-inflicted trauma. There are no smooth, completely bald areas like in alopecia areata.
Observing the scalp’s appearance within and around the hair loss areas is equally vital:
- Normal-appearing scalp: Common in non-scarring alopecias like alopecia areata, telogen effluvium, and androgenetic alopecia, where the skin color and texture are healthy, and follicular openings are generally preserved (though miniaturized in AGA).
- Redness (Erythema): Suggests inflammation, often seen in active scarring alopecias such as lichen planopilaris, folliculitis decalvans, or discoid lupus erythematosus.
- Scaling: May indicate inflammatory conditions like seborrheic dermatitis (which can exacerbate hair loss), psoriasis, or specific types of scarring alopecia like lichen planopilaris or DLE.
- Pustules or Bumps: Point towards follicular inflammation or infection, as seen in folliculitis decalvans or dissecting cellulitis of the scalp.
- Shiny, smooth skin with loss of follicular openings: A hallmark of scarring (cicatricial) alopecia, indicating permanent destruction of hair follicles and replacement with scar tissue.
- Follicular plugging: The presence of keratinous plugs within hair follicles, characteristic of DLE and sometimes LPP.
A careful visual assessment of these alopecia symptoms pictures guides the initial differentiation between numerous conditions, setting the stage for further diagnostic steps.
Signs of Alopecia Pictures
Beyond the gross pattern of hair loss, a closer inspection reveals specific signs of alopecia pictures that are critical for accurate diagnosis. These microscopic or subtle macroscopic findings provide invaluable clues to the nature and activity of the hair loss process. These signs are often visible upon closer examination, sometimes requiring a dermatoscope, but many can be discerned with the naked eye by an experienced observer. Understanding these nuanced visual markers is essential for a comprehensive evaluation of any alopecia presentation.
Key specific signs often present in alopecia:
- Exclamation Mark Hairs:
- Appearance: Short, broken hairs that are narrower at the base (proximal end) near the scalp and wider at the distal end, resembling an exclamation mark. They often appear at the periphery of alopecia areata patches.
- Significance: A highly characteristic sign of active alopecia areata, indicating ongoing immune attack on the hair follicles. Their presence confirms the diagnosis of AA even in unusual presentations.
- Visual Context: Often seen alongside normal-looking hairs and vellus hairs within or around the patches.
- Broken Hairs / Short, Fractured Hairs:
- Appearance: Hairs that have fractured at various lengths, leaving stubble or very short, coarse segments.
- Significance: Common in trichotillomania due to physical pulling, tinea capitis (fungal infection) where hairs become brittle, and some forms of traumatic alopecia like traction alopecia. In scarring alopecias, broken hairs can sometimes be observed at the active margins.
- Differentiating Factor: Unlike exclamation mark hairs, these do not typically have the tapered base, unless seen in specific instances of active inflammatory alopecia impacting hair shaft integrity.
- Vellus Hairs:
- Appearance: Fine, short, non-pigmented, downy hairs that are usually barely visible.
- Significance: An increase in vellus hairs or the appearance of vellus hairs within a bald patch can be a sign of early regrowth in non-scarring alopecias like alopecia areata or androgenetic alopecia. In androgenetic alopecia, terminal hairs progressively miniaturize into vellus hairs.
- Visual Context: Indicates follicular activity, even if it’s producing miniaturized hairs.
- “Black Dots” or Cadaverized Hairs:
- Appearance: Small, dark dots on the scalp surface, representing the remnants of hair shafts that have broken off at or just below the scalp level and are trapped within the follicle.
- Significance: A common sign of tinea capitis and sometimes observed in alopecia areata or trichotillomania. In tinea capitis, it’s due to fungal invasion weakening the hair shaft.
- Visual Context: Often accompanied by scaling and inflammation in tinea capitis.
- Yellow Dots:
- Appearance: Yellowish or brownish-yellow dots, often slightly elevated, representing empty or degenerated follicular openings filled with sebum and keratin.
- Significance: Frequently seen in alopecia areata, especially chronic cases, and also in androgenetic alopecia. They indicate inactive follicles or sebaceous gland activity.
- Visual Context: Often found within bald patches of alopecia areata.
- Nail Dystrophy (Onychodystrophy):
- Appearance:
- Pitting: Small, pinpoint depressions on the nail plate, resembling the surface of a thimble.
- Trachyonychia (Sandpaper Nails): Roughening and dulling of the nail plate, often with longitudinal ridging.
- Onychomadesis: Shedding or loss of the nail plate from the nail bed.
- Longitudinal Ridging: Vertical lines or grooves along the length of the nail.
- Red Lunulae: Red discoloration of the crescent-shaped area at the base of the nail.
- Significance: Strongly associated with alopecia areata, particularly severe or extensive forms like alopecia totalis or universalis. Nail changes can precede, coincide with, or follow hair loss.
- Visual Context: Examination of fingernails and toenails is crucial during alopecia evaluation.
- Appearance:
- Eyebrow and Eyelash Loss:
- Appearance: Partial or complete absence of hair in the eyebrows and/or eyelashes.
- Significance: A common feature in more severe or extensive forms of alopecia areata (totalis, universalis), frontal fibrosing alopecia (often affecting eyebrows preferentially), and sometimes in inflammatory scarring alopecias.
- Visual Context: Can be a significant cosmetic concern and diagnostic clue.
- Follicular Plugging:
- Appearance: White or yellowish keratinous plugs visibly occluding the openings of hair follicles.
- Significance: A characteristic feature of discoid lupus erythematosus (DLE) and lichen planopilaris (LPP), indicating inflammation and destruction of the pilosebaceous unit.
- Visual Context: Often seen alongside perifollicular erythema and scaling in active lesions of scarring alopecia.
- Perifollicular Erythema and Scale:
- Appearance: Redness and fine flaking or scaling immediately surrounding the hair follicles.
- Significance: Hallmark of active inflammatory scarring alopecias such as lichen planopilaris, central centrifugal cicatricial alopecia (CCCA), and discoid lupus erythematosus (DLE). This indicates ongoing inflammation targeting the hair follicle.
- Visual Context: Often more prominent at the periphery of expanding patches of hair loss.
- Tufted Folliculitis:
- Appearance: Multiple hair shafts emerging from a single follicular opening, creating a “doll’s hair” or “tuft” appearance.
- Significance: Highly characteristic of folliculitis decalvans, an inflammatory scarring alopecia.
- Visual Context: Usually seen within areas of pustules, crusting, and scarring.
These specific signs of alopecia pictures, when combined with the overall hair loss pattern, provide a more granular understanding of the underlying dermatological process. Their presence or absence helps in narrowing down differential diagnoses and guiding further investigations.
Early Alopecia Photos
Recognizing early alopecia photos is paramount for timely intervention and potentially preventing extensive or permanent hair loss. Initial symptoms can be subtle, easily overlooked, or mistaken for normal hair shedding. However, paying close attention to these nascent changes can significantly impact the prognosis. Early visual clues often involve slight alterations in hair density, texture, or minimal scalp changes that progress over time if left unaddressed. Understanding what to look for in the nascent stages of hair loss is key for individuals seeking prompt medical advice.
Here are characteristic features often seen in early alopecia photos:
- Early Alopecia Areata (AA):
- Small, Solitary Smooth Patch: The very first sign is often a single, small, perfectly smooth, non-inflamed, circular or oval patch of complete hair loss. These patches can be anywhere on the scalp and may be as small as a dime.
- Subtle Exclamation Mark Hairs: Even in small patches, subtle exclamation mark hairs might be present at the borders, indicating active disease.
- Asymptomatic: Often, there are no accompanying symptoms like itching or pain, making the discovery of the patch a surprise.
- Scalp Appearance: The skin within the patch appears normal, healthy, and non-scarred.
- Early Androgenetic Alopecia (AGA) / Pattern Hair Loss:
- Receding Hairline (Males):
- Subtle Temple Thinning: Mild recession at the temples, leading to a slightly higher or more defined forehead.
- Fuzzy Hairline: Hairs along the frontal hairline may appear finer, shorter, and less pigmented than the rest of the scalp, indicating miniaturization.
- Crown Thinning (Males):
- Widening Part: A very slight increase in visibility of the scalp when looking at the crown.
- Reduced Hair Density: Hair in the vertex area feels less dense to the touch, or the scalp becomes marginally more visible under strong light.
- Female Pattern Hair Loss (FPHL):
- Widening of the Central Part: The most common initial sign is a progressive widening of the part line at the top of the scalp. This might be noticed when styling hair.
- Increased Scalp Visibility: The scalp becomes more apparent through the hair, particularly in the frontal-parietal region, while the frontal hairline often remains intact.
- Increased Shedding: An increase in daily hair shedding may precede noticeable thinning.
- Hair Miniaturization: Individual hair shafts appear thinner, shorter, and lighter in color than surrounding terminal hairs in affected areas.
- Receding Hairline (Males):
- Early Telogen Effluvium (TE):
- Increased Hair Shedding: The most prominent early sign is a sudden, significant increase in hair shedding during washing, brushing, or simply running hands through hair. This occurs 2-4 months after a trigger event (e.g., stress, illness, childbirth).
- Diffuse but Mild Thinning: While shedding is high, the overall hair density reduction might initially be subtle and generalized across the entire scalp, not localized to specific patches.
- No Scalp Inflammation: The scalp typically appears completely normal, without redness, scaling, or itching.
- Early Traction Alopecia:
- Broken Hairs along Hairline: Small, broken hairs or stubble along the frontal and temporal hairlines, indicating stress on the follicles.
- Small Bumps (Folliculitis): Tiny red bumps or pustules may appear around hair follicles along the strained hairline, signifying early inflammation.
- Slight Hairline Recession: A very subtle and gradual recession of the frontal or temporal hairline, often uneven.
- Scalp Tenderness or Itching: Mild discomfort or itchiness in the areas under tension from tight hairstyles.
- Early Scarring Alopecias (e.g., Lichen Planopilaris, CCCA):
- Perifollicular Redness and Scaling: One of the earliest visual clues is subtle redness and fine scaling directly around the hair follicles, often accompanied by itching or burning sensations. This is often more pronounced at the margins of active lesions.
- Small, Irregular Patches of Hair Loss: Hair loss may start as small, ill-defined patches. Unlike AA, the scalp within these patches might show subtle signs of inflammation or early scarring (e.g., subtle shiny appearance).
- Follicular Plugging: Tiny white or yellowish plugs might be seen within follicular openings, particularly in DLE or LPP.
- Subtle Hair Texture Changes: Hairs in affected areas might feel rougher or more brittle.
- Symptoms of Discomfort: Itching, burning, tenderness, or pain in the affected scalp areas, often preceding noticeable hair loss. These symptoms are crucial early indicators.
- Early Trichotillomania (TTM):
- Irregular Patches of Broken Hairs: Small, non-uniform patches with hairs of varying lengths (regrowing, broken, normal) are characteristic. The patches usually appear in areas easily reached by the individual’s hands.
- No True Baldness: Rarely are there completely smooth, bald areas. Instead, hair density is reduced, and hair is often sparse.
- Scalp Excoriations: Mild skin abrasions or irritation from repetitive pulling.
These detailed descriptions of early alopecia photos emphasize that vigilance for subtle changes in hair appearance and scalp condition is essential for initiating effective management strategies. Early detection of these warning signs allows for prompt dermatological evaluation, which can be critical for preserving hair and preventing the progression of some forms of alopecia.
Skin rash Alopecia Images
When alopecia presents with an accompanying skin rash, alopecia images take on a different and often more complex visual profile. The presence of erythema, scaling, pustules, or other dermatological changes on the scalp indicates an active inflammatory or immune-mediated process targeting the hair follicles, frequently leading to scarring (cicatricial) alopecia. Differentiating these inflammatory alopecias from non-inflammatory types is critical, as their prognosis and treatment approaches vary significantly. The rash itself provides invaluable diagnostic clues regarding the specific type of scarring alopecia.
Common types of alopecia associated with a skin rash or inflammatory scalp changes include:
- Lichen Planopilaris (LPP):
- Rash Appearance:
- Perifollicular Erythema: Redness or purplish-red discoloration concentrically surrounding the hair follicles, particularly at the active borders of hair loss.
- Perifollicular Scaling: Fine, white, adherent scale or hyperkeratosis (excess keratin) around the base of individual hair shafts.
- Violaceous Hue: The overall affected skin may have a subtle violaceous or purplish tint, characteristic of lichen planus.
- Hair Loss Pattern: Irregular patches of permanent hair loss, often with a smooth, atrophic, and shiny appearance in scarred areas, lacking follicular openings.
- Symptoms: Often associated with significant itching, burning, and tenderness of the scalp.
- Visual Progression: Starts with inflammation around follicles, leading to their destruction and irreversible scarring.
- Rash Appearance:
- Discoid Lupus Erythematosus (DLE) of the Scalp:
- Rash Appearance:
- Erythematous Patches: Well-demarcated, often circular or oval, reddish patches.
- Hyperkeratosis and Scaling: Thick, adherent scales that may be difficult to remove.
- Follicular Plugging: Prominent keratin plugs filling the hair follicles, which, when removed, often show a “carpet tack” appearance on their underside.
- Dyspigmentation: Patches may show areas of hyperpigmentation (darkening) at the periphery and hypopigmentation (lightening) in the scarred center.
- Hair Loss Pattern: Irregular, often patchy, scarring hair loss with noticeable atrophy and loss of follicular openings in the center of lesions.
- Symptoms: Can be itchy, tender, or asymptomatic. Sun exposure often exacerbates lesions.
- Visual Progression: Inflammation leads to follicular destruction and characteristic scarring.
- Rash Appearance:
- Folliculitis Decalvans (FD):
- Rash Appearance:
- Pustules: Clusters of sterile pustules (small, pus-filled bumps) centered around hair follicles.
- Crusting: Exudate from ruptured pustules leads to yellow-brown crusting.
- Erythema: Surrounding redness indicates inflammation.
- Tufted Folliculitis: A hallmark sign where multiple hair shafts (5-10 or more) emerge from a single dilated follicular opening, resembling a doll’s hair.
- Hair Loss Pattern: Irregular, often expanding patches of scarring alopecia, with active pustules and crusting at the advancing edges and smooth, atrophic scarring in older lesions.
- Symptoms: Often associated with pain, itching, and tenderness.
- Visual Progression: Chronic inflammation and recurrent bacterial infections lead to progressive follicular destruction and scarring.
- Rash Appearance:
- Central Centrifugal Cicatricial Alopecia (CCCA):
- Rash Appearance:
- Subtle Perifollicular Erythema and Scale: Often very mild in early stages, sometimes just tenderness or itching without overt rash.
- Inflammation at Periphery: Active inflammation, if visible, is often at the advancing edges of the hair loss patch, presenting as faint redness or small papules.
- Absence of Follicular Openings: As scarring progresses, follicular ostia disappear in the central, scarred areas.
- Hair Loss Pattern: Begins on the crown or vertex and expands centrifugally (outwards) in a circular pattern. Hair loss patches are smooth, shiny, and atrophic, indicating scarring.
- Symptoms: Can range from asymptomatic to intense itching, burning, and tenderness.
- Visual Progression: Progressive follicular destruction from an unknown inflammatory process (often linked to hair care practices) leading to permanent baldness.
- Rash Appearance:
- Dissecting Cellulitis of the Scalp (DCS) / Perifolliculitis Capitis Abscedens et Suffodiens:
- Rash Appearance:
- Nodules and Abscesses: Deep-seated, painful, boggy nodules and abscesses (collections of pus) on the scalp.
- Pustules and Sinus Tracts: May drain pus and blood through multiple sinus tracts, forming interconnecting channels under the skin.
- Scarring: Irregular, hypertrophic (raised) or atrophic (depressed) scarring.
- Hair Loss Pattern: Irregular, permanent hair loss in areas affected by inflammation and scarring. Hairs often show “tufting” at the borders of lesions.
- Symptoms: Severe pain, tenderness, and sometimes systemic symptoms like fever.
- Visual Progression: A chronic, progressive inflammatory condition leading to significant follicular destruction, abscess formation, and extensive scarring.
- Rash Appearance:
- Tinea Capitis (Scalp Ringworm):
- Rash Appearance:
- Scaly Patches: Patches of varying sizes with fine to coarse grayish scales, often mimicking dandruff.
- Erythema: Underlying redness of the scalp.
- Pustules: Small pustules may be present, indicating inflammation.
- “Black Dots”: Hairs breaking off at the scalp surface leave tiny black dots.
- Kerion: In severe cases, a painful, boggy, inflamed mass with pustules and crusting, representing a hypersensitivity reaction to the fungus.
- Hair Loss Pattern: Irregular patches of partial hair loss (not complete baldness), with broken hairs and increased fragility. Can be non-scarring if treated early, but kerion can lead to scarring.
- Symptoms: Often itchy, sometimes painful.
- Visual Progression: Fungal infection of hair shafts, leading to brittleness and breakage.
- Rash Appearance:
The presence of a skin rash in alopecia images is a crucial indicator pointing towards an inflammatory or infectious etiology. Accurate identification of these specific dermatological features is vital for correct diagnosis and the implementation of targeted therapies to halt inflammation and prevent further permanent hair loss.
Alopecia Treatment
While this article primarily focuses on visual symptoms, understanding alopecia treatment strategies is crucial as they directly aim to reverse, halt, or manage the visual manifestations described. Treatment approaches are highly individualized, depending on the specific type of alopecia, its severity, duration, and the patient’s overall health. The goal of any intervention is to promote hair regrowth, reduce inflammation, prevent further hair loss, and improve the overall cosmetic appearance of the scalp. This section will outline common treatment modalities and how they address the visual signs of alopecia.
General treatment categories and their visual impact:
- Topical Treatments: Applied directly to the scalp to stimulate hair follicles or reduce localized inflammation.
- Minoxidil (Rogaine):
- Mechanism: Vasodilator that prolongs the anagen (growth) phase of hair follicles and may increase follicular size.
- Visual Impact: Can lead to visible hair regrowth, increased hair density, and conversion of vellus hairs to terminal hairs in androgenetic alopecia and sometimes alopecia areata. It reduces the appearance of scalp visibility.
- Forms: Available as a liquid solution or foam, typically applied once or twice daily.
- Corticosteroids (e.g., Clobetasol, Betamethasone):
- Mechanism: Potent anti-inflammatory agents that suppress the immune response attacking hair follicles.
- Visual Impact: Reduces redness, scaling, and inflammation visible in conditions like lichen planopilaris, DLE, and active alopecia areata patches. Can promote hair regrowth in non-scarring inflammatory alopecias.
- Forms: Creams, lotions, foams, solutions, or ointments.
- Anthralin:
- Mechanism: Immunomodulatory and antiproliferative effects, thought to impact the immune cells involved in alopecia areata.
- Visual Impact: Can induce hair regrowth in patchy alopecia areata, potentially reducing the size of bald areas.
- Usage: Applied as a short-contact therapy to minimize skin irritation.
- Calcineurin Inhibitors (e.g., Tacrolimus, Pimecrolimus):
- Mechanism: Immunosuppressants that specifically target immune cell activation.
- Visual Impact: Can reduce inflammation (erythema, scaling) in certain inflammatory alopecias like LPP or DLE, potentially stabilizing hair loss. Less potent for regrowth.
- Topical Finasteride:
- Mechanism: 5-alpha reductase inhibitor, reduces dihydrotestosterone (DHT) locally in the scalp.
- Visual Impact: Can slow down hair loss, increase hair count, and improve hair thickness in androgenetic alopecia, visually making hair appear denser.
- Minoxidil (Rogaine):
- Injections: Delivering medication directly into the scalp for localized action.
- Intralesional Corticosteroids (e.g., Triamcinolone Acetonide):
- Mechanism: Directly injects anti-inflammatory corticosteroids into active patches or inflammatory areas.
- Visual Impact: Highly effective for stimulating regrowth in patchy alopecia areata, visibly reducing the size of bald spots. Reduces inflammation (redness, tenderness) in active scarring alopecias, potentially halting progression at the site of injection.
- Usage: Administered every 4-6 weeks for several sessions.
- Intralesional Corticosteroids (e.g., Triamcinolone Acetonide):
- Oral Medications: Systemic treatments for more widespread or severe alopecia.
- Finasteride (Propecia) / Dutasteride (Avodart):
- Mechanism: 5-alpha reductase inhibitors, reduce systemic and scalp DHT levels.
- Visual Impact: Significantly slows hair loss, promotes regrowth, and increases hair density and thickness across the scalp in androgenetic alopecia. Can improve the visual appearance of thinning and balding.
- Minoxidil (Oral):
- Mechanism: Systemic vasodilator that may enhance hair growth.
- Visual Impact: Increasingly used for diffuse hair loss conditions, showing promising results in increasing hair density and reducing shedding across the scalp.
- Corticosteroids (e.g., Prednisone):
- Mechanism: Potent systemic immunosuppressants.
- Visual Impact: Used for acute, rapidly progressing, or widespread alopecia areata, or severe inflammatory scarring alopecias to quickly suppress inflammation and induce regrowth or halt destruction. Visibly reduces redness and inflammation.
- Usage: Short courses are preferred due to potential side effects.
- Immunosuppressants (e.g., Methotrexate, Cyclosporine, Azathioprine):
- Mechanism: Systemic agents that broadly suppress the immune system.
- Visual Impact: Used for severe, recalcitrant alopecia areata or progressive scarring alopecias (LPP, DLE) to control inflammation and prevent further hair loss. Aims to stabilize the scalp and prevent new bald areas.
- Janus Kinase (JAK) Inhibitors (e.g., Baricitinib, Tofacitinib, Ruxolitinib):
- Mechanism: Target specific signaling pathways (JAK-STAT) involved in immune cell activity that drives alopecia areata.
- Visual Impact: Revolutionized treatment for severe alopecia areata, leading to significant and often complete hair regrowth of scalp, eyebrow, and eyelash hair. Dramatically changes the visual presentation from baldness to full hair coverage.
- Antibiotics (e.g., Doxycycline, Rifampicin, Clindamycin):
- Mechanism: Primarily anti-inflammatory effects and antibacterial action.
- Visual Impact: Used for folliculitis decalvans and dissecting cellulitis to reduce pustules, redness, pain, and prevent progression of scarring. Visibly reduces inflammatory lesions.
- Antifungals (e.g., Griseofulvin, Terbinafine, Fluconazole):
- Mechanism: Eradicate fungal infections.
- Visual Impact: Resolves scaling, redness, and hair fragility in tinea capitis, allowing for normal hair regrowth. Prevents progression to scarring if kerion is present.
- Finasteride (Propecia) / Dutasteride (Avodart):
- Light Therapy and Phototherapy (e.g., Excimer Laser, PUVA):
- Mechanism: Delivers specific wavelengths of light to the scalp, thought to have immunomodulatory effects.
- Visual Impact: Can stimulate regrowth in alopecia areata and reduce inflammation in some scarring alopecias, potentially reducing bald patches and scalp redness.
- Platelet-Rich Plasma (PRP) Therapy:
- Mechanism: Involves injecting a concentration of a patient’s own platelets, rich in growth factors, into the scalp.
- Visual Impact: May stimulate hair growth, increase hair thickness, and improve hair density in androgenetic alopecia and some cases of alopecia areata, leading to a visually fuller scalp.
- Hair Transplantation:
- Mechanism: Surgical procedure involving transplanting hair follicles from donor areas (typically the back of the scalp) to bald or thinning areas.
- Visual Impact: Provides a permanent solution for restoring hair to scarred or balding areas, particularly effective in stable androgenetic alopecia and some types of stable scarring alopecia. Visibly restores hair density and recreates hairlines.
- Considerations: Not suitable for active or unstable forms of alopecia.
- Lifestyle and Supportive Care:
- Nutritional Support: Addressing deficiencies (e.g., iron, vitamin D, zinc) can improve overall hair health and contribute to visual improvement in hair quality and density.
- Stress Management: Reducing stress can positively impact conditions like telogen effluvium and potentially alopecia areata, leading to reduced shedding and improved regrowth.
- Hair Care Practices: Avoiding tight hairstyles and harsh chemical treatments can prevent traction alopecia and reduce irritation in inflammatory alopecias, visibly protecting existing hair.
In summary, the diverse array of alopecia treatment options aims to directly or indirectly address the observable symptoms of hair loss and scalp conditions. From promoting visible hair regrowth and increasing hair density to reducing inflammation, redness, and scarring, each treatment modality plays a role in improving the visual appearance and health of the scalp. Early and accurate diagnosis, guided by characteristic visual signs, is paramount to selecting the most effective treatment strategy.