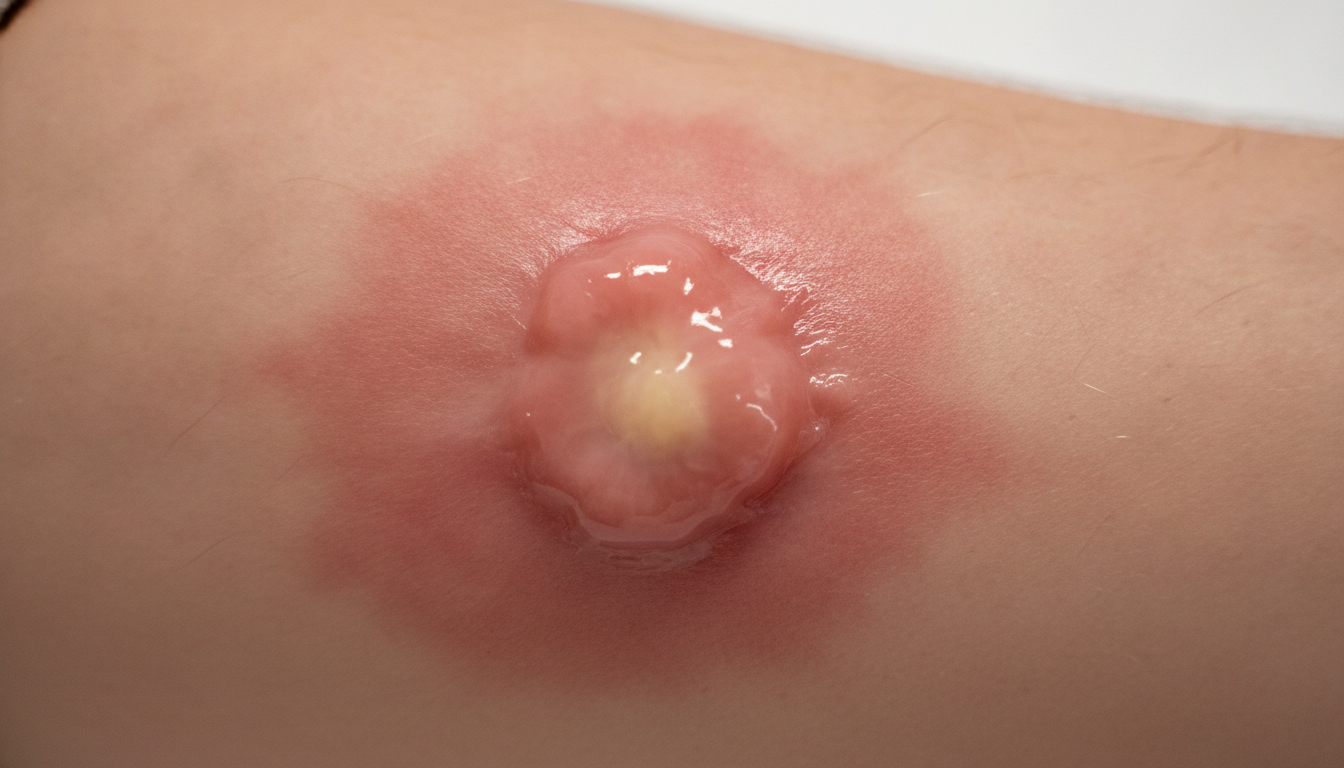
Prompt recognition of `Abscess after an injection symptoms pictures` is crucial for timely intervention and preventing severe complications. Understanding the specific visual and physical cues associated with these post-injection infections can significantly aid in early diagnosis and appropriate management. This article details the symptoms, signs, and appearance of an abscess following an injection, as well as its treatment.
Abscess after an injection Symptoms Pictures
An abscess after an injection is a localized collection of pus within tissues, resulting from a bacterial or sometimes non-infectious inflammatory response at the injection site. Identifying the correct Abscess after an injection symptoms pictures is paramount for proper medical attention. The symptoms can vary in severity and presentation depending on the causative agent, the patient’s immune status, and the depth of the injection. Generally, these symptoms are progressive, worsening over hours to days without intervention. Recognizing these symptoms early can prevent spread and systemic complications.
The primary symptoms often reported by individuals developing an injection site abscess include:
- Pain: This is almost universally present and often the first symptom noticed. Initially, it might be a mild tenderness, but it rapidly escalates to a deep, throbbing, or pulsatile pain that is constant and worsens with pressure or movement. The pain often becomes disproportionate to the visible size of the lesion, indicating deep tissue involvement and pressure buildup from accumulated pus. Patients describe it as an intense, localized discomfort that can interfere with sleep and daily activities. The area around the injection site may feel particularly sensitive to touch.
- Swelling: A noticeable lump or elevation at the injection site is a hallmark sign. The swelling can range from a small, firm nodule to a large, diffuse mass that encompasses a significant area around the injection point. This induration is due to inflammation and the accumulation of fluid and pus. Over time, the swelling may become softer in the center, indicating the maturation of the abscess and the liquefaction of tissue into pus. The extent of swelling can obscure the original injection mark.
- Redness (Erythema): The skin overlying the developing abscess typically becomes red or discolored. This redness is a sign of inflammation and increased blood flow to the infected area. The color can range from a light pink to a vibrant, angry red or even a purplish hue in more severe or deeper infections. The redness may spread outwards from the central point of the injection, indicating an expanding area of inflammation, possibly cellulitis.
- Warmth: The affected skin will feel noticeably warmer than the surrounding healthy skin. This increased local temperature is another cardinal sign of inflammation and infection, resulting from increased metabolic activity and blood flow at the site. The warmth can be palpated with the back of the hand and often correlates with the degree of redness.
- Fever and Chills: Systemic symptoms like fever (elevated body temperature, often above 100.4°F or 38°C) and chills indicate a more widespread inflammatory response or the body’s attempt to fight a significant infection. These symptoms suggest that the localized infection might be causing systemic effects and warrant immediate medical evaluation. The fever can be low-grade or high, and accompanied by malaise, fatigue, and general body aches.
- Pus Formation/Discharge: While not always visible externally until the abscess spontaneously ruptures or is incised, the internal collection of pus is the defining characteristic. If the abscess breaks open, a thick, often yellowish, greenish, or brownish fluid with a foul odor may drain from the site. This discharge is composed of dead white blood cells, bacteria, and necrotic tissue. Visible pus is a definitive sign of a mature abscess.
- Fluctuance: As the abscess matures, the core of the swollen area may become soft and compressible, feeling like a fluid-filled sac under the skin. This “fluctuance” is a critical clinical sign indicating the presence of liquid pus that is ready for drainage. Palpating for fluctuance requires a gentle but firm touch, pressing down on one side of the lesion and feeling for displacement of fluid on the opposite side.
- General Malaise and Fatigue: The body’s immune response to infection can lead to a general feeling of unwellness, lack of energy, and fatigue. These non-specific symptoms often accompany fever and chills and indicate that the body is expending significant resources to combat the infection.
Understanding these post-injection abscess symptoms helps in differentiating a simple injection site reaction from a developing infection, emphasizing the need for prompt medical attention if these signs are observed.
Signs of Abscess after an injection Pictures
Beyond the subjective symptoms, there are objective Signs of Abscess after an injection Pictures that a healthcare professional can observe and assess during a physical examination. These signs are critical for confirming the diagnosis of an injection site infection and guiding treatment. Visual inspection and palpation reveal specific characteristics of the abscess and surrounding tissues. Observing these signs in conjunction with the reported symptoms provides a comprehensive clinical picture of the severity and progression of the post-injection abscess.
Key objective signs often present include:
- Localized Tenderness on Palpation: When the affected area is gently touched or pressed, it elicits a disproportionate amount of pain. This tenderness is a more localized and specific finding than general pain and helps delineate the extent of the inflammatory process. The tenderness often peaks directly over the purulent collection.
- Induration and Edema: The tissue around the injection site and the abscess itself will feel firm or hardened (indurated) due to inflammation and fluid accumulation. This induration often has poorly defined borders, especially if accompanied by cellulitis. Edema refers to the visible swelling caused by fluid accumulation in the interstitial spaces.
- Skin Discoloration: While redness is a primary symptom, the skin may exhibit other discolorations. In more advanced cases, or with deeper infections, the skin may appear purplish, dusky, or even bluish, indicating impaired circulation or deeper tissue involvement. If necrosis begins, parts of the skin can turn black (eschar). These color changes are crucial visual cues for assessing tissue viability and infection severity.
- Shiny, Taut, or Stretched Skin: The overlying skin may appear shiny or stretched due to the underlying pressure from the accumulated pus and swelling. This can be particularly noticeable with larger abscesses, giving the skin a smooth, almost translucent appearance, indicating significant dermal and subcutaneous tension.
- Central Softening or Fluctuance: As mentioned previously, the development of a soft, compressible center within a firm mass is the most definitive physical sign of a mature abscess ready for drainage. This sensation of a fluid-filled cavity distinguishes an abscess from a solid inflammatory mass or a sterile granuloma.
- Pustule or Nodule Formation: In some instances, particularly if the infection is more superficial, a visible pustule (a small, raised lesion containing pus) or a nodule (a small, solid, raised lump) may form directly over the injection site. These are often precursors to a larger abscess or part of the inflammatory response.
- Spontaneous Drainage: If the abscess ruptures on its own, pus will drain from the site. The presence of purulent discharge, especially if it is thick, malodorous, or discolored (yellow, green, brown), is a clear sign of an abscess. The drainage may be continuous or intermittent, and the amount can vary significantly.
- Regional Lymphadenopathy: The lymph nodes draining the affected area (e.g., axillary nodes for arm injections, inguinal nodes for leg/buttock injections) may become enlarged, tender, and firm. This swollen gland response indicates that the lymphatic system is actively fighting the infection, trapping pathogens and immune cells.
- Tracking Lymphangitis: Red streaks extending from the injection site towards the regional lymph nodes can sometimes be observed. These streaks indicate inflammation of the lymphatic vessels due to the spread of infection. This is a serious sign, suggesting the infection is progressing beyond the localized area.
- Systemic Signs of Sepsis: In severe, untreated cases, the infection can spread into the bloodstream, leading to sepsis. Signs include persistent fever, rapid heart rate (tachycardia), rapid breathing (tachypnea), low blood pressure (hypotension), confusion, and altered mental status. These are medical emergencies requiring immediate intensive care.
Each of these signs of an injection site abscess provides valuable information for diagnosis and helps healthcare providers determine the urgency and specific approach to treatment. Early identification of these objective signs through careful examination is crucial for effective patient management and preventing potentially life-threatening complications.
Early Abscess after an injection Photos
Recognizing Early Abscess after an injection Photos is often challenging because the initial signs can mimic a normal post-injection reaction. Many patients experience mild pain, redness, and swelling immediately after an injection, which usually subsides within a day or two. However, when these symptoms persist, worsen, or are accompanied by new, specific characteristics, it signals the potential development of an early injection abscess. The key is to differentiate a benign reaction from the nascent stages of an infection that demands attention. The progression from a minor irritation to a full-blown abscess can be rapid, making early detection critical for a better outcome.
The initial manifestation of an abscess after an injection typically involves a constellation of subtle yet important changes:
- Persistent or Worsening Mild Redness and Swelling: Unlike the transient redness and swelling that fades within 24-48 hours, early abscess formation presents with redness that either does not resolve or gradually intensifies. The swelling might also feel firmer than expected for a simple injection reaction, indicating underlying tissue inflammation and fluid accumulation. The borders of this redness might initially be well-defined but can become diffuse.
- Localized Tenderness Beyond 48 Hours: While initial tenderness is common, its persistence or increase beyond the second day post-injection is a significant warning sign. The tenderness might be localized to a small, firm area, rather than a diffuse, mild soreness. This pinpoint tenderness suggests an inflammatory focus that is not resolving naturally.
- Subtle Warmth: An early abscess will manifest with a subtle increase in local temperature that is more pronounced than what would be expected from a minor inflammatory response. The area might feel distinctly warmer to touch compared to the surrounding skin, even if the redness is not yet very prominent.
- Small, Firm Nodule or Lump: One of the earliest palpable signs of an impending abscess is the formation of a small, firm, slightly painful nodule or lump at or very near the injection site. This nodule represents the initial collection of inflammatory cells and possibly bacteria, forming the core of what will become a pus-filled cavity. It might be mistaken for a normal granuloma or a post-injection hematoma, but its progressive nature distinguishes it.
- Delayed Onset of Symptoms: Sometimes, an abscess does not immediately manifest but develops days to even weeks after the injection. This delayed presentation can be particularly challenging to diagnose as patients might not immediately associate symptoms with the earlier injection. Delayed symptoms often point towards less virulent organisms or a sterile abscess.
- Mild Systemic Symptoms: In the very early stages, systemic symptoms like fever might be low-grade or absent. However, some individuals might report a general feeling of being unwell, mild fatigue, or generalized body aches, even without a significant fever. These subtle systemic cues suggest the body’s immune system is actively responding to an infection.
- Lack of Improvement with Conservative Measures: If the initial mild symptoms (redness, swelling, tenderness) do not improve with typical conservative measures like cold compresses and rest, and instead seem to be static or worsening, it strongly suggests a pathological process like an abscess developing rather than a simple reaction.
It is also important to differentiate between an infectious early abscess and a sterile abscess. A sterile abscess (or non-infectious abscess) develops due to irritation from the injected substance itself, without bacterial infection. Early sterile abscesses may present with similar localized swelling and pain but often exhibit less redness, warmth, and rarely progress to systemic symptoms like fever. However, they can still become fluctuant and may require drainage. Their progression tends to be slower and less aggressive.
Visual examples in Early Abscess after an injection Photos often depict a localized area of slight swelling and redness, perhaps with a central firm spot. The key distinguishing factor from a normal reaction is the persistence and gradual worsening of these signs, coupled with increasing pain. If these early signs are identified, especially in conjunction with risk factors for infection (e.g., immunocompromised state, poor injection technique), prompt medical consultation is advised to prevent the abscess from fully maturing and leading to more serious complications.
Skin rash Abscess after an injection Images
While an abscess itself is a localized collection of pus, the surrounding skin often develops various changes or a skin rash abscess after an injection images that provides critical diagnostic clues. These dermatological manifestations can range from simple inflammatory responses to more severe, spreading infections that accompany or precede the abscess formation. Understanding these distinct skin presentations is vital for comprehensive assessment of an injection site infection. The appearance of the skin can indicate the severity of the underlying infection, its potential to spread, and the presence of associated complications.
Specific skin changes associated with an abscess after an injection include:
- Cellulitis: This is a common and often co-occurring infection with an abscess. Cellulitis presents as a spreading bacterial infection of the deeper layers of the skin and subcutaneous tissue. Visually, it manifests as an area of redness, warmth, and tenderness that is poorly demarcated (has fuzzy, irregular borders) and expands over time. The skin can appear shiny or stretched. Cellulitis often surrounds an abscess, indicating the infection has extended beyond the immediate pus pocket. It is characterized by:
- Diffuse, spreading erythema: Redness that is not confined to a specific area but radiates outwards.
- Significant warmth to touch: The skin feels very hot.
- Painful to touch: Tenderness is widespread across the affected area.
- Possible blistering or bullae: In more severe cases, fluid-filled blisters can form on the surface of the skin.
- Systemic symptoms: Fever, chills, and malaise are common with cellulitis.
- Erysipelas: Similar to cellulitis but typically more superficial, affecting the upper dermis and lymphatic system. Erysipelas is characterized by a bright red, raised, indurated lesion with sharply demarcated (well-defined) borders. The skin often has an “orange peel” texture (peau d’orange). While less common at injection sites than cellulitis, it can occur and indicates a specific type of spreading bacterial infection.
- Folliculitis/Furunculosis: If the injection was superficial or occurred in an area with hair follicles, the infection might initially manifest as folliculitis (inflammation of hair follicles) or furunculosis (boils). These are often multiple, small, red, tender bumps, sometimes with a central pustule or head. While smaller than typical abscesses, they are essentially small abscesses originating from a hair follicle.
- Skin Discoloration Progression: Beyond initial redness, the skin overlying an abscess can undergo a spectrum of color changes indicative of worsening pathology.
- Purplish or Dusky Hues: Indicates venous congestion, compromised circulation, or deeper tissue infection.
- Bluish Mottling (Livedo Reticularis): A net-like or reticulated vascular pattern, which can suggest impaired blood flow to the skin, sometimes seen in severe infections or septic conditions.
- Black Eschar (Necrosis): The most severe form of skin discoloration, indicating tissue death. This happens when the infection, inflammation, or pressure from the abscess compromises local blood supply sufficiently to cause infarction. Necrotic tissue appears black, leathery, and insensitive.
- Ulceration and Skin Breakdown: As an abscess matures and the pressure within builds, the overlying skin can become thin, stretched, and eventually break down, leading to an open wound or ulcer. This exposes the underlying purulent material. The edges of the ulcer may be inflamed, and the base may show necrotic tissue or granulation tissue if healing has begun.
- Satellite Lesions: Sometimes, smaller pustules or areas of inflammation (satellite lesions) may appear in the vicinity of the main abscess. These indicate either multiple points of infection or spreading infection from the primary site.
- Tracking Lymphangitis: As mentioned previously, the appearance of red streaks that track up the limb towards regional lymph nodes is a specific skin manifestation indicating lymphatic spread of the infection. This is a concerning sign and requires urgent treatment.
These specific skin rash after injection abscess characteristics are crucial for a thorough clinical evaluation. They not only help in diagnosing the abscess but also provide insights into the extent of the infection, potential complications, and guide the choice of appropriate medical interventions. Any of these severe skin changes observed around an injection site should prompt immediate medical consultation.
Abscess after an injection Treatment
Treating an Abscess after an injection is crucial to prevent further complications, reduce pain, and eradicate the infection. The primary goal of treatment is to drain the pus, eliminate the causative organisms, and promote healing. The approach to treatment is usually multi-faceted, involving both local interventions and systemic therapies. Delay in treatment can lead to systemic spread of infection (sepsis), extensive tissue damage, and prolonged recovery.
Diagnosis and Assessment
Before initiating treatment, a thorough diagnosis is essential:
- Clinical Examination: A healthcare provider will visually inspect and palpate the site, assessing for the characteristic signs like redness, warmth, swelling, tenderness, and fluctuance.
- Imaging Studies:
- Ultrasound: Often the gold standard for diagnosing deeper abscesses, confirming the presence and extent of fluid collection, and differentiating it from solid masses or cellulitis. It helps guide aspiration or incision.
- CT Scan/MRI: May be used for very deep, complex, or multiple abscesses, especially if there is suspicion of bone involvement (osteomyelitis) or spread to vital structures.
- Pus Culture and Sensitivity: If pus is drained, a sample should be sent for Gram stain, culture, and antibiotic sensitivity testing. This identifies the specific bacteria causing the infection and determines which antibiotics will be most effective. This is critical, especially given the rise of antibiotic-resistant organisms like Methicillin-resistant Staphylococcus aureus (MRSA).
- Blood Tests: Complete Blood Count (CBC) will often show elevated white blood cell count (leukocytosis) with a left shift, indicating a bacterial infection. C-reactive protein (CRP) and Erythrocyte Sedimentation Rate (ESR) may also be elevated, reflecting systemic inflammation.
Mainstay Treatment: Incision and Drainage (I&D)
For most mature abscesses, incision and drainage (I&D) is the definitive treatment. This procedure involves surgically opening the abscess to allow the pus to escape.
- Procedure Steps:
- Local Anesthesia: The area around the abscess is numbed with a local anesthetic (e.g., lidocaine).
- Incision: A small incision is made with a scalpel over the most fluctuant or prominent part of the abscess.
- Drainage and Exploration: The pus is allowed to drain. The cavity is then explored with a blunt instrument (e.g., hemostat or finger) to break up loculations (compartments within the abscess) and ensure complete drainage of all purulent material.
- Irrigation: The abscess cavity may be irrigated with sterile saline solution to cleanse it further.
- Packing: A sterile gauze strip (often impregnated with an antiseptic like iodoform) is usually packed loosely into the cavity. This packing helps to keep the wound open, allowing for continued drainage, and promotes healing from the inside out, preventing premature closure of the skin surface.
- Benefits of I&D:
- Rapid symptom relief (pain, pressure).
- Removal of infectious material.
- Reduces bacterial load.
- Promotes wound healing.
- Non-infectious (Sterile) Abscesses: Even sterile abscesses, which are not caused by bacteria, may require I&D if they are large, symptomatic, or persist, as the body may not reabsorb the collected fluid effectively.
Antibiotic Therapy
While I&D is primary, antibiotics for post-injection infection are often prescribed, especially if:
- There is significant surrounding cellulitis.
- The patient has systemic signs of infection (fever, chills).
- The patient is immunocompromised.
- The abscess is large or deep.
- The abscess is located on the face, hands, or genitals.
- There is concern for MRSA infection.
Antibiotic Regimen:
- Empiric Therapy: Initially, broad-spectrum antibiotics are chosen to cover common skin pathogens (e.g., Staphylococcus aureus and Streptococcus pyogenes), including potential MRSA coverage if prevalent in the community (e.g., clindamycin, trimethoprim-sulfamethoxazole, doxycycline).
- Culture-Directed Therapy: Once culture results are available, antibiotics may be narrowed or adjusted based on the specific pathogen and its sensitivity profile.
- Duration: Typically 7-14 days, but can vary depending on the severity of the infection and patient response.
- Route: Oral antibiotics are usually sufficient for uncomplicated cases; intravenous (IV) antibiotics may be necessary for severe infections, immunocompromised patients, or those unable to tolerate oral medication.
Wound Care
Proper wound care for abscess drainage sites is crucial for healing and preventing recurrence:
- Dressing Changes: Regular dressing changes, often daily or every other day, are required. The packing gauze is typically removed and replaced, initially by a healthcare professional, then potentially by the patient or a family member with proper instruction.
- Cleaning: The wound should be gently cleaned with sterile saline or an antiseptic solution (as instructed) during dressing changes.
- Debridement: Any necrotic tissue within the wound should be carefully debrided (removed) by a healthcare professional to promote healthy tissue growth.
- Warm Compresses: After I&D, warm compresses can help promote blood flow, comfort, and continued drainage.
Pain Management and Supportive Care
- Analgesics: Over-the-counter pain relievers such as acetaminophen or NSAIDs (ibuprofen, naproxen) can help manage pain and reduce fever. Opioid analgesics may be prescribed for severe post-procedural pain.
- Hydration and Rest: Adequate fluid intake and rest support the body’s healing process.
- Elevation: Elevating the affected limb can help reduce swelling and discomfort.
Potential Complications and Prevention
Untreated or improperly treated abscesses can lead to:
- Spread of Infection: Cellulitis, lymphangitis, osteomyelitis (bone infection), septic arthritis (joint infection), or even sepsis (systemic infection).
- Recurrence: Incomplete drainage or persistent risk factors can lead to the abscess reforming.
- Scarring: Significant tissue damage from the abscess or the surgical drainage can lead to permanent scarring.
- Necrotizing Fasciitis: A rare but life-threatening rapidly spreading bacterial infection that destroys soft tissue.
Prevention of injection site abscesses relies heavily on:
- Strict Aseptic Technique: Using sterile needles, syringes, and ensuring the injection site is thoroughly cleaned with an antiseptic (e.g., alcohol, chlorhexidine) before injection.
- Proper Injection Sites: Selecting appropriate sites free from skin lesions, scars, or areas of active infection.
- Correct Injection Depth: Ensuring the medication is injected into the intended tissue layer (e.g., intramuscular, subcutaneous) to prevent deposition in inappropriate tissues that can lead to irritation or sterile abscess formation.
- Patient Education: Advising patients to monitor injection sites for signs of infection and seek medical attention if symptoms develop.
Timely and appropriate abscess treatment after injection, guided by accurate diagnosis, is essential for a full recovery and to minimize the risk of serious complications. Always consult a healthcare professional if an injection site abscess is suspected.